Related Experiment Video
Updated: Aug 16, 2026
Standardized Hemorrhagic Shock Induction Guided by Cerebral Oximetry and Extended Hemodynamic Monitoring in Pigs
Published on: May 21, 2019
Oxygent as a top load to colloid and hyperoxia is more effective in resuscitation from hemorrhagic shock than colloid
Gregor I Kemming1, Franz G Meisner, Christoph J Wojtczyk
1Institute for Surgical Research, Klinikum Grosshadern, Ludwig-Maximilians-University Munich, 81377, Germany.

Abstract:
Perfluorocarbon (PFC) emulsions are intravascular oxygen therapeutics that temporarily enhance tissue oxygenation in dilutional anemia. However, PFC emulsions are not resuscitation fluids because PFCs only work optimally in the presence of high O2 partial pressure (hyperoxia); moreover, because they have no oncotic potential, dosing limitations prevent their use to permanently replace large hemorrhage volumes. Our objective was to clarify whether in the presence of hyperoxia a conventional colloid therapy supplemented by PFC is more efficacious than colloid alone. To answer this question, 22 anesthetized, ventilated dogs were hemorrhaged to a mean arterial pressure of 45 mmHg and were kept at this level until a metabolic O2 debt of 120 mL kg(-1) body weight had evolved. Hyperoxia was established and dogs were randomly allocated to receive colloid (6% HES, Hydroxy Ethyl Starch shed blood volume) or colloid together with Oxygent (perflubron emulsion, 60%, w/v; Alliance Pharmaceutical Corp., San Diego, CA; single dose, 4.5 mL kg(-1); i.e., 2.7 g PFC kg body weight) in a blinded fashion. Hemodynamic and O2 transport parameters, intestinal mucosal blood flow (microspheres), and O2 partial pressure (MDO-Electrode; Eschweiler, Kiel, Germany) were measured at baseline, in shock, and during 3 h post-therapy. In the presence of hyperoxia, Oxygent improved the amount of physically dissolved O2 in plasma and increased the contribution of physically dissolved O2 to global O2 delivery (P < 0.05) and thus whole body O2 consumption when compared with colloid alone (P < 0.05). As a result, Oxygent reduced intestinal mucosal hypoxia and global O2 debt within the first hour post-therapy (P < 0.05). We conclude that under hyperoxic conditions, fluid resuscitation supplemented by Oxygent was more efficacious than colloid and hyperoxia alone. PFC temporarily enhanced intestinal mucosal tissue oxygenation during resuscitation.
Related Concept Videos
 01:27
Oxygen Transport in the Blood
 01:23
Hypoxia
Types of Hypoxia
There are four primary types of hypoxia, each resulting from a different cause:
1. Anemic hypoxia: This type occurs due to insufficient oxygen delivery caused by a lack of red blood cells (RBCs) or RBCs with abnormal or...
 01:16
Treatment for Pulmonary Arterial Hypertension: Oxygen Therapy for Respiratory Failure
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue, improving...
 01:20
Respiration and Gaseous Exchange
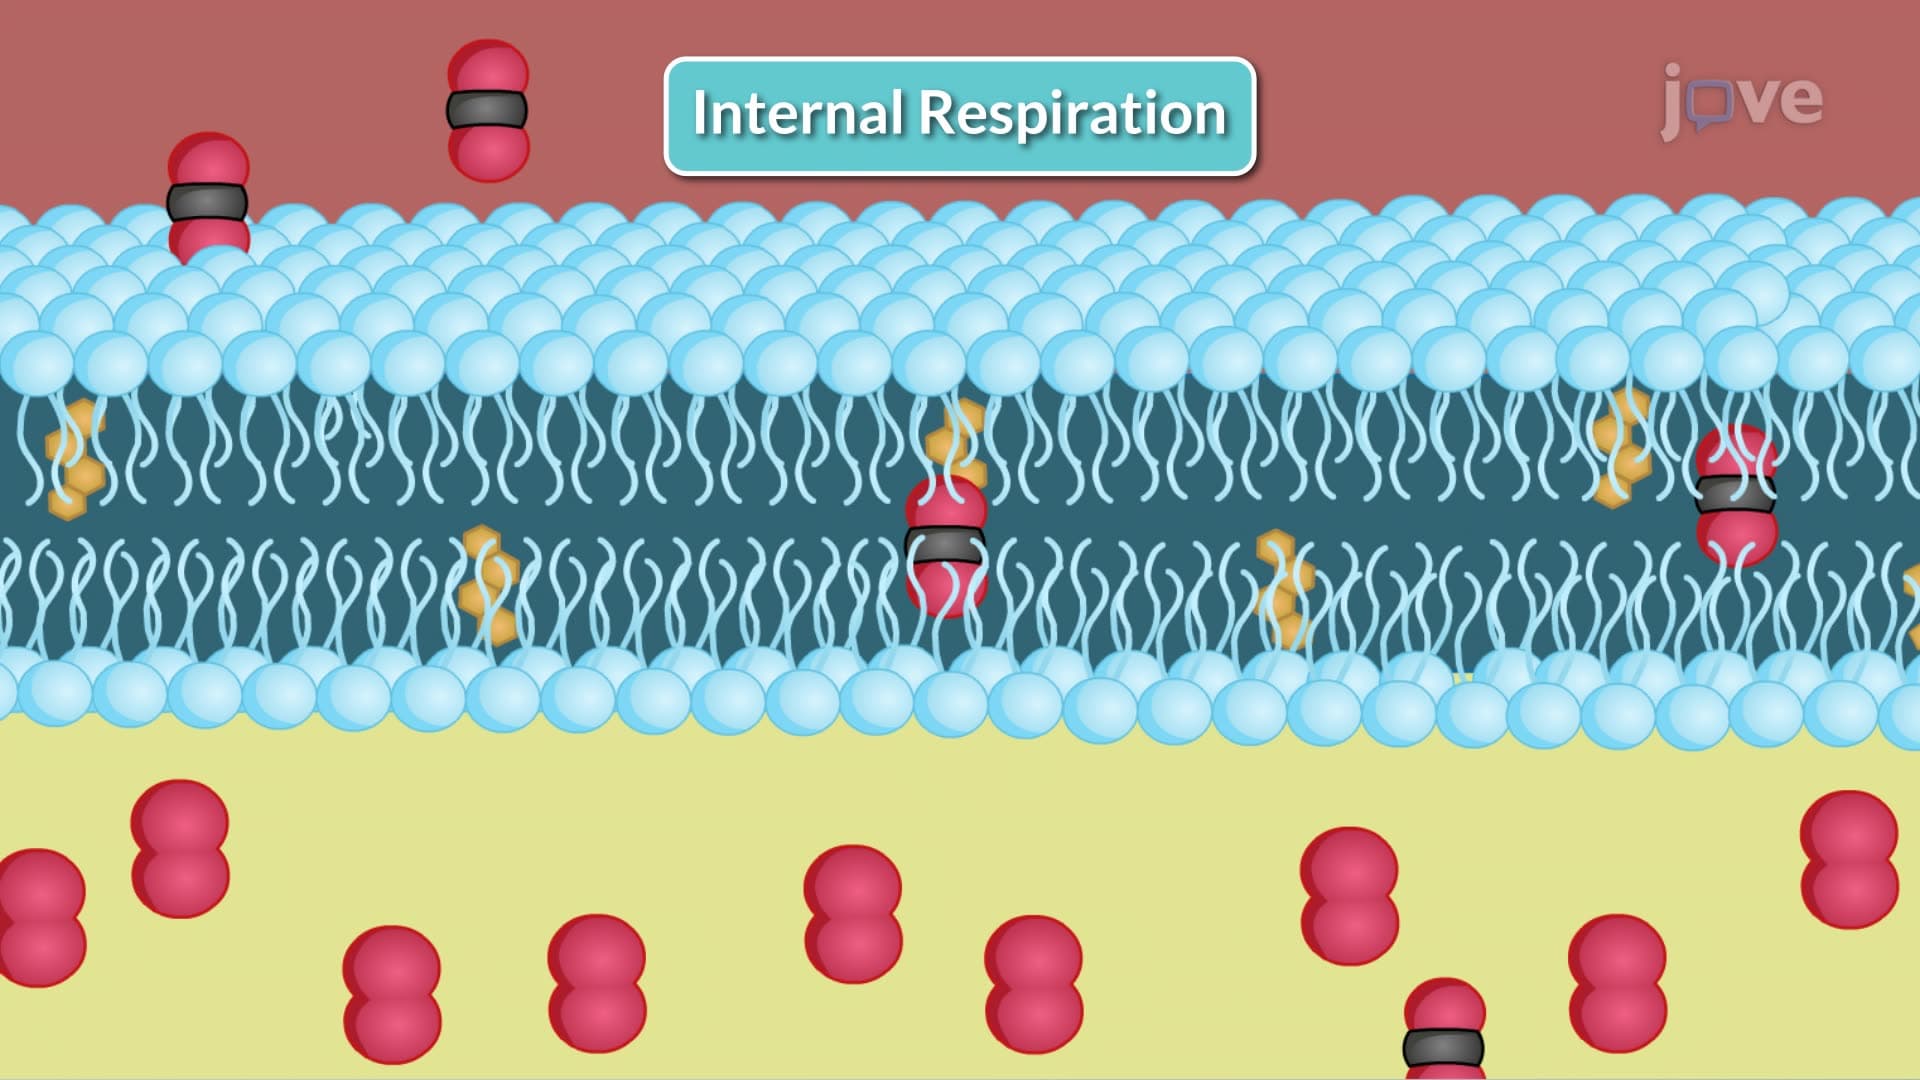
Respiration involves the exchange of gases, especially oxygen (O2) and carbon dioxide (CO2), between the alveoli and body cells, a process facilitated by blood circulation. As a result, the cardiovascular system, which involves the...
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...
 01:29
Oxygen Requirements and Growth Patterns