Related Experiment Video
Updated: Aug 16, 2026


Development of Compendium for Esophageal Squamous Cell Carcinoma
Published on: April 12, 2024
Cyclooxygenase-2 expression and cell proliferation are increased in MUC2-positive area of columnar-lined esophagus
1Department of Pathology, Dongguk University College of Medicine, Kyongbuk, Korea. taejung@mail.dongguk.ac.kr

Abstract:
Columnar-lined esophagus is composed of intestinal type and gastric type epithelium. Only the specialized or intestinal type columnar epithelium is susceptible to the development of esophageal adenocarcinoma. The aim of the present paper was to evaluate the expression of cyclooxygenase (COX) and microsomal prostaglandin E synthase (mPGES) in gastric-type and intestinal-type metaplasia in columnar-lined esophagus and compare these with cell proliferation. Biopsy specimens of 30 columnar-lined esophagus patients were collected, and immunohistochemistry was performed for secretory mucins (MUC2, MUC5AC), COX, mPGES and cell proliferation (Ki-67). The MUC2-positive area had higher COX-2 expression and cell proliferation than the MUC5AC-positive area. There was a close correlation between COX-2 expression and cell proliferation. In contrast, the expression of COX-1, mPGES-1 and -2 was similar between intestinal metaplasia and gastric metaplasia. In conclusion, intestinal-type columnar-lined esophagus possesses COX-2 expression and a higher proliferation potential, suggesting that esophageal adenocarcinoma may arise from specialized columnar-lined esophagus.

Related Concept Videos
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more similar...
 01:24
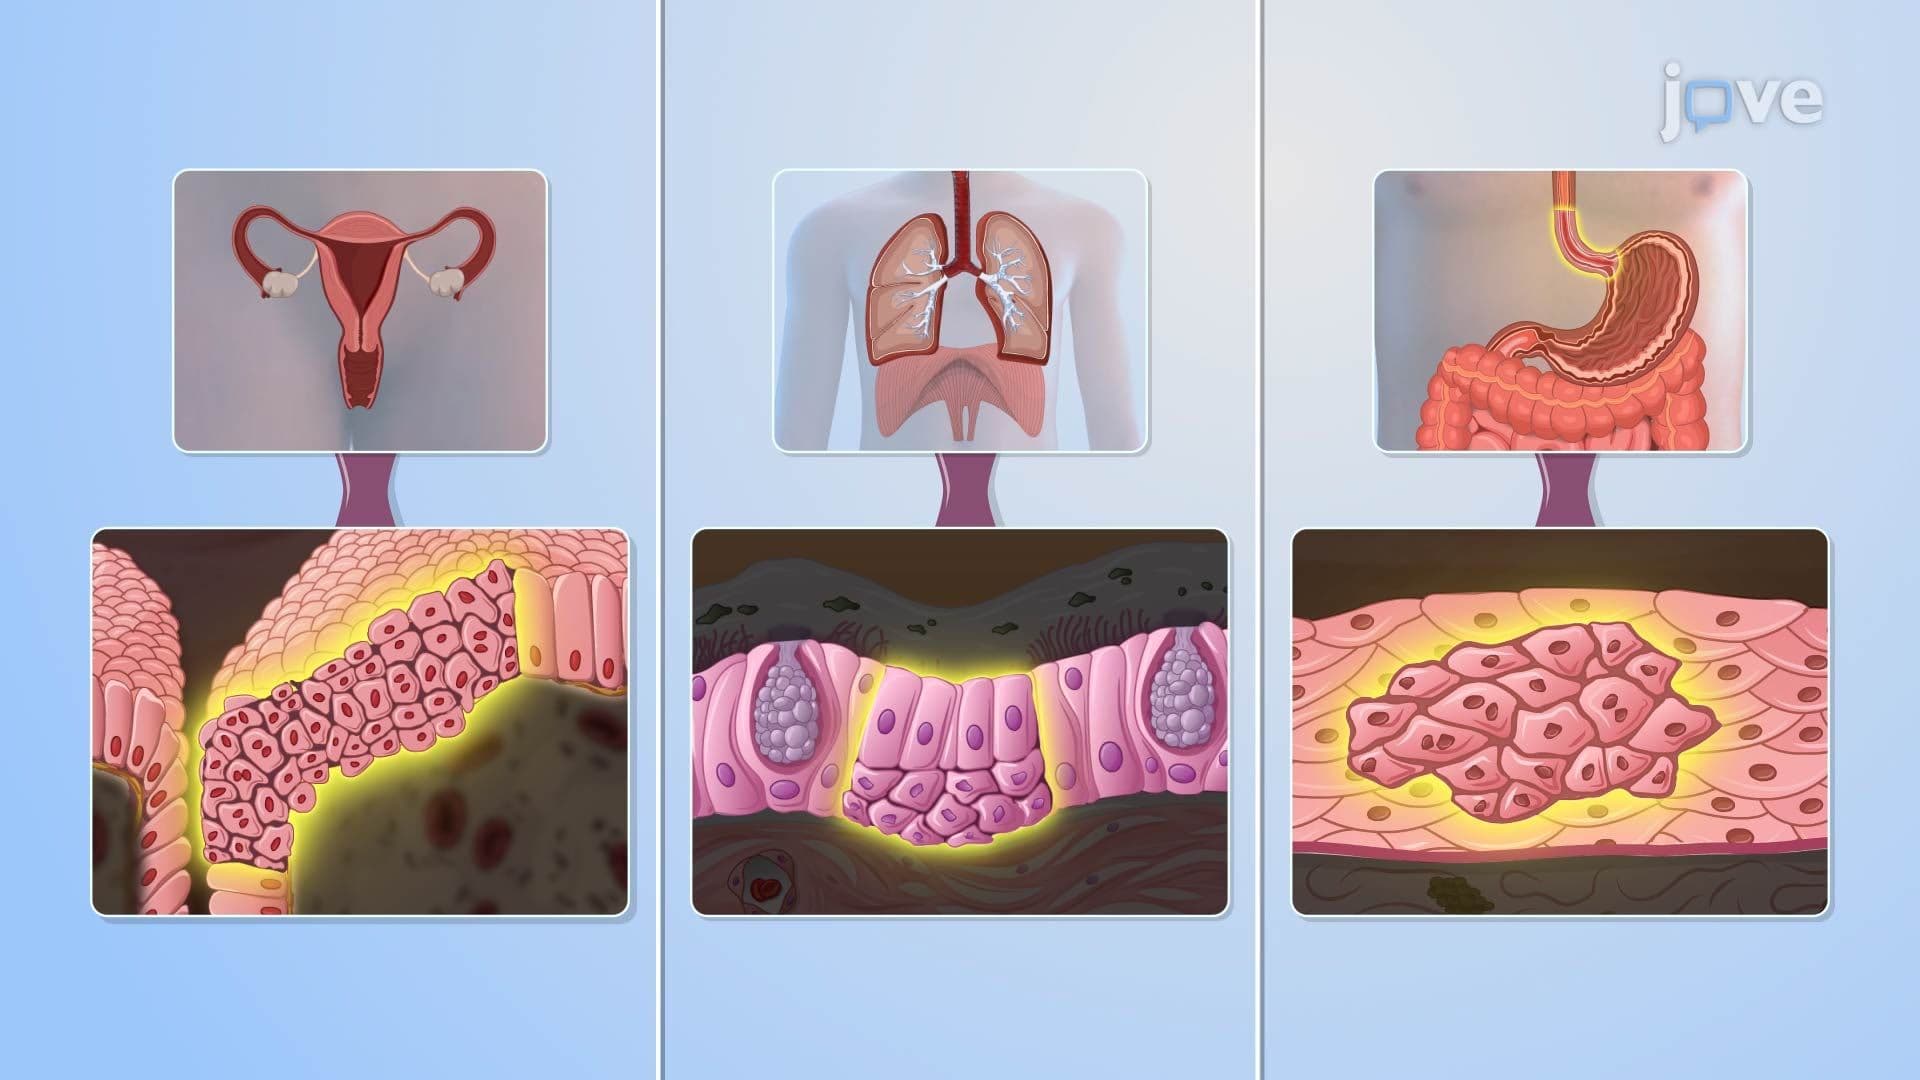
Cellular Adaptation IV: Dysplasia and Metaplasia
 01:23
Renewal of Intestinal Stem Cells
 01:26
Gastritis II: Pathophysiology
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...