Related Experiment Video
Updated: Aug 16, 2026

Laminar Flow-based Assays to Investigate Leukocyte Recruitment on Cultured Vascular Cells and Adherent Platelets
Published on: April 9, 2018
Platelet-leukocyte aggregates and derived microparticles in inflammation, vascular remodelling and thrombosis
Lilian McGregor1, Juliette Martin, John L McGregor
1INSERM IFR63-EA 3470, Faculty of Medicine RTH Laennec, Lyon, France.

As a result of vascular injury, activated platelets will rapidly interact with circulating platelets, via membrane glycoprotein complex alphaIIbbeta3 (GPIIb-IIIa) and fibrinogen, to form a thrombus or a plug preventing fatal bleeding. In addition, platelets interacting with ruptured atherosclerotic plaques or with the surface of diseased vessels can aggregate and induce ischemia that prevents blood flow. However, increasing evidence has also shown that circulating platelets interact with leukocytes and endothelial cells, via specific adhesion molecules, in inflammation, vascular remodelling and thrombosis. The aim of this chapter is to present the importance of cell-cell interactions involving platelets and leukocytes in events related to inflammation, coagulation, vascular remodelling and thrombosis. A key adhesion molecule implicated in platelet interaction with leukocytes is P-selectin, also known as CD62P. It is present on activated platelets and endothelial cells, and its counterpart on leukocytes is known as P-selectin glycoprotein ligand-1 (PSGL-1). A critical co-factor leading to leukocyte activation in platelet-monocyte aggregate formation is the presence of a chemokine known as RANTES. It acts in concert with platelet P-selectin and PSGL-1 in monocyte stimulation.
As a result of vascular injury, activated platelets will rapidly interact with circulating platelets, via membrane glycoprotein complex alphaIIbbeta3 (GPIIb-IIIa) and fibrinogen, to form a thrombus or a plug preventing fatal bleeding. In addition, platelets interacting with ruptured atherosclerotic plaques or with the surface of diseased vessels can aggregate and induce ischemia that prevents blood flow. However, increasing evidence has also shown that circulating platelets interact with leukocytes and endothelial cells, via specific adhesion molecules, in inflammation, vascular remodelling and thrombosis. The aim of this chapter is to present the importance of cell-cell interactions involving platelets and leukocytes in events related to inflammation, coagulation, vascular remodelling and thrombosis. A key adhesion molecule implicated in platelet interaction with leukocytes is P-selectin, also known as CD62P. It is present on activated platelets and endothelial cells, and its counterpart on leukocytes is known as P-selectin glycoprotein ligand-1 (PSGL-1). A critical co-factor leading to leukocyte activation in platelet-monocyte aggregate formation is the presence of a chemokine known as RANTES. It acts in concert with platelet P-selectin and PSGL-1 in monocyte stimulation.


Related Concept Videos
 01:18
Structure and Function of Platelets
Platelets are continually replenished, circulating in the bloodstream for 9-12 days before being removed by phagocytes, primarily in the spleen. A microliter of circulating blood contains between 150,000 and 450,000 platelets, with...
 01:22
Formation of the Platelet Plug
As the injured blood vessel contracts, endothelial cells undergo contraction, revealing collagen fibers in the basement membrane and underlying connective tissue. Furthermore, the plasma membrane of endothelial cells becomes adhesive, preparing the site for platelet adhesion. Platelets...
 01:38
Inflammation
 01:16
Clot Retraction and Fibrinolysis
 01:26
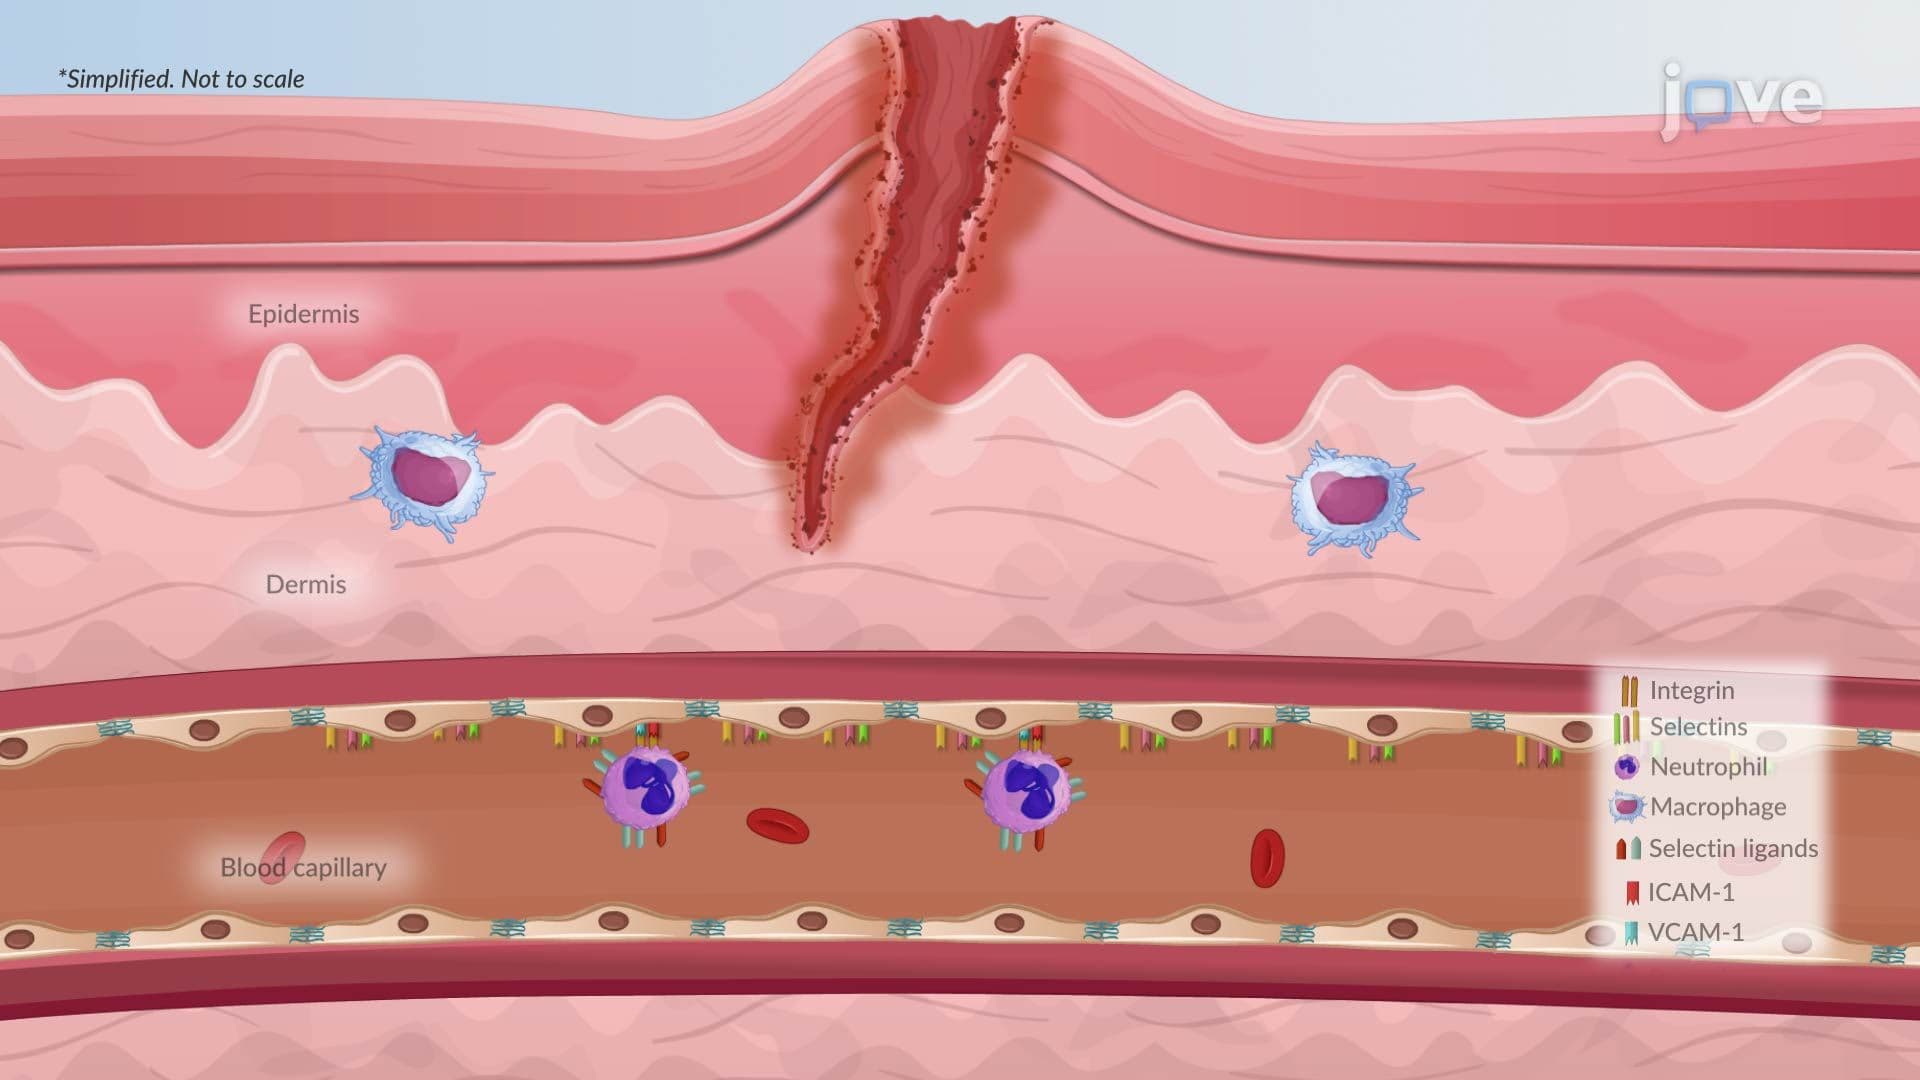
Acute Inflammation II: Cellular Phase
 01:25
Acute Inflammation III: Local and Systemic Effects