Related Experiment Video
Updated: Aug 16, 2026
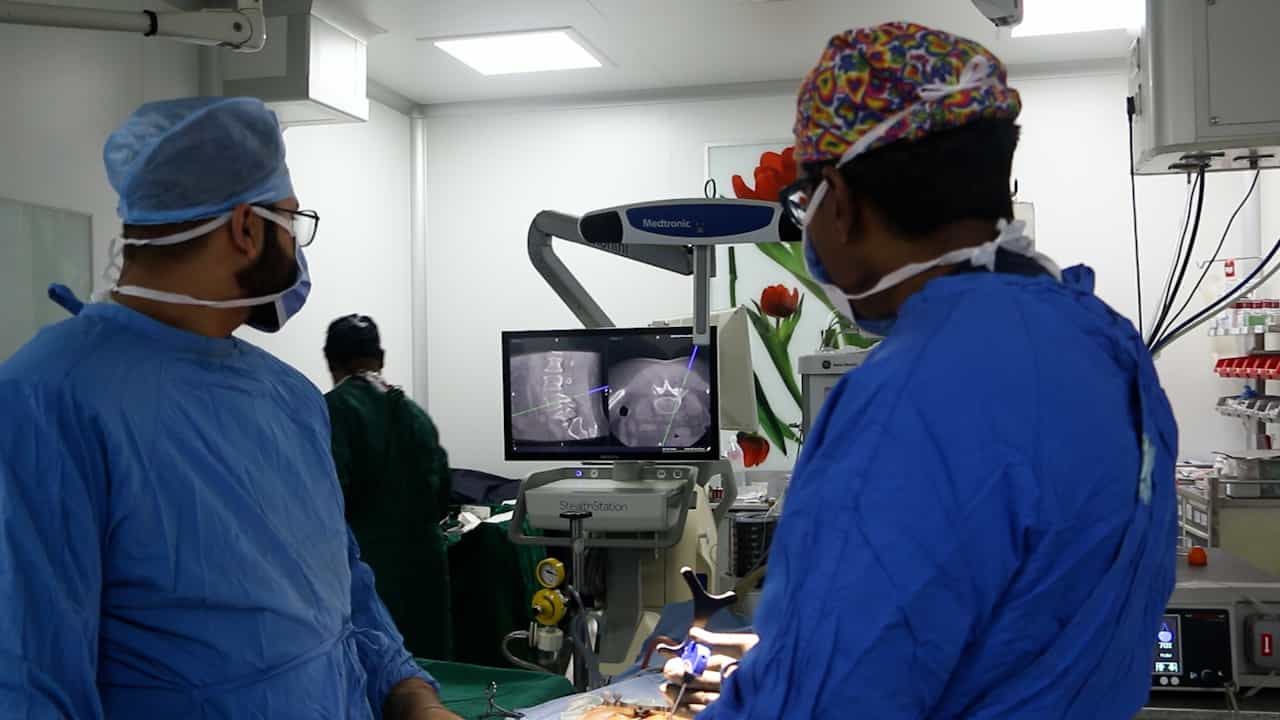

Optimizing Minimally Invasive Spine Surgery: A Fully 3D CT O-Arm Navigated Workflow in MIS TLIF
Published on: October 17, 2025
Medial canal fibrosis: surgical technique, results, and a proposed grading system
Vincent Yu-Wen Lin1, Gerard H Chee, Eytan A David
1Department of Otolaryngology, Sunnybrook and Women's College Health Science Center, Toronto, Ontario, Canada. vlin@sympatico.ca

Objective:
To report the hearing and surgical results in patients with medial canal fibrosis. To describe the surgical technique for removal of medial canal fibrosis and to propose a classification for grading postoperative surgical outcome and to correlate this with hearing results.
Setting:
Tertiary university referral center.
Study Design:
Retrospective case review.
Methods:
Twenty-one patients with mature medial canal fibrosis underwent a total of 26 operations at our institution from February 1994 to June 2003. Four patients underwent surgery for bilateral disease and another had a second operation for recurrence.
Results:
According to the proposed grading system, 10 (38.5%) of the 29 ears operated on achieved a Grade I result (normal self-cleaning ears) and three (11.5%) had recurrence (Grade III). One patient was found to have external ear canal cholesteatoma. Postoperatively, 15 ears demonstrated closure of the air-bone gap to within 10 dB or improvement on four-frequency average pure-tone audiogram to better than 25 dB. The mean preoperative air-bone gap was 28.7 dB compared with 12.5 dB postoperatively (p < 0.001). When hearing results were correlated with postoperative grade, 90.0% of the ears with a Grade I result had significant hearing improvement, 46.2% in patients with Grade II and 33.3% in patients with Grade III results. Four patients complained of temporomandibular joint pain postoperatively.
Conclusion:
Surgery remains the treatment of choice for mature medial canal fibrosis. With proper surgical technique and meticulous postoperative care, a patent and functioning external ear canal can be achieved in a majority of patients. Absence of recurrence does not equate with improved hearing thresholds.