Related Experiment Video
Updated: May 14, 2026

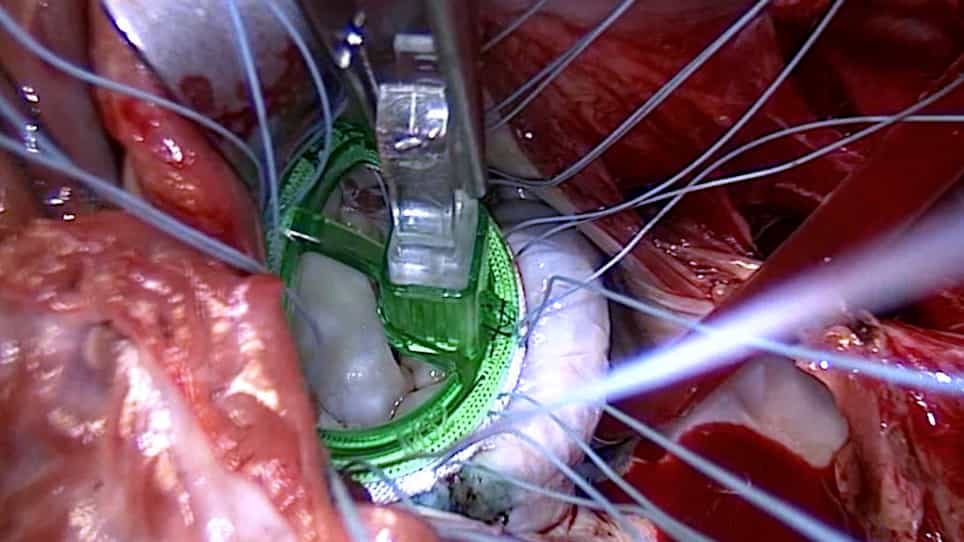
Implantation of the Syncardia Total Artificial Heart
Published on: July 18, 2014
Long-term results in patients with idiopathic dilated cardiomyopathy after weaning from left ventricular assist
Michael Dandel1, Yuguo Weng, Henryk Siniawski
1Department of Cardiothoracic and Vascular Surgery, Deutsches Herzzentrum Berlin, Berlin, Germany. dandel@dhzb.de

Insights
Weaning patients with idiopathic dilated cardiomyopathy from left ventricular assist devices (LVADs) is a viable option with good long-term outcomes. Echocardiography reliably predicts cardiac recovery and stability after LVAD explantation.
Area of Science:
- Cardiology
- Medical Devices
- Heart Failure Research
Background:
- Left ventricular assist devices (LVADs) have been used to treat idiopathic dilated cardiomyopathy (IDCM).
- Since 1995, 32 IDCM patients have been successfully weaned from LVADs in this department.
- Echocardiography during "off-pump" trials was crucial for weaning decisions.
Purpose of the Study:
- To assess the reliability of weaning criteria for IDCM patients based on long-term results.
- To evaluate the long-term cardiac function and survival rates after LVAD explantation in IDCM patients.
- To determine the predictive value of echocardiographic data for long-term cardiac stability post-weaning.
Main Methods:
- Evaluation of 32 IDCM patients weaned between March 1995 and March 2004.
- Assessment of cardiac function preservation and survival post-LVAD explantation.
- Review of echocardiographic data (LV end-diastolic diameter, LVEF) and patient history (HF duration) to identify risk factors for recurrence.
Main Results:
- Survival rate at 5 years post-explantation was 78.3%.
- Heart failure (HF) recurred in 31.3% within 3 years; most were successfully transplanted.
- Risk factors for early HF recurrence included LV end-diastolic diameter >55 mm, LVEF <45%, and HF history ≥5 years.
- Patients with no risk factors showed no recurrence; those with ≥2 risk factors had early recurrence.
- Echocardiographic changes (LVEF decrease) were noted within the first month in patients with HF recurrence.
Conclusions:
- LVAD weaning is a clinical option for selected IDCM patients with demonstrated cardiac recovery.
- Off-pump echocardiographic parameters are reliable for assessing LV recovery and predicting long-term stability.
- Consider LVAD weaning in IDCM patients showing cardiac recovery post-implantation.
Background:
Since our first successful left ventricular assist device (LVAD) explantation in a patient with idiopathic dilated cardiomyopathy (IDCM) in 1995, an additional 31 IDCM patients have been weaned in our department. Echocardiographic evaluations during repeated "off-pump" trials were the cornerstone for weaning decisions. After 9 years of experience, we assessed the reliability of our weaning criteria in light of the long-term results.
Methods And Results:
We evaluated all of the IDCM patients who were weaned between March 1995 and March 2004 with regard to preservation of cardiac function without LVAD support and survival after weaning. Additionally, we reviewed our echocardiographic data to assess their predictive value for long-term stability of cardiac function after weaning. The 32 weaned IDCM patients showed a survival rate of 78.3%+/-8.1 at 5 years after LVAD explantation. Heart failure (HF) recurred during the first 3 years after weaning in 31.3%. Only 2 patients died because of HF after weaning; the other patients with HF recurrence were successfully transplanted. Off-pump LV end-diastolic diameter >55 mm and/or LVEF <45% before LVAD removal, as well as history of HF > or =5 years before LVAD implantation, appeared to be major risk factors for early recurrence of HF. Patients without any of these 3 risk factors showed no HF recurrence during the first 3 years after weaning, but at the same time, all of those with at least 2 of these 3 risk factors developed early recurrence of HF. In patients with HF recurrence during the first 3 postweaning years, a significant LVEF decrease already occurred during the first month after weaning, whereas in those with long-term stable cardiac function even at the end of the sixth postweaning month, the LVEF was not different from that before LVAD removal.
Conclusions:
For selected patients with IDCM, weaning from LVADs is a clinical option with good results over >9 years and should, therefore, be considered in those with cardiac recovery after LVAD implantation. Off-pump echocardiographic data are reliable for the detection of LV recovery and prediction of long-term cardiac stability after weaning.

Related Concept Videos
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:29
Heart Failure II: Pathophysiology
 01:22
Heart Failure VI: Adjunct Therapies
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Cardiomyopathy V: Interprofessional Care