Related Experiment Video
Updated: Jun 23, 2026
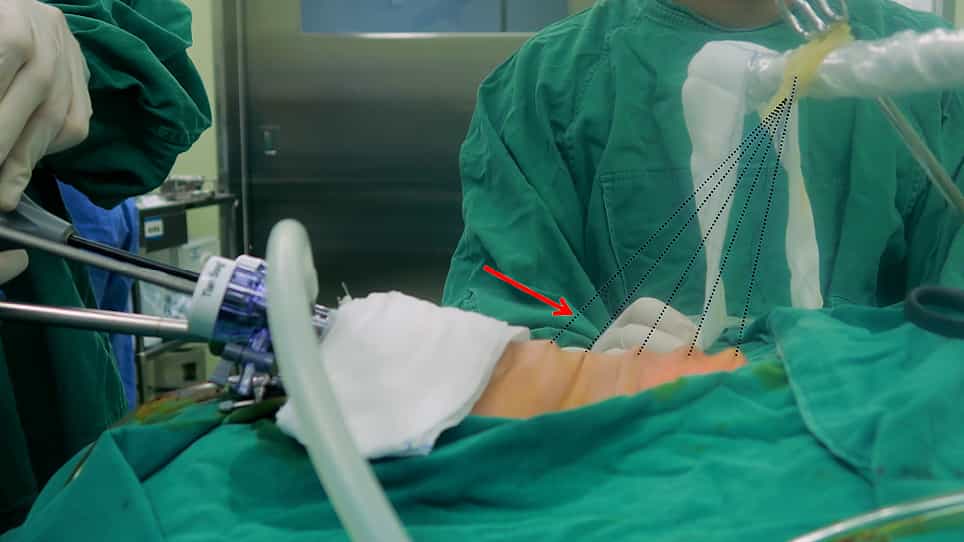

Transoral Endoscopic Thyroidectomy Vestibular Approach for Thyroid Lobectomy
Published on: May 12, 2023
Prophylactic thyroidectomy in multiple endocrine neoplasia type 2A
Michael A Skinner1, Jeffrey A Moley, William G Dilley
1Department of Surgery, Duke University School of Medicine, Durham, NC, USA.

Background:
Medullary thyroid carcinoma is the most common cause of death in patients with multiple endocrine neoplasia (MEN) type 2A (MEN-2A) or type 2B or familial medullary thyroid carcinoma. We sought to determine whether total thyroidectomy in asymptomatic young members of kindreds with MEN-2A who had a mutated allele of the RET proto-oncogene could prevent or cure medullary thyroid carcinoma.
Methods:
A total of 50 patients 19 years of age or younger who were consecutively identified through a genetic screening program as carriers of a RET mutation characteristic of MEN-2A underwent total thyroidectomy. Five to 10 years after the surgery, each patient was evaluated by physical examination and by determination of plasma calcitonin levels after stimulation with provocative agents.
Results:
In 44 of the 50 patients, basal and stimulated plasma calcitonin levels were at or below the limits of detection of the assay (proportion, 0.88; 95 percent confidence interval, 0.76 to 0.95). Two patients had basal and stimulated plasma calcitonin levels above the normal range. Stimulated plasma calcitonin levels had increased but remained within the normal range in four patients. The data suggest that there was a lower incidence of persistent or recurrent disease in children who underwent total thyroidectomy before eight years of age and in children in whom there were no metastases to cervical lymph nodes.
Conclusions:
In this study, young patients identified by direct DNA analysis as carriers of a RET mutation characteristic of MEN-2A had no evidence of persistent or recurrent medullary thyroid carcinoma five or more years after total thyroidectomy. A longer period of evaluation will be necessary to confirm that they are cured.
Insights
Total thyroidectomy in young patients with MEN-2A RET mutations prevented medullary thyroid carcinoma in most cases. Early surgery, before age eight, showed the best outcomes, suggesting a cure is possible.
Area of Science:
- Endocrinology
- Genetics
- Surgical Oncology
Background:
- Medullary thyroid carcinoma (MTC) is a leading cause of mortality in Multiple Endocrine Neoplasia (MEN) types 2A and 2B, and familial MTC.
- Early detection and intervention are crucial for managing MTC in at-risk individuals.
Purpose of the Study:
- To investigate the efficacy of total thyroidectomy in preventing or curing medullary thyroid carcinoma in asymptomatic young carriers of the RET proto-oncogene mutation associated with MEN-2A.
Main Methods:
- Fifty patients aged 19 or younger with a confirmed RET mutation for MEN-2A underwent total thyroidectomy.
- Post-operative evaluation included physical exams and stimulated plasma calcitonin level measurements 5-10 years after surgery.
Main Results:
- 88% of patients had undetectable calcitonin levels post-surgery.
- Two patients showed elevated calcitonin levels, and four had levels within the normal range but increased.
- Lower recurrence rates were observed in children operated on before age eight and those without lymph node metastases.
Conclusions:
- Total thyroidectomy in young, asymptomatic RET mutation carriers for MEN-2A appears to prevent persistent or recurrent medullary thyroid carcinoma.
- Long-term follow-up is required to definitively confirm a cure in these patients.
Related Concept Videos
 01:23
The Thyroid Gland
The follicles have a central cavity lined by simple cuboidal to squamous epithelial cells called follicular cells. These cells produce the glycoprotein...
 01:20
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:25
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:24
Graves Disease II: Pathophysiology
 01:23
Hypothyroidism II: Pathophysiology