Related Experiment Video
Updated: Aug 15, 2026
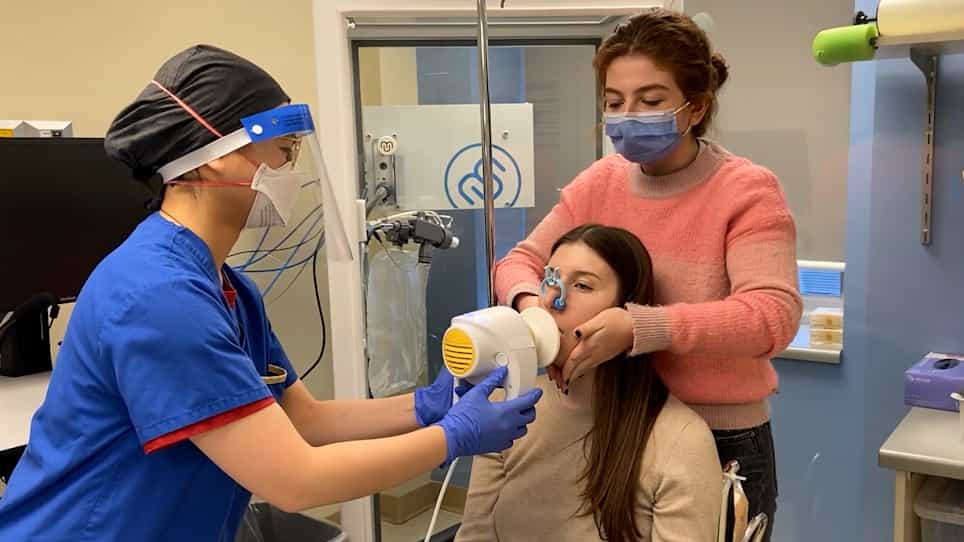

Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
Recognition of asthma in adolescents and young adults: which objective measure is best?
Charlotte Suppli Ulrik1, Dirkje S Postma, Vibeke Backer
1Department of Respiratory Diseases, Hvidovre Hospital, Copenhagen, Denmark. csulrik@dadlnet.dk

Background:
Objective assessment of airway function is important in epidemiologic studies of asthma to facilitate comparison between studies. Airway hyperresponsiveness (AHR), peak expiratory flow (PEF) variability, and bronchodilator reversibility (BR) are widely used as markers of airway lability in such studies. Data from a survey of a population sample of adolescents and young adults (n = 609; 288 males), aged 13-23 years, were analyzed to investigate whether AHR, PEF variability, and BR can be used interchangeably as markers of asthma in an epidemiological setting.
Methods:
Case history, including self-reported and doctor-diagnosed asthma, smoking habits, and use of asthma medication, was obtained by interview and questionnaire. Lung function, airway responsiveness (positive test: PC20 FEV1 < 16 mg/mL histamine), PEF variability (positive test: amplitude percentage mean > 20%), BR (positive test: deltaFEV1 [(FEV1max - FEV1min)/FEV1max) 100] > 10%), blood eosinophil count, and skin prick test reactivity were measured by using standard techniques.
Results:
The prevalence of a positive test was AHR 16.4%, PEFpos 13.3%, and BRpos 7.2%, respectively; 73.5% of the sample had three negative tests. Among the 74 participants with current self-reported asthma (12.2%), 34 subjects (46%) had more than one positive test. Using AHR as the only objective marker of asthma identified 93% of the participants with current asthma, whereas PEF and BR identified 45% and 10%, respectively. Confining the analysis to participants with only one positive test revealed that 61% of the subjects with isolated AHR had current asthma, whereas none of the subjects with isolated BRpos had asthma, and only one participant with isolated PEFpos had current asthma. Degree of histamine responsiveness was closer associated with other asthma-related factors, including self-reported asthma, use of asthma medication, and level of lung function, than PEF variability and bronchodilator responsiveness.
Conclusions:
Airway responsiveness to histamine, diurnal peak-flow variability, and bronchodilator reversibility cannot be used interchangeably as objective markers of asthma in epidemiologic studies. On the basis of the present findings, airway hyperresponsiveness to a nonspecific bronchoconstrictor is recommended as the objective marker of asthma-related airway lability.

Related Concept Videos
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:13
Asthma III: Clinical Manifestations
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like asthma or COPD,...
 01:30
Asthma-IV: Nursing Management
First, in...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:29
Asthma-I: Introduction