Related Experiment Video
Updated: Aug 15, 2026
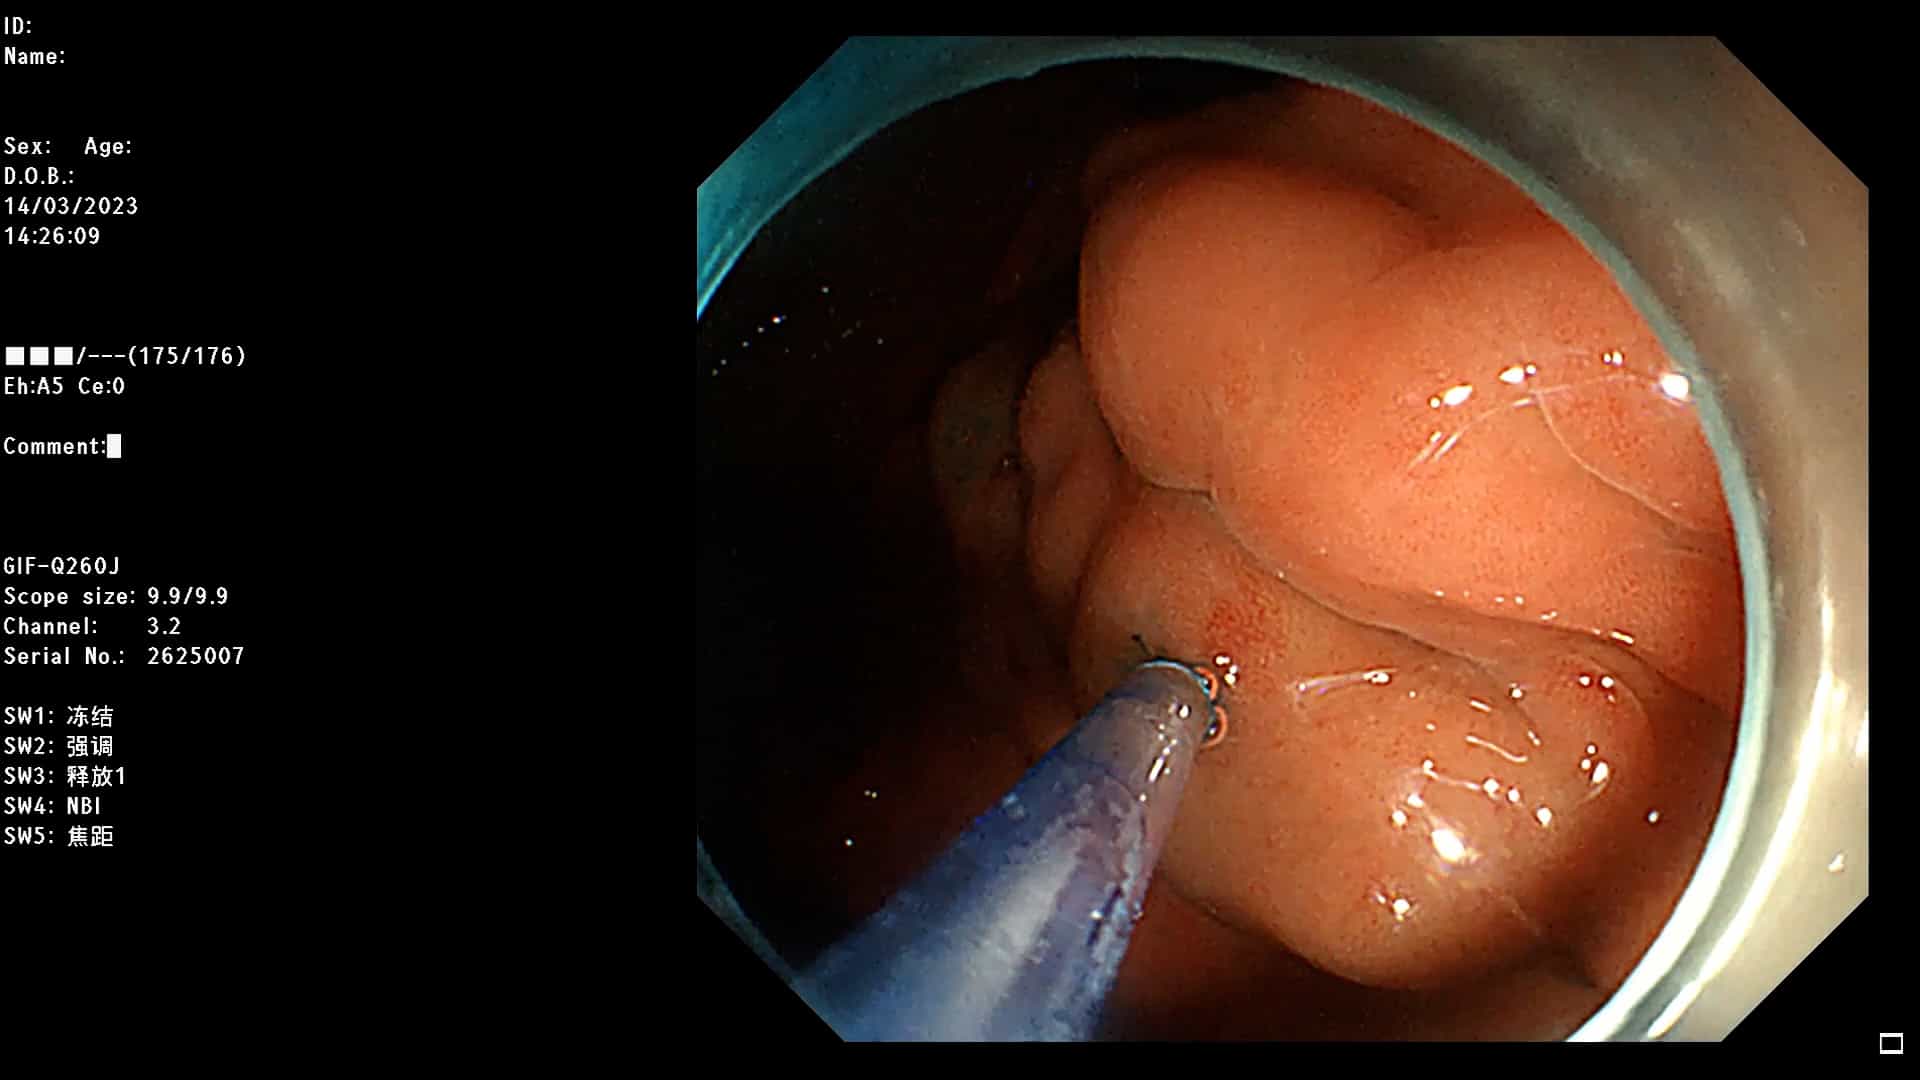
Endoscopic Injection Sclerotherapy Assisted by Cyanoacrylate and Clips for Gastroesophageal Varices
Published on: June 13, 2025
[Patient evolution in different stages of hepatic failure submitted to eradication of esophageal varices with
Elisa Estela Caldera1, Angel Andrés Reyes Dorantes, Julio Alberto González Ortiz
1Residente de Endoscopia, Becaria de la República de Nicaragua.

Insights
Endoscopic band ligation effectively eradicates esophageal varices in all hepatic failure stages. However, patients with advanced liver disease (Child Pugh C) require more sessions and have higher risks of recurrence and complications.
Area of Science:
- Hepatology
- Gastroenterology
- Endoscopic procedures
Context:
- Esophageal varices are a serious complication of advanced liver disease.
- Bleeding from esophageal varices has high mortality.
- Endoscopic band ligation is a primary treatment for esophageal varices.
Purpose:
- To evaluate the efficacy and safety of endoscopic band ligation for esophageal varices eradication.
- To assess patient progress across different stages of hepatic failure (Child Pugh classification).
- To compare outcomes based on Child Pugh class.
Summary:
- A prospective study of 124 patients with esophageal varices treated with endoscopic band ligation.
- 100% eradication was achieved, but more sessions were needed for Child Pugh C patients.
- Recurrence, rebleeding, and complications like gastropathy were more frequent in Child Pugh C patients.
Impact:
- Endoscopic band ligation is effective regardless of hepatic reserve.
- Treatment requires tailoring to hepatic function, with closer monitoring for advanced disease.
- Understanding complication rates informs patient management and follow-up strategies.
Objective:
To know the patients' progress with distinct stages of hepatic failure, according to the Child Pugh classification, who underwent esophageal varices eradication with the use of endoscopic band ligation.
Design:
Descriptive, longitudinal, prospective and comparative study. CENTRE: Endoscopy Department of the Central Military Hospital, Mexico, D.F.
Methods:
One-hundred twenty-four patients with esophageal varices and a history of bleeding, were submitted to various band ligation sessions every 4 weeks until the varices were eradicated and control sessions every 3 months.
Results:
A total of 425 endoscopy sessions were performed of which 239 were ligature applications and 187 control sessions. Eradication of varices was achieved in 100% of the patients. Of the Child A, 2/3 of them were eradicated in one session and the other 1/3 with 2 sessions. The patients of the Child B class, 66% of varices were effaced in one session, 22% in two and 12% in three sessions. In the Child C group, 50% were obliterated in two sessions, 47% with three, 2% needed 4 sessions. The follow-up period was from 4 months being the minimum and 13 months the maximum (mean of 7 months). In 15% of the patients varices recurred. None were from the Child A group. Those pertaining to the Child B group varices reappeared in 7.3% of which 2/3 required another ligation session to eradicate them once again and the other 1/3 were removed in two sessions. In the Child C group the incidence of recidivation was 28%, 43% of these needing one session to eliminate them once again, 50% two sessions and 7% three sessions for complete eradication. Rebleeding appeared in 7.7% of the sample, all of them were from the Child C class. The occurrence of congestive gastropathy before ligature was 42%, and 73% at the conclusion of the follow-up period. Congestive gastropathy developed in 11% of the Child A patients after eradication, 34% of the Child B group and 38.5% of the Child C group. The incidence of gastric varices was 21% before ligature and at the end of the follow-up period 17% more developed gastric varices. None of the Child A patients developed gastric varices, 12% of group B and 24% of group C. From the (n = 124) 22.5% presented dysphagia as a complication which lasted less than one week and in 0.8% mucosal ulcer
Conclusion:
It is possible to eradicate esophageal varices by band ligation independently of the hepatic function reserve. A greater number of sessions is required to eradicate varices in the poor hepatic function group and the incidence of recidivation, rebleeding, and complications that developed such as gastric varices and gastropathy are more frequent in patients with poor hepatic function reserve.
More Related Videos
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:24
Esophageal Varices-I: Introduction
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care