Related Experiment Video
Updated: Jul 20, 2026


Drug-Induced Sleep Endoscopy (DISE) with Target Controlled Infusion (TCI) and Bispectral Analysis in Obstructive Sleep Apnea
Published on: December 6, 2016
Comparison of pleural pressure and transcutaneous diaphragmatic electromyogram in obstructive sleep apnea syndrome
Riccardo A Stoohs1, Hans-Christian Blum, Lennart Knaack
1Zentrum für Schlafmedizin und Schlafstörungen GbR, Dortmund Sleep Disorders Center Dortmund, Germany. rastoohs@somnolab.de

Study Objectives:
Based on studies of the impact of esophageal pressure on cardiovascular variables during sleep, this signal can be used to refine the severity level in the clinical diagnosis of obstructive sleep apnea syndrome. We hypothesized that relative changes in diaphragmatic electromyogram (EMG) can reflect short-term changes in esophageal pressure durng obstructive apneas and hypopneas.
Design:
Diaphragmatic EMG was sampled at 0.25 kHz; diaphragmatic EMG waveform was band-pass filtered and digitally converted; the electrocardiogram artifact was eliminated; using a gating procedure, the waveform was fast-Fourier transformed and digitally rectified; and a moving average of 200 milliseconds was calculated. For each inspiratory effort during apnea or hypopnea, we calculated maximum diaphragmatic EMG and esophageal pressure. Data were normalized calculating the percentage difference between the first obstructed and each subsequent inspiratory effort during the respiratory event.
Setting:
Sleep disorders laboratory.
Patients:
9 patients with moderate obstructive sleep apnea syndrome presenting with apneas and hypopneas during sleep.
Intervention:
None.
Measurements And Results:
861 respiratory events were scored, and the evolution between esophageal pressure and diaphragmatic EMG were compared. Normalized data showed a good correlation between the 2 measures during apneas and hypopneas. There was a significant difference between the percentage increase in esophageal pressure and diaphragmatic EMG for apneas and hypopneas (esophageal pressure, apnea: 118.1% +/- 118.5%, hypopnea: 76.1% +/- 74.3%, P = .000; diaphragmatic EMG, 123.5% +/- 131.7%, hypopnea: 73.3% +/- 74.2%, P = .000). No significant differences for apnea or hypopnea were noted between the 2 measures under investigation.
Conclusion:
Diaphragmatic EMG may be clinically useful to describe relative changes in respiratory effort under conditions of apnea and hypopnea during sleep and to reliably dissociate central from obstructive events where esophageal pressure monitoring is not readily available.


Related Concept Videos
 01:17
Measurement of Blood Pressure
 01:24
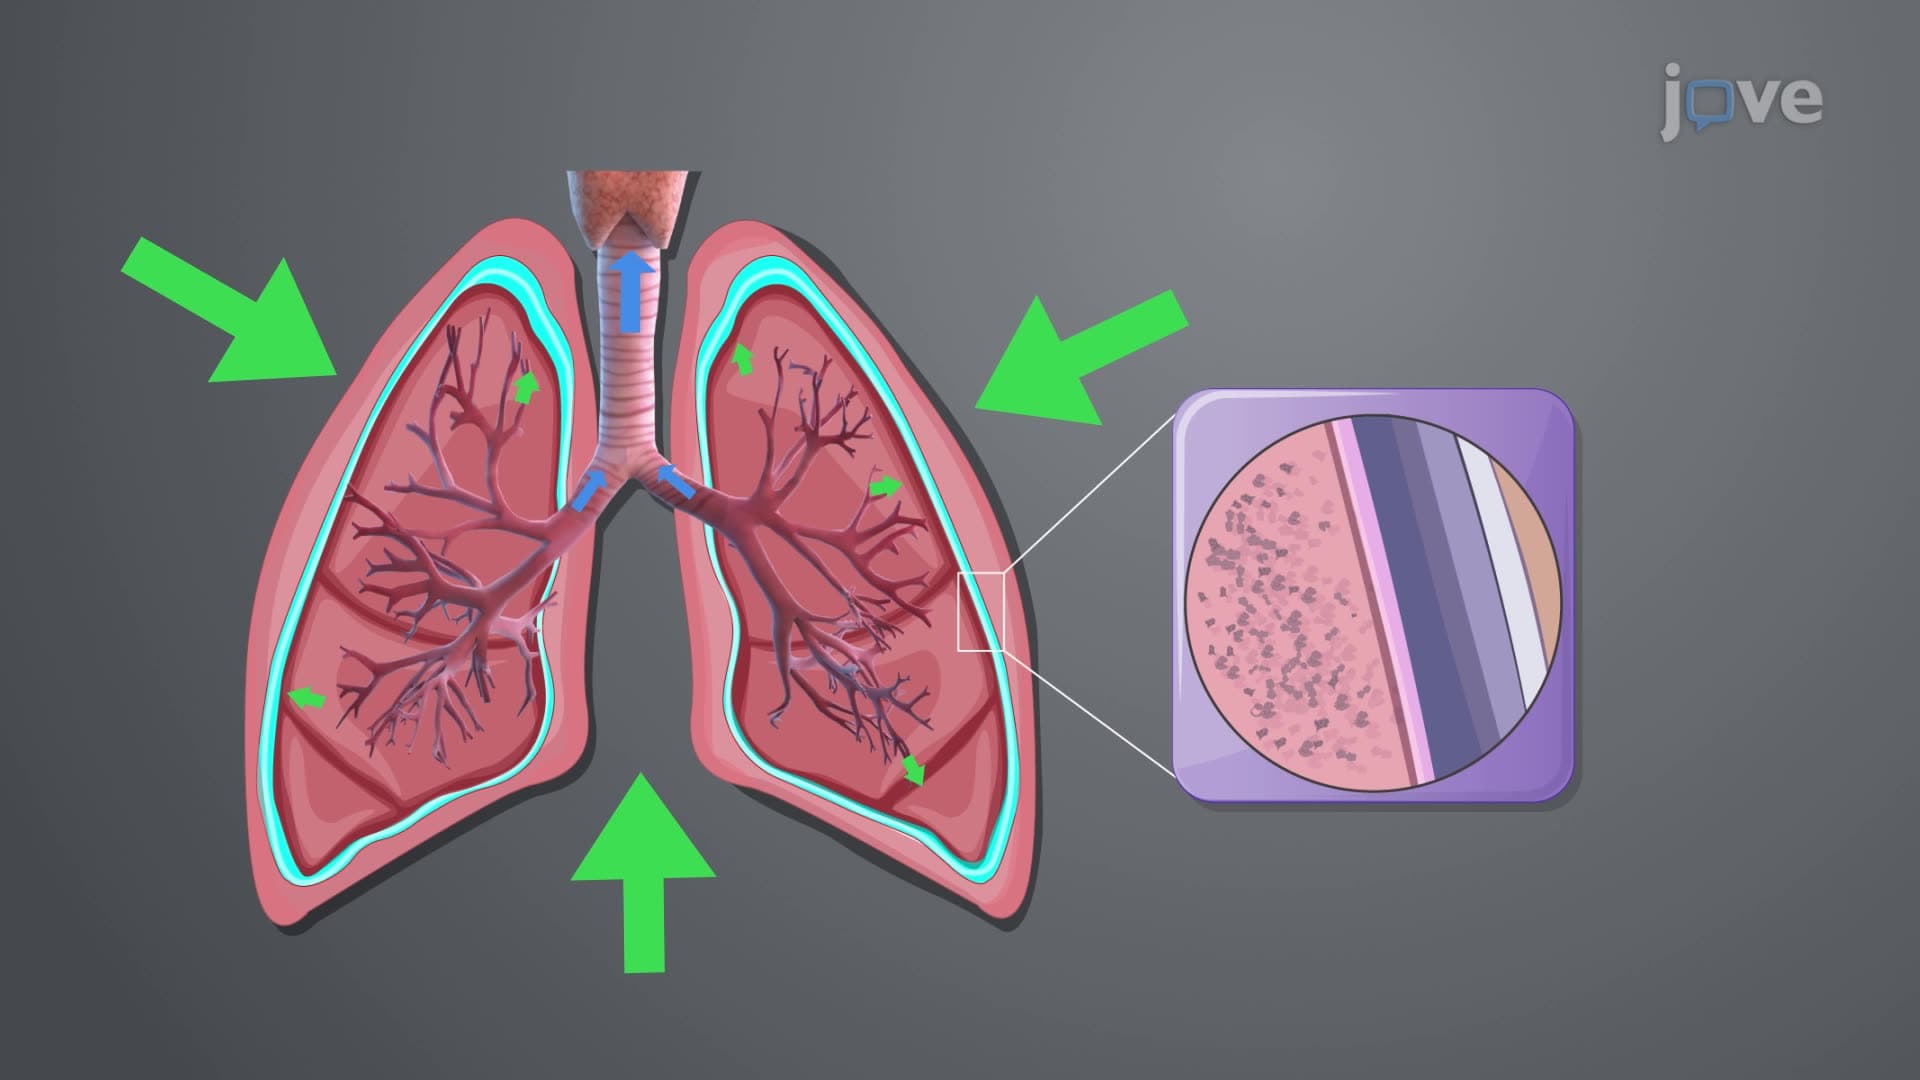
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs during...
 01:24
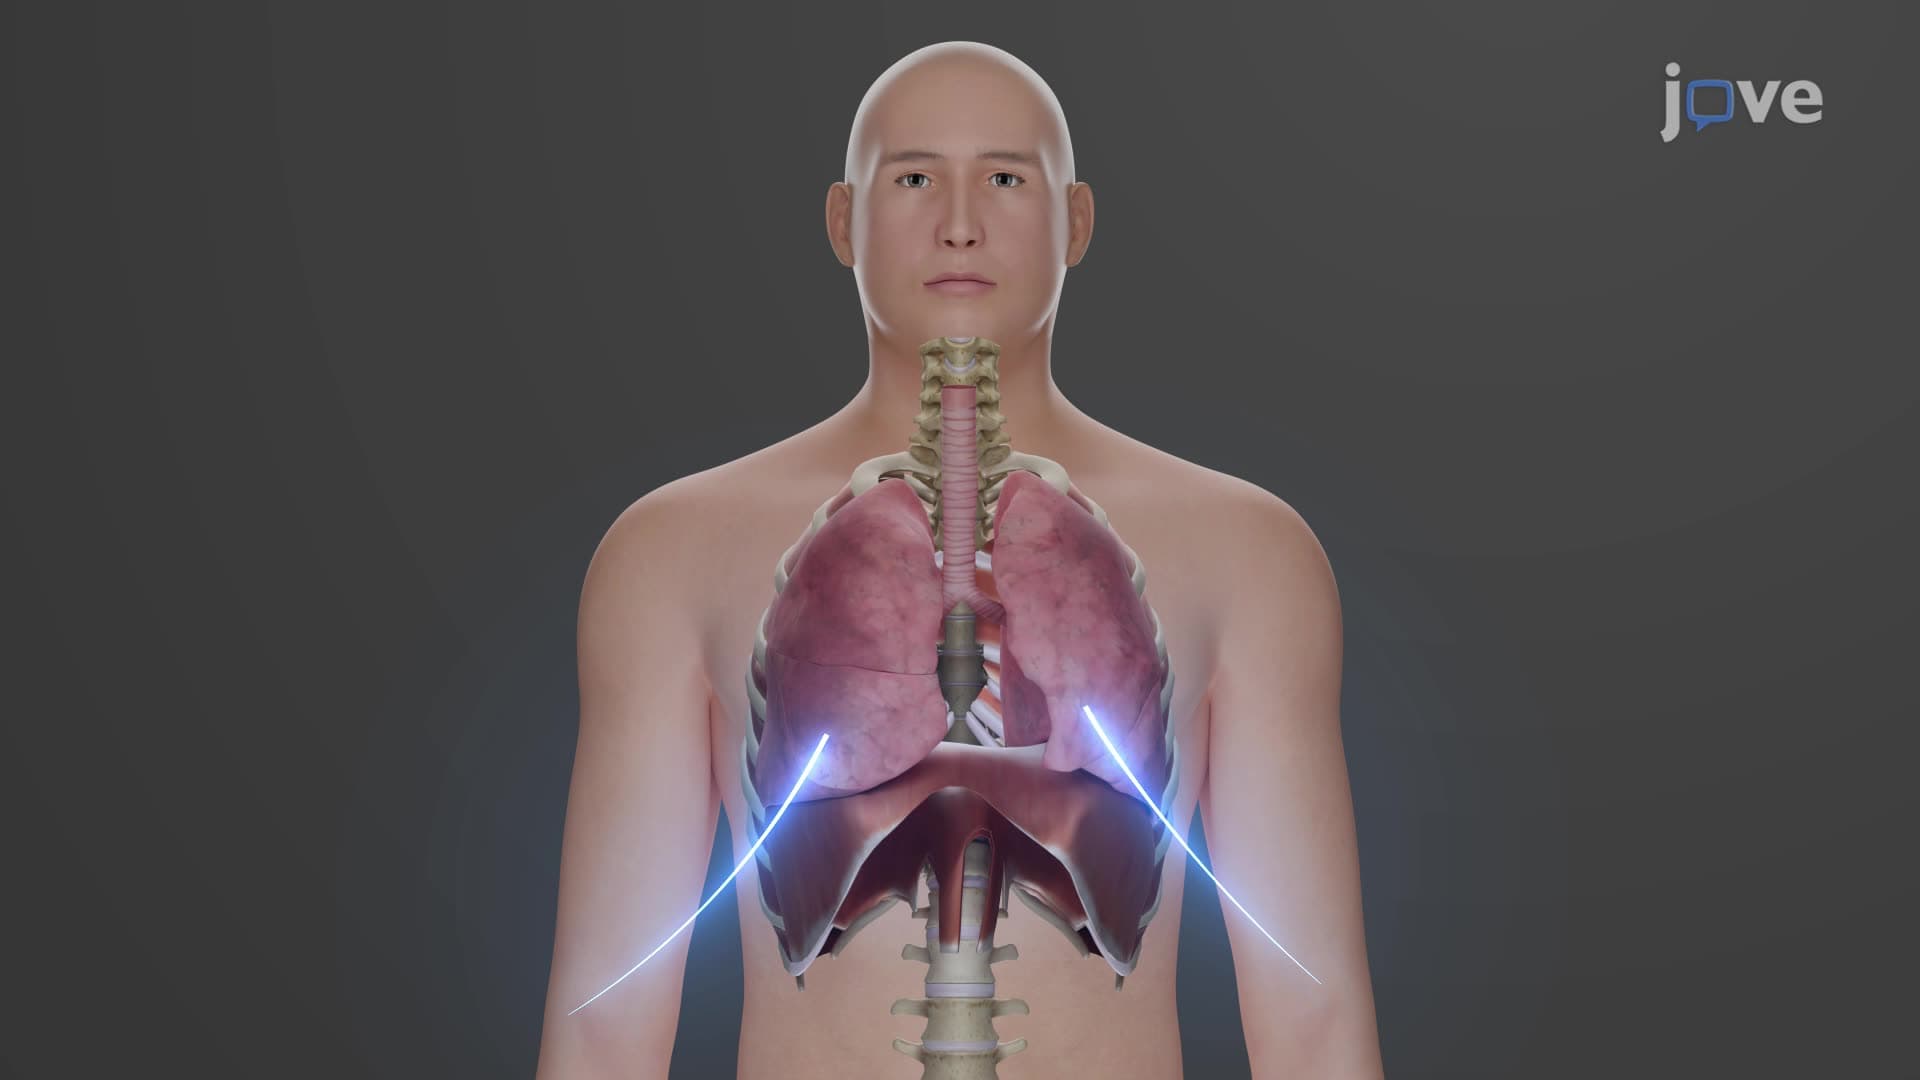
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...
 01:29
Physical Assessment of the Respiratory Tract III: Percussion
Percussion in Respiratory Assessment
Percussion evaluates underlying tissue composition with audible and tactile vibrations,...
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:21
Sleep Apnea
The condition is more prevalent among...