Related Experiment Video
Updated: Aug 15, 2026

Reprogramming Pancreatic Ductal Adenocarcinoma to Pluripotency
Published on: February 2, 2024
Ductal neoplasia of the pancreas: nosologic, clinicopathologic, and biologic aspects
Nazmi Volkan Adsay1, Olca Basturk, Jeanette D Cheng
1The Karmanos Cancer Institute, Harper University Hospital, Wayne State University, Detroit, MI 48201, USA. adsayv@med.wayne.edu

Abstract:
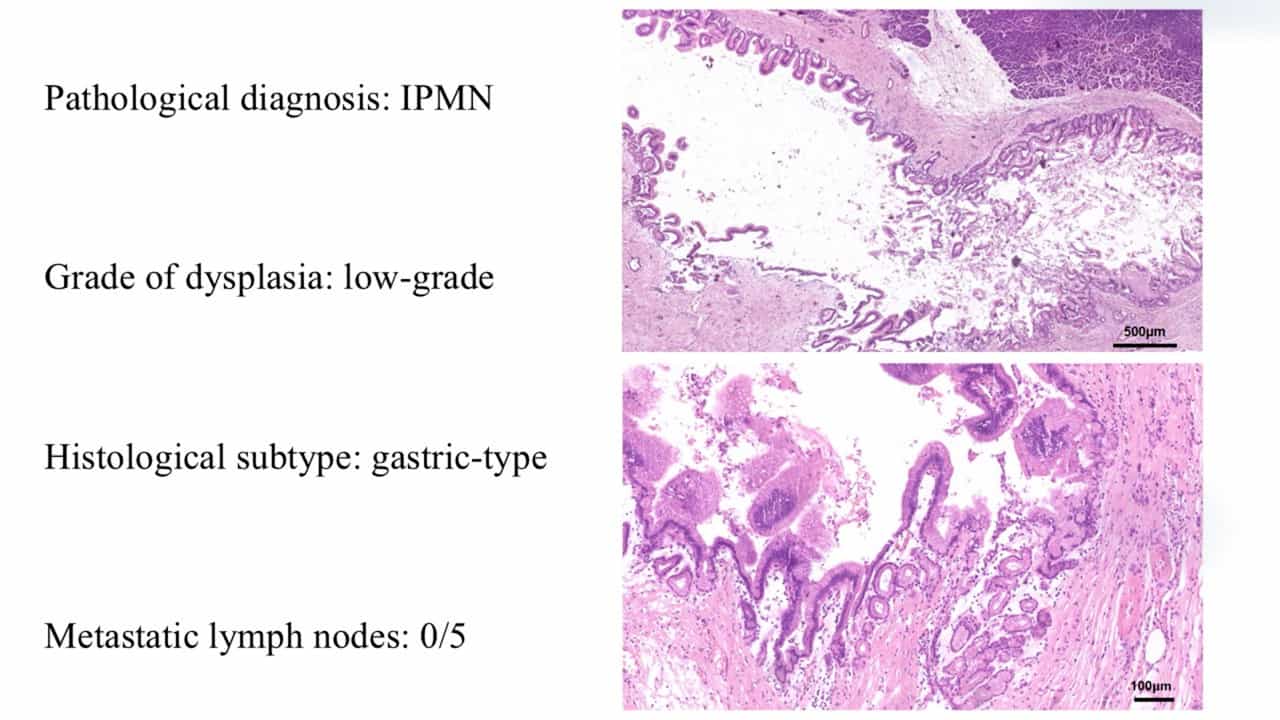
Most pancreatic neoplasia are of ductal lineage, characterized by tubule (gland), cyst, papilla, or mucin formation and expression of mucin-related glycoproteins and oncoproteins (eg, MUC1, CA19-9, CEA, DUPAN), as well as some subsets of cytokeratin (eg, CK19). Mutations of k-ras oncogene and DPC4 are also common in ductal neoplasia and generally not seen in nonductal tumors. A variety of pancreatic neoplasia fall under the heading of ductal neoplasia. Invasive ductal adenocarcinoma (DA) is the most important and constitutes the vast majority (>85%) of pancreatic tumors. DA is characterized by insidious infiltration and rapid dissemination, despite its relatively well-differentiated histologic appearance. In some variants of DA such as undifferentiated or sarcomatoid, evidence of ductal differentiation may be lacking or only focal. The presumed precursors of DA are microscopic intraductal proliferative changes that are now termed pancreatic intraepithelial neoplasia (PanIN). PanINs comprise a neoplastic transformation ranging from early mucinous change (PanIN-1A) to frank CIS (PanIN-3). A similar (in situ) neoplastic spectrum also characterizes intraductal papillary mucinous neoplasms and mucinous cystic neoplasms, which are cystic ductal-mucinous tumors with varying degrees of papilla formation, and may be associated with invasive carcinoma. As such, these can be regarded as mass-forming preinvasive neoplasia. Some intraductal papillary mucinous neoplasms are associated with invasive carcinoma of the colloid type. Colloid carcinoma of the pancreas appears to be a clinicopathologically distinct tumor with indolent behavior. Whereas most ductal pancreatic neoplasia are characterized by some degree of mucin formation, serous tumors, of which serous (microcystic) adenoma is the sole example, lack mucin formation, presumably because they recapitulate centroacinar ducts. They are typically benign tumors. It is recognized now that pancreatic carcinoma, like other malignant processes, is a genetic disease produced by progressive mutations in cancer-related genes. These alterations can be categorized as "early" such as k-ras mutation, HER-2/neu, PSCA, MUC5, and fascin overexpression; "intermediate" such as p16 inactivation, MUC1, and cyclin D1 overexpression; and finally as "late" such as p53 and DPC4 inactivation, BRCA2 mutation, and overexpression of ki-67, 14-3-3sigma, and mesothelin. Ductal neoplasia is the most important category among pancreatic tumors. It is important to appreciate the different types of ductal tumors because they vary greatly in their clinicopathologic characteristics and prognosis. Understanding the molecular mechanisms of ductal carcinogenesis will help develop more efficient prevention and therapy of these tumors.
Related Concept Videos
 01:21
Chronic Pancreatitis II: Pathophysiology
 01:25
Chronic Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:26
Type I Diabetes II: Pathophysiology
 01:24
Cellular Adaptation IV: Dysplasia and Metaplasia
 01:24
Type II Diabetes II: Pathophysiology