

The role of dydrogesterone in recurrent (habitual) abortion
Christian J Gruber1, Johannes C Huber
1Department of Gynecologic Endocrinology and Reproductive Medicine, Vienna University School of Medicine, Währinger Gürtel 18-20, A-1090 Vienna, Austria. christian.gruber@chello.at

Abstract:
The published evidence regarding the administration of dydrogesterone in the treatment of habitual abortion is summarised in this review. Habitual abortion is defined as the loss of three or more consecutive pregnancies without known maternal or foetal pathology. The immunology of early pregnancy seems to determine the rejection or non-rejection of the allogenic embryo. When peripheral mononuclear cells from recurrent aborters are incubated with progesterone or dydrogesterone in vitro, T-helper (Th)2 cytokines such as interleukin (IL)-4 and IL-6 markedly increase whereas the Th1 cytokine interferon-gamma decreases. Additionally, both progesterone and dydrogesterone are thought to inhibit the activity of natural killer cells at the foeto-maternal interface in humans. Progesterone-induced blocking factor (PIBF) mediates the immunological effects of progesterone and dydrogesterone in pregnancy. It affects various phases of the maternal immune response involving both the cellular and humoral immune system, exerts anti-abortive effects and inhibits the release of arachidonic acid. It also favours the production of so-called asymmetric, pregnancy-protecting antibodies. In rodents, blockade of this factor results in the termination of pregnancy and in women considerably lower levels are found in those with threatened abortion or pre-term labour. In order to draw final conclusions as to the usefulness of dydrogesterone in women with a history of recurrent miscarriage, further controlled, blinded, randomised clinical trials are needed.
Related Concept Videos
 01:27
Ovarian Cycle
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:21
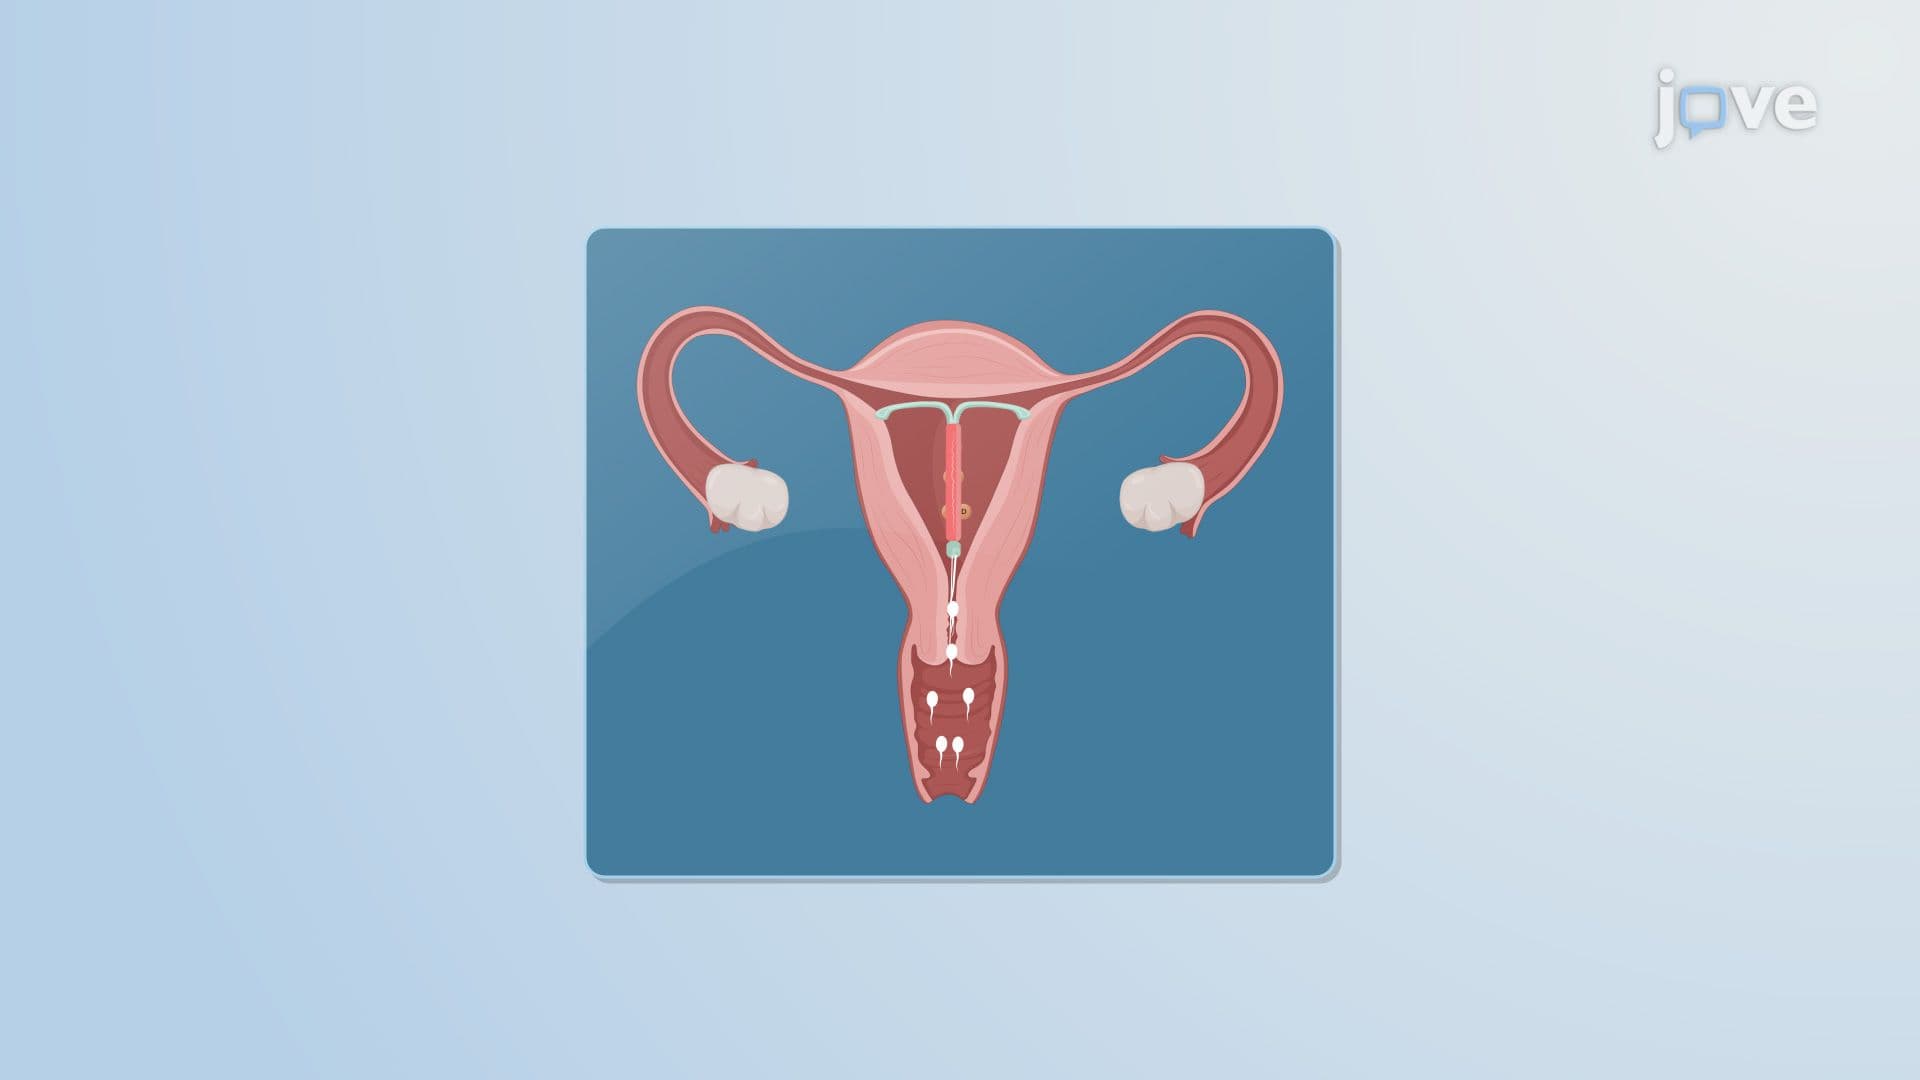
Intrauterine Drug Delivery Systems
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:17
Drugs for Treatment of Diarrhea-Predominant IBS
Two specific drugs used in the treatment are alosetron (Lotronex) and eluxadoline (Viberzi). Alosetron, a 5-HT3 antagonist, works by slowing the movement of stools in the gut, reducing bowel...
 02:07
Oogenesis