Low-dose intrathecal morphine does not delay early extubation after cardiac surgery
Related Experiment Video
Updated: Aug 15, 2026

Non-Intubated Video-Assisted Thoracoscopic Surgery
Published on: May 26, 2023
Eric Jacobsohn1, Trevor W R Lee, Ryan J Amadeo
1Department of Anesthesia and Cardiothoracic Surgery, Washington University School of Medicine, Campus Box 8054, St. Louis, MO 63110, USA. jacobsoe@msnotes.wustl.edu

Purpose:
This study was designed to examine the efficacy of low-dose intrathecal morphine (ITM) on extubation times and pain control after cardiac surgery.
Methods:
43 patients undergoing elective cardiac surgery were enrolled in this prospective, randomized, double-blind placebo controlled trial. Patients were given a pre-induction dose of ITM (6 microg x kg(-1) per ideal body weight in 5 mL normal saline, group ITM) or 5 mL of intrathecal normal saline (group ITS). Anesthesia was induced with thiopental (3 mg x kg(-1)), sufentanil, midazolam and rocuronium. The total allowable doses of sufentanil and midazolam for the entire case were limited to 0.5 microg x kg(-1) and 0.045 mg x kg(-1) respectively. Anesthesia was maintained with isoflurane before and during cardiopulmonary bypass (CPB), and with propofol after CPB. In the postanesthesia care unit, patients received nurse-administered morphine followed by patient-controlled analgesia morphine. Serial visual analogue scale pain scores, morphine use, mini-mental state examinations and pulmonary function tests were measured for 48 hr. Patient satisfaction questionnaires were completed at the time of discharge.
Results:
Mean times to extubation from the application of dressings were short and did not differ between groups (ITM = 41.4 +/- 33.0 min, ITS = 39.2 +/- 37.1 min). During the first 24 hr postoperatively, the ITM group had improved pain control and a lower iv morphine requirement than the control group, both at rest and during deep breathing. Both forced expiratory volume in one second and forced vital capacity were improved in the ITM group. There were no differences in spinal-related side effects or in the overall complication rates. Patient satisfaction was high in both groups.
Conclusion:
Low-dose ITM for cardiac surgery did not delay early extubation, but it improved postoperative analgesia and pulmonary function.
Related Concept Videos
 01:29
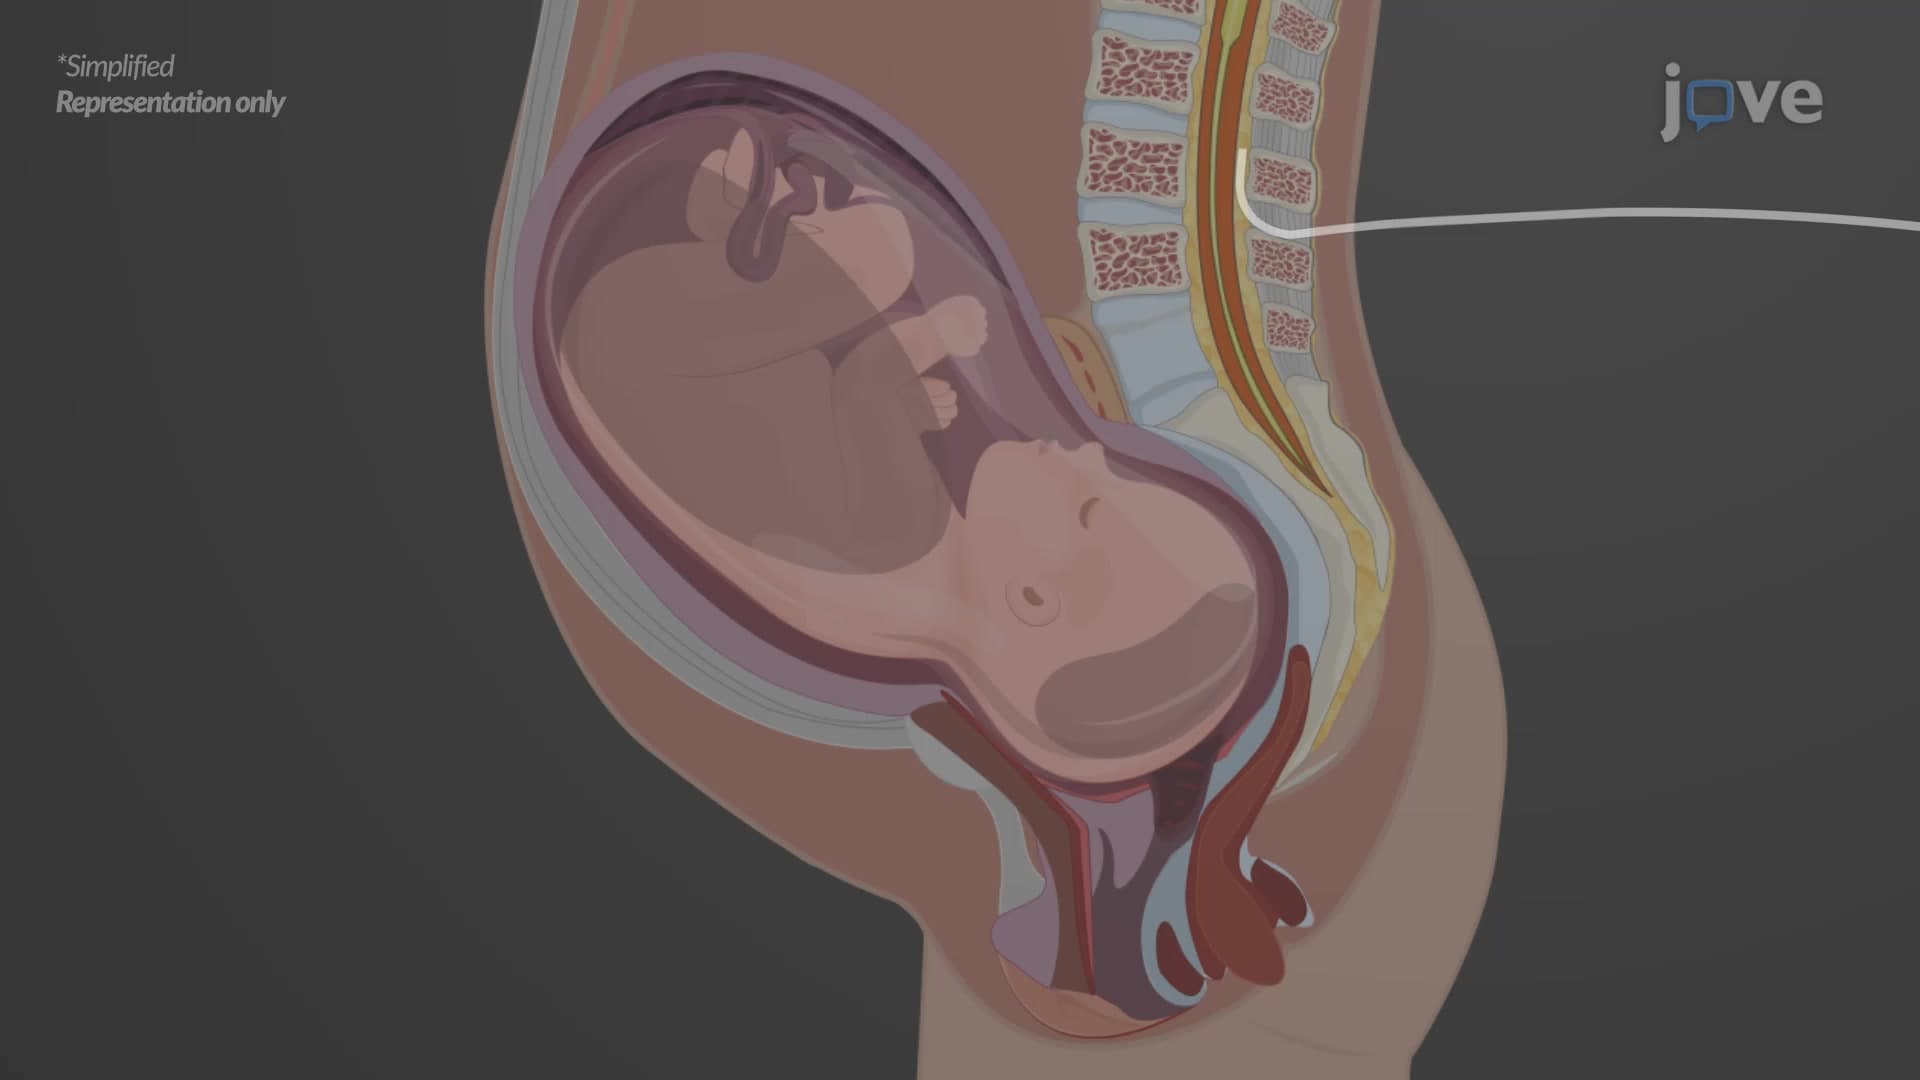
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:24
Parenteral Anesthetics: Overview
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...