Related Experiment Video
Updated: Aug 15, 2026

Cardiac Response to β-Adrenergic Stimulation Determined by Pressure-Volume Loop Analysis
Published on: May 19, 2021
Hyperdynamic myocardial response to beta-adrenergic stimulation in patients with chest pain and normal coronary
Juraj Madaric1, Jozef Bartunek, Katia Verhamme
1Cardiovascular Centre Aalst, OLV Clinic, Aalst, Belgium.

Insights
Abnormal beta-adrenergic stimulation responses may cause chest pain in patients with normal coronary arteries. Dobutamine echocardiography revealed abnormal intraventricular flow velocities in nearly half of patients, which improved with bisoprolol treatment.
Area of Science:
- Cardiology
- Physiology
- Diagnostic Imaging
Background:
- The underlying causes of angina-like chest pain in patients with normal coronary arteries are not fully understood.
- Investigating the role of beta-adrenergic stimulation in this patient group is crucial for diagnosis and treatment.
Purpose of the Study:
- To test the hypothesis that an abnormal response to beta-adrenergic stimulation contributes to chest pain pathophysiology in patients with normal coronary arteries.
- To evaluate regional wall motion and intraventricular flow velocities (IFV) using dobutamine echocardiography (DE).
Main Methods:
- Fifty-eight patients with angina-like chest pain and normal coronary angiograms underwent DE.
- Twenty-two matched healthy individuals served as controls.
- Abnormal IFV was defined as a dagger-shaped Doppler spectrum ≥3 m/s.
Main Results:
- No dobutamine-induced regional wall motion abnormalities were observed.
- Abnormal IFV (≥3 m/s) was detected in 48% of patients with chest pain versus 18% of controls (p < 0.05).
- Patients with abnormal IFV had higher plasma renin concentration (PRC).
- Treatment with bisoprolol reduced IFV and angina scores in a subgroup of patients.
Conclusions:
- An exaggerated myocardial response to beta-adrenergic stimulation is implicated in the mechanisms of chest pain in some patients with normal coronary arteries.
- Dobutamine echocardiography and assessment of IFV can identify patients with abnormal beta-adrenergic responses.
- These findings suggest a potential therapeutic target for managing chest pain in this population.
Objectives:
The goal of this study was to test the hypothesis that an abnormal response to beta-adrenergic stimulation may play a role in the pathophysiology of chest pain in patients with normal coronary arteries.
Background:
The mechanism of angina-like (AL) chest pain in patients with angiographically normal coronary arteries remains controversial.
Methods:
Fifty-eight patients with AL pain and a normal coronary angiogram underwent dobutamine echocardiography (DE) to evaluate regional wall motion and intraventricular flow velocities (IFV). Control patients consisted of 22 matched patients free of angina and coronary artery disease. Abnormal IFV were defined as dagger-shaped Doppler spectrum > or =3 m/s.
Results:
Dobutamine-induced regional wall motion abnormalities did not develop in any of the patients. An IFV > or = 3 m/s was found in 28 patients (48%) with AL pain but in only 4 (18%) control patients (p < 0.05). In the subgroup of patients with AL pain and IFV > or =3 m/s, plasma renin concentration (PRC) was higher as compared with those with IFV <3 m/s (18 +/- 17 pg/ml vs. 9 +/- 6 pg/ml, p < 0.05). There were no differences in plasma ADR, NADR, or angiotensin-converting enzyme levels. Fourteen patients with angina and IFV > or =3 underwent control DE and blood sampling after 6 weeks treatment with 10 mg of bisoprolol. In these patients, a decrease in IFV (from 3.4 +/- 0.35 m/s to 2.46 +/- 0.64 m/s, p < 0.001) and a decrease in angina score (from 5.4 +/- 1.5 to 0.6 +/- 1.4, p < 0.001) were observed at follow-up.
Conclusions:
The present data suggest that an exaggerated myocardial response to beta-adrenergic stimulation plays a role in the mechanisms of chest pain in some patients with normal coronary arteries.


Related Concept Videos
 01:29
Heart Failure II: Pathophysiology
 01:29
Pathophysiology of Cardiac Performance
 01:22
Heart Failure Drugs: β-Blockers
 01:26
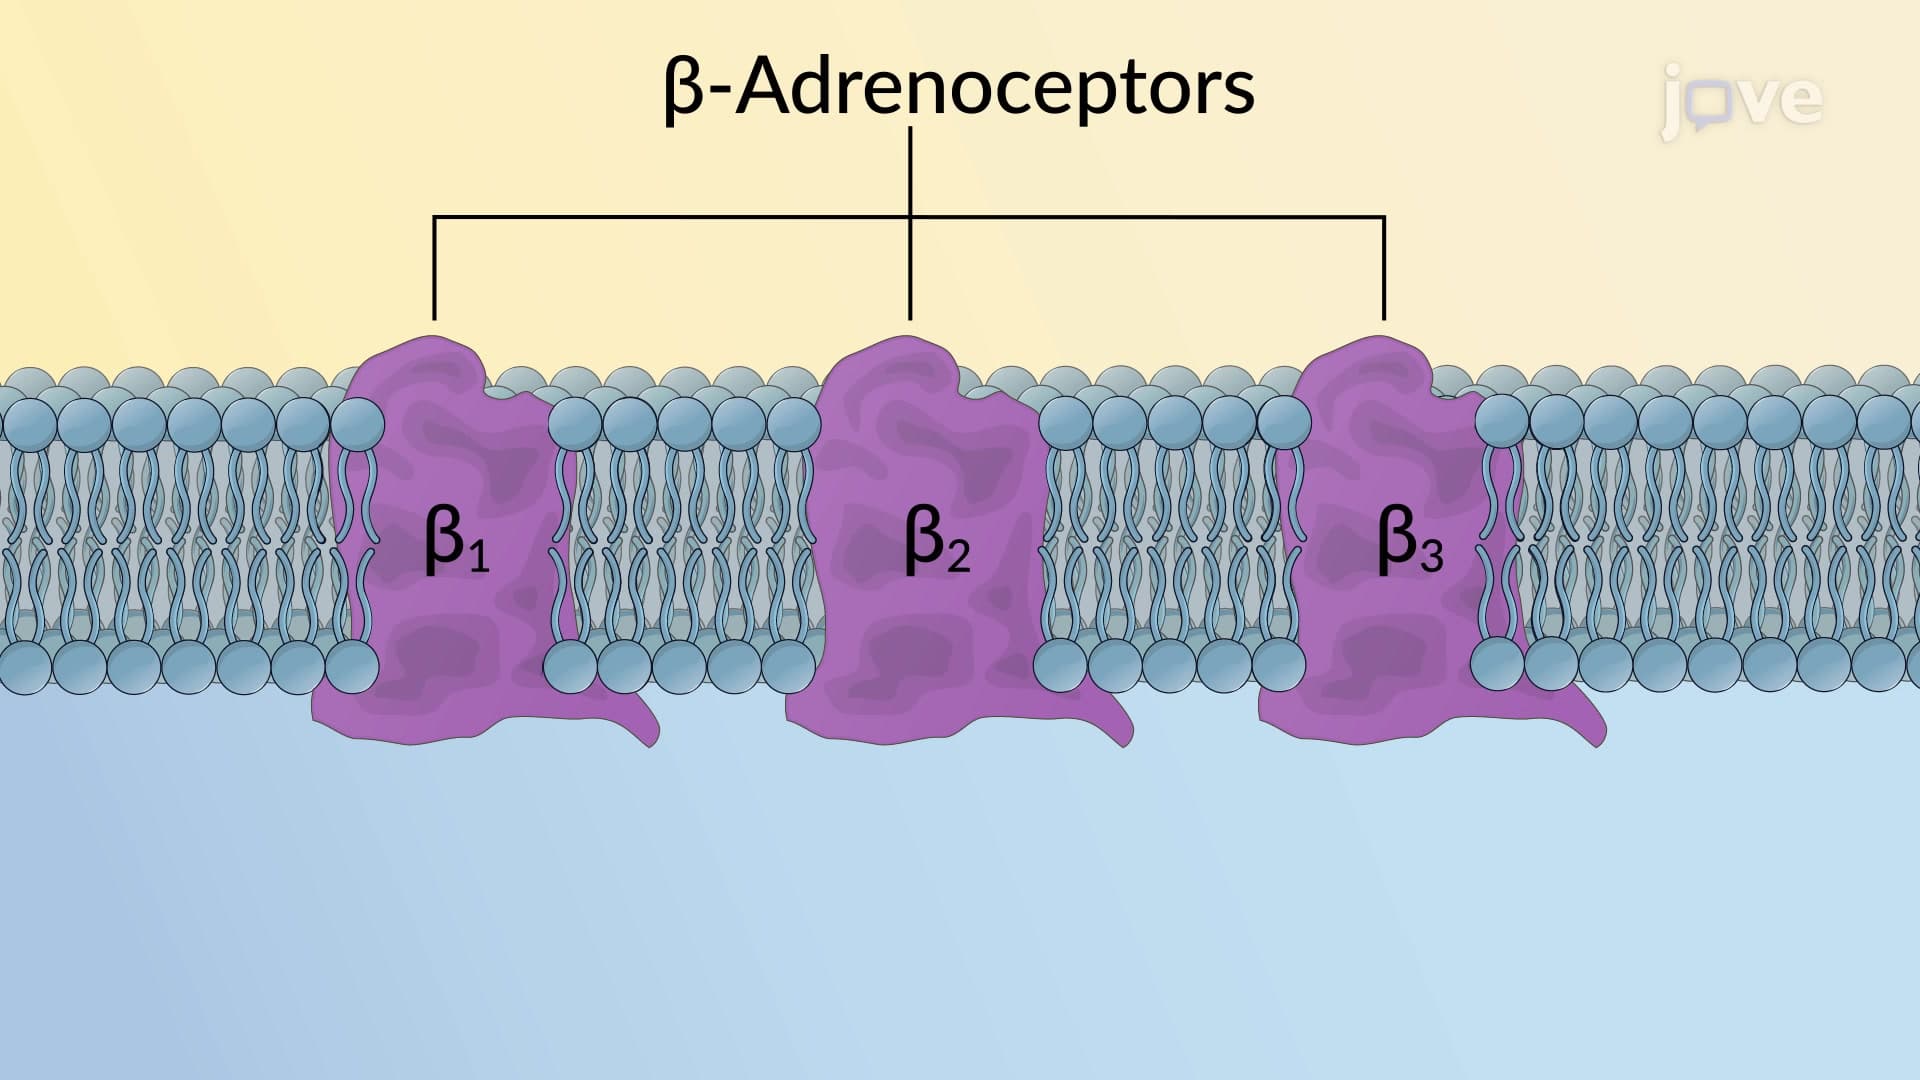
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:16
Antianginal Drugs: Nitrates and β-Blockers
Organic nitrates, such as nitroglycerin, play a pivotal role. Once metabolized, they liberate nitric oxide, a molecular marvel. Nitric oxide triggers guanylyl cyclase and augments cGMP production. This biochemical cascade orchestrates the relaxation of vascular smooth muscles, ushering in vasodilation and enhancing coronary blood flow. Administered...
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy