Related Experiment Video
Updated: Aug 15, 2026

Laparoscopic Repair of Para-Esophageal Hernia Using Absorbable Biosynthetic Mesh
Published on: September 11, 2021
Dysphagia after laparoscopic antireflux surgery: a problem of hiatal closure more than a problem of the wrap
F A Granderath1, U M Schweiger, T Kamolz
1Department of General, Visceral and Transplant Surgery, University Hospital of Tuebingen, 72076 Tuebingen, Germany.

Background:
Postoperative dysphagia after laparoscopic antireflux surgery usually is transient and resolves within weeks after surgery. Persistent dysphagia develops in a small percentage of patients after surgery. There still is debate about whether postoperative dysphagia is caused by the type or placement of the fundic wrap or by mechanical obstruction of the hiatal crura. This study aimed to investigate patients who experienced recurrent or persistent dysphagia after laparoscopic antireflux surgery, and to identify the morphologic reason for this complication.
Methods:
A sample of 50 patients consecutively referred to the authors' unit with recurrent, persistent, or new-onset of dysphagia after laparoscopic antireflux surgery were prospectively reviewed to identify the morphologic cause of postoperative dysphagia. According to their radiologic findings, these patients were divided into three groups: patients with signs of obstruction at or above the gastroesophageal junction suspicious of crural stenosis (group A; n = 18), patients with signs of total or partial migration of the wrap intrathoracically (group B; n = 27), and patients in whom the hiatal closure was radiologically assessed to be correct with a supposed stenosis of the wrap (group C; n = 5). The exact diagnosis of a too tight (group A) or too loose (group B) hiatus in contrast to a too tight wrap (group C) was established during laparoscopic redo surgery (groups B and C) or by x-ray during pneumatic dilation (group A).
Results:
For all 18 group A patients, intraoperative x-ray during pneumatic dilation showed the typical signs of hiatal tightness. Of these, 15 were free of symptoms after dilation, and 3 had to undergo laparoscopic redo surgery because of persistent dysphagia. In all these patients, the hiatal closure was narrowing the esophagus. All the group B patients underwent laparoscopic redo surgery because of intrathoracic wrap migration. Intraoperatively, all the patients had an intact fundoplication, which slipped above the diaphragm. Definitely, only in 10% of all 50 patients (group C) presenting with the symptom of dysphagia, was the morphologic reason for the obstruction a problem of the fundic wrap.
Conclusions:
In most patients, postoperative dysphagia is more a problem of hiatal closure than a problem of the fundic wrap.

Related Concept Videos
 01:25
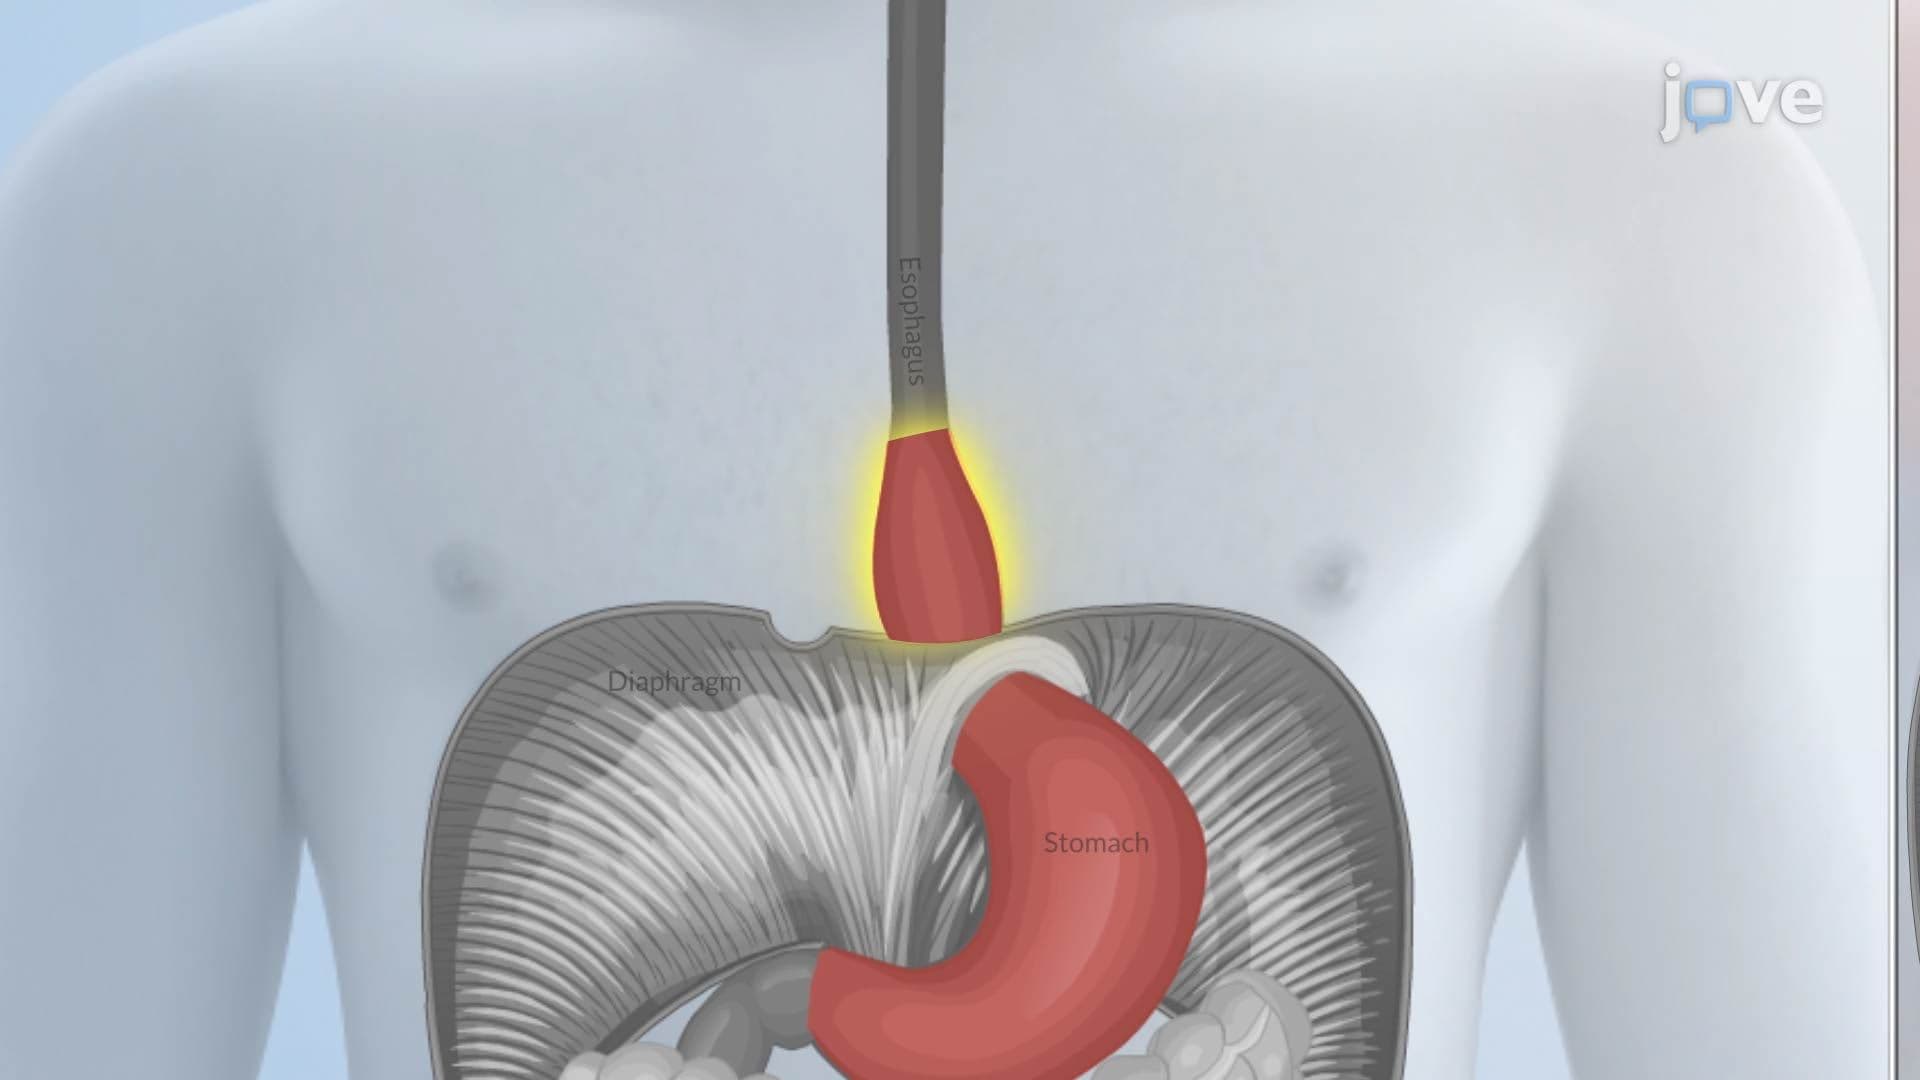
Hiatal Hernia
 01:27
Esophageal Achalasia
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...