Related Experiment Videos
Incremental effects of concurrent pharmacotherapeutic regimens for heart failure on hospitalizations and costs
Grant H Skrepnek1, Jacob Abarca, Daniel C Malone
1College of Pharmacy, University of Arizona, Tucson, AZ 85721-0207, USA. skrepnek@pharmacy.arizona.edu

Insights
Patients with heart failure (HF) on suboptimal medication regimens face higher hospitalization risks and costs. Optimal use of guideline-recommended HF medications significantly reduces these risks and associated healthcare expenses.
Area of Science:
- Cardiology
- Pharmacotherapy
- Health Economics
Background:
- Inappropriate medication use in heart failure (HF) patients complicates evidence-based care.
- Suboptimal pharmacotherapy contributes to increased hospitalizations and healthcare costs.
Purpose of the Study:
- To assess the impact of concurrent and persistent use of ACE inhibitors, beta-blockers, loop diuretics, and digoxin on HF patient outcomes.
- To evaluate the one-year risk of all-cause hospitalization and total healthcare costs associated with HF treatment.
Main Methods:
- Retrospective analysis of a US managed care organization database (1997-1999).
- Multivariate regression models examined associations between treatment regimens, hospitalizations, and costs.
- Controlled for patient demographics and risk factors.
Main Results:
- Patients receiving none of the four studied HF agents had a 2.5-fold higher hospitalization risk and 43.6% greater costs.
- Persistent use of three or more HF agents was associated with an 80% reduction in hospitalizations and a 70% decrease in costs.
Conclusions:
- A significant number of HF patients receive suboptimal pharmacotherapy in real-world settings.
- Suboptimal care leads to increased hospitalizations and healthcare expenditures.
- Quality improvement programs are needed to ensure guideline-adherent HF treatment.
Background:
Inappropriate medication use in patients with heart failure (HF) presents challenges in providing optimal, evidence-based care.
Objective:
To evaluate the incremental differences of concurrent and persistent use of angiotensin-converting enzyme (ACE) inhibitors, beta-blockers, loop diuretics, and digoxin on the one-year, all-cause risk of hospitalization and total healthcare costs associated with treatment of HF in patients enrolled in a managed care organization within the US.
Methods:
A retrospective database analysis was conducted spanning from January 1, 1997, to December 31, 1999. Multivariate regression methods were used to examine the association between treatment regimens and hospitalizations or costs after controlling for patient demographics and risk factors.
Results:
Of the 1903 patients meeting inclusion criteria, 32.3% (n = 615) received none of the 4 HF agents studied and were associated with a 2.5 times greater risk (p < or = 0.001) of hospitalization and 43.6% higher (p < or = 0.001) total costs compared with all other patients with HF. Comparatively, 13.9% (n = 264) utilized the HF medications investigated for at least 6 months. Of those with persistent use of > or =3 agents, approximate decreases in hospitalizations were noted of 80% (p < or = 0.001) and total costs of 70% (p < or = 0.001) relative to patients receiving no HF therapy.
Conclusions:
A substantial portion of patients with HF may be receiving suboptimal pharmacotherapeutic care in real-world practice settings, potentially incurring large increases in hospitalizations and total costs. Quality improvement initiatives should seek to identify and manage those not being treated according to guideline recommendations.
Related Concept Videos
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:30
Heart Failure V: Medical Management
 01:22
Heart Failure VI: Adjunct Therapies
 01:24
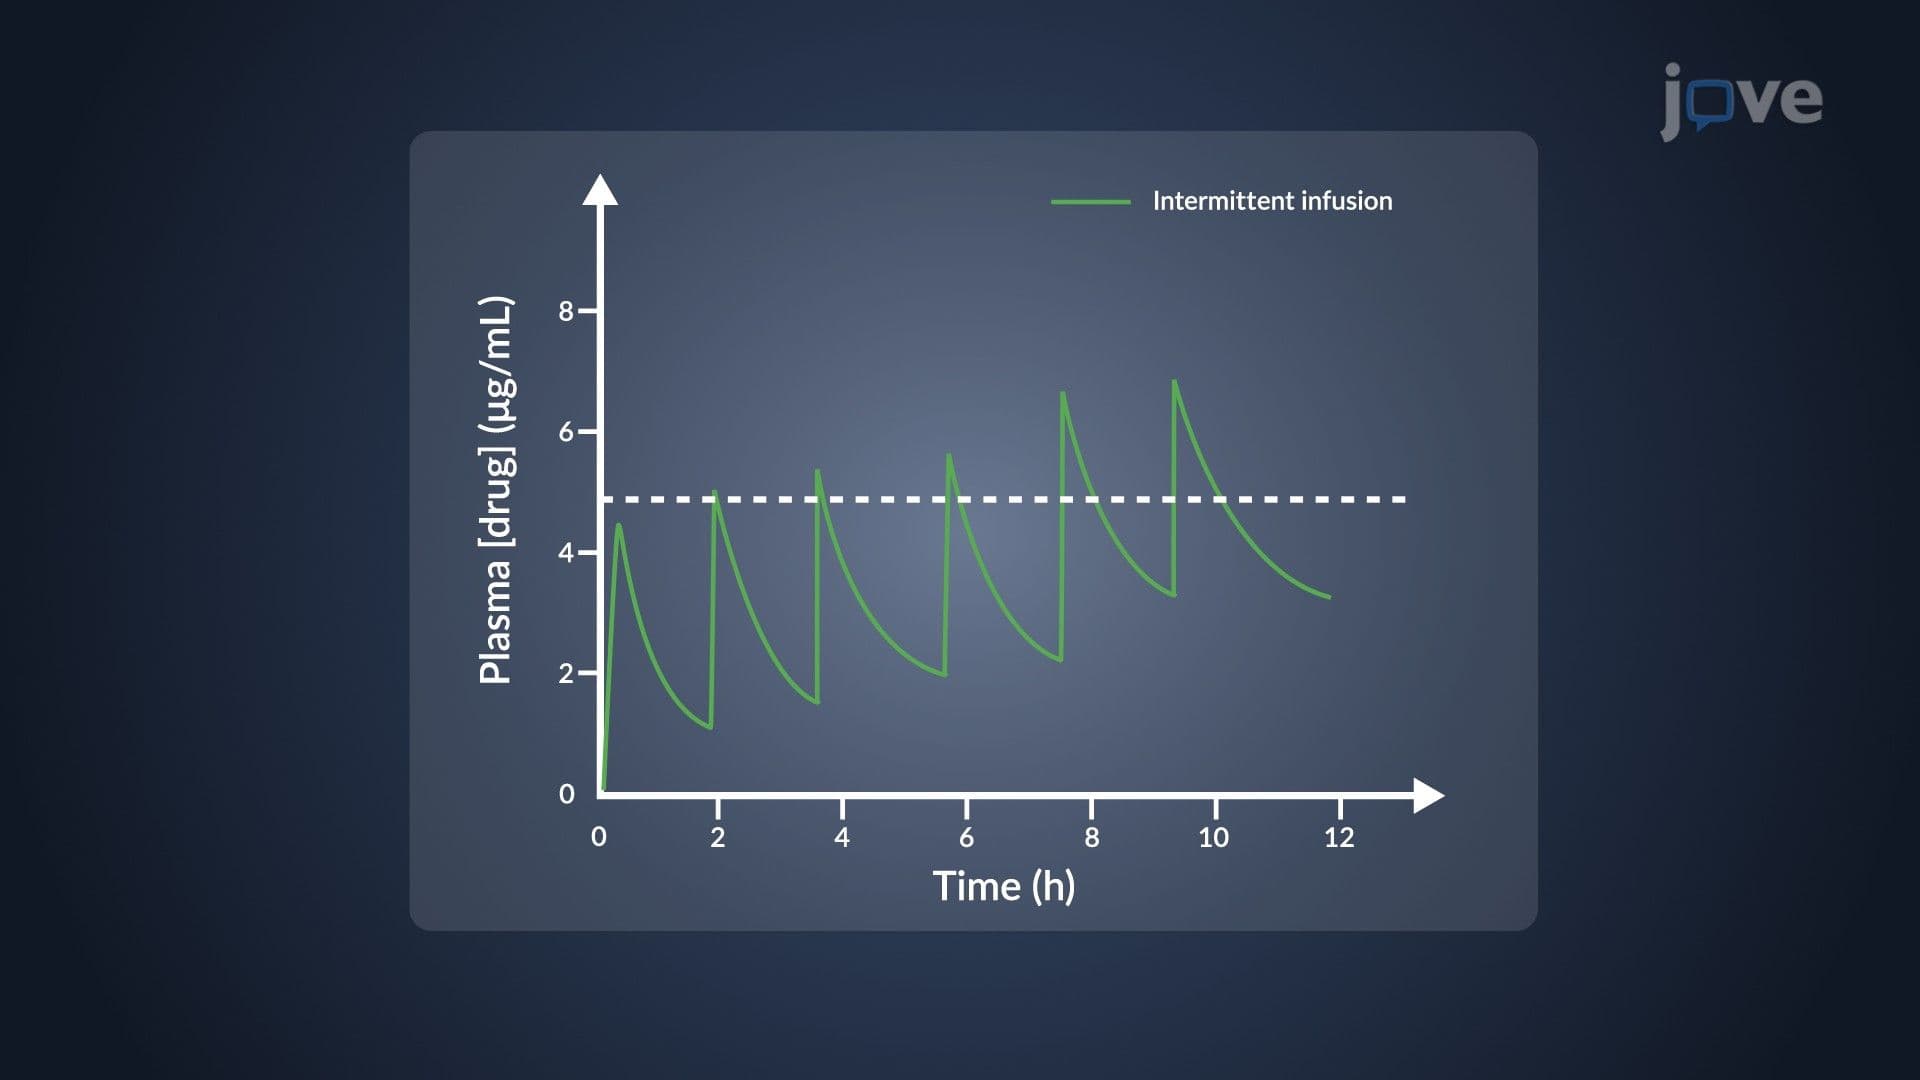
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:26
Heart Failure Drugs: Inotropic Agents
 01:22
Heart Failure Drugs: Diuretics