Related Experiment Video
Updated: Aug 15, 2026
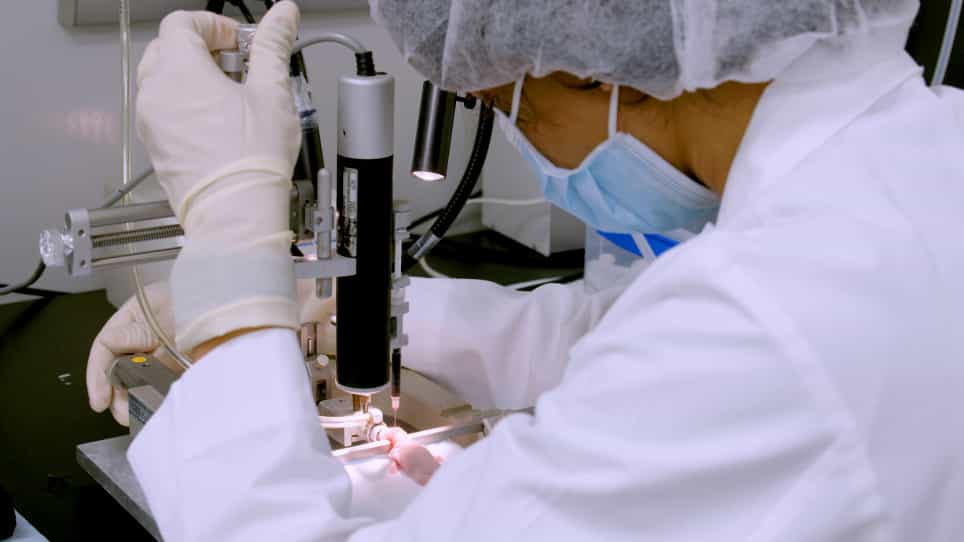

Modeling Neonatal Intraventricular Hemorrhage Through Intraventricular Injection of Hemoglobin
Published on: August 25, 2022
A follow-up study of infants with intracranial hemorrhage at full-term
Balraj S Jhawar1, Adrianna Ranger, David A Steven
1Division of Neurosurgery, London Health Sciences Centre, University of Western Ontario, London, Ontario, Canada.

Insights
Infants experiencing birth intracranial hemorrhage (ICH) showed varied outcomes. Thrombocytopenia significantly increased the risk of physical disability, while frontal lobe bleeds were most disabling.
Area of Science:
- Neonatal neurology
- Pediatric neurosurgery
- Perinatal medicine
Background:
- Intracranial hemorrhage (ICH) is a serious birth complication affecting newborns.
- Understanding the long-term physical and cognitive impacts of ICH is crucial for infant care.
Purpose of the Study:
- To evaluate the physical and cognitive outcomes in full-term infants following birth-related intracranial hemorrhage (ICH).
- To identify perinatal risk factors and hemorrhage characteristics associated with adverse outcomes.
Main Methods:
- Retrospective hospital-based follow-up study of infants treated between 1985-1996.
- Outcome assessment via telephone interviews and clinic visits using physical and cognitive scales.
- Correlation analysis between perinatal factors, hemorrhage details, and infant outcomes.
Main Results:
- 57% of infants with ICH had no physical or cognitive deficits at follow-up (median 3 years).
- Subdural hemorrhage was associated with better outcomes (80% no disability), while subarachnoid hemorrhage had higher mortality (19%).
- Thrombocytopenia was a significant predictor of physical disability (OR=7.6) and borderline for cognitive disability (OR=4.6). Frontal lobe bleeds and spontaneous vaginal delivery were also linked to poorer outcomes.
Conclusions:
- While forceps-assisted delivery may contribute to ICH, outcomes were better than spontaneous vaginal delivery in this cohort.
- Frontal lobe hemorrhage and multifocal involvement increased disability risk.
- Thrombocytopenia emerged as the most significant factor associated with poor physical and cognitive outcomes in infants with ICH.
Objective:
To determine physical and cognitive outcomes of full-term infants who suffered intracranial hemorrhage (ICH) at birth.
Methods:
A retrospective hospital-based, follow-up study of infants treated in London, Ontario between 1985 and 1996. Follow-up was conducted by telephone interviews and clinic visits. Outcome was measured according to physical and cognitive scales. Perinatal risk factors and hemorrhage characteristics were correlated with final outcome.
Results:
For this study 66 infants with ICH were identified, of which seven died during the first week of life. We obtained follow-up in all but ten cases (median = 3-years; range 1.0 to 10.9 years). Overall, 57% of infants had no physical or cognitive deficits at follow-up. Death occurred most frequently among those with primarily subarachnoid hemorrhage (19%) and the most favorable outcomes occurred among those with subdural hemorrhage (80% had no disability). In univariate models, thrombocytopenia (platelet count < or = 70 x 10(9)/L), increasing overall hemorrhage severity, frontal location and spontaneous vaginal delivery as opposed to forceps-assisted delivery increased risk for poor outcome. In multivariate models, all these factors tended towards increased risk, but only thrombocytopenia remained significant for physical disability (OR = 7.6; 95% CI = 1.02 - 56.6); thrombocytopenia was borderline significant in similar models for cognitive disability (OR = 4.6; 95% CI = 0.9 - 23.9).
Conclusion:
Although forceps-assisted delivery may contribute to ICH occurrence, our study found better outcomes among these infants than those who had ICH following a spontaneous vaginal delivery. Hemorrhage in the frontal lobe was the most disabling hemorrhage location and if multiple compartments were involved, disability was also more likely to occur. However, in this report we found that the factor that was most likely to contribute to poor outcome was thrombocytopenia and this remained important in multivariate analysis.
