Related Experiment Video
Updated: Aug 15, 2026

A High-throughput Method for Measurement of Glomerular Filtration Rate in Conscious Mice
Published on: May 10, 2013
Agreement between two routine methods of estimation of glomerular filtration rate in patients with advanced and
R Garcia-Naveiro1, A Rodriguez-Carmona, M Pérez-Fontán
1Division of Nephrology, Hospital Juan Canalejo, A Corunia, Spain.

Background:
Estimations of glomerular filtration rate (GFR) obtained either by the modification of diet in renal disease study equation (MDRD-GFR) or by classic 24-hour urine collection-based methods (mean of creatinine and urea clearance (Ccr-ur)) are considered to be equivalent in patients with chronic renal failure (CRF). However, the agreement between both methods has been insufficiently studied in patients during the most advanced stages of CRF.
Methods:
We compared 615 estimations of GFR performed by both methods simultaneously in adult (> 18 years) patients with advanced (aCRF) (15 - 30 ml/min/1.73m2) and preterminal (tCRF) (< 15 ml/min/1.73m2) chronic renal failure. We also analyzed the influence of some relevant covariables (demographic characteristics, inflammatory and nutritional markers) with respect to the concordance between both methods.
Results:
In aCRF, mean GFR were 19.7 +/- 5.5 (MDRD-GFR) and 19.3 +/- 3.7 ml/min/1.73m2 (Ccr-ur) (mean difference 0.4 ml/min/1.73m2, 95% confidence interval CI -0.3/1.1, p = 0.26), with an intraclass correlation coefficient of 0.46. In tCRF, mean GFR was 12.5 +/- 4.2 and 10.4 +/- 2.7 ml/min/1.73m2, respectively (mean difference 2.1 ml/min/1.73m2, 95% CI 1.7/2.4, p < 0.0005), with an intraclass correlation co-efficient of 0.43. Multivariate analysis identified lean body mass, body mass index, protein nitrogen appearance, proteinuria, gender, age, albumin (aCRF) and prealbumin (tCRF) as variables independently correlated with the difference MDRD-GFR minus Ccr-ur. Lean body mass was by far the strongest predictor of deviations between both methods, both in aCRF (R2 = 0.66, p < 0.0005) and tCRF (R2 = 0.49, p < 0.0005).
Conclusions:
MDRD-GFR and Ccr-ur show an acceptable agreement in advanced stages of chronic renal failure. However, MDRD-GFR produces estimations of GFR systematically higher than those given by the Ccr-ur method, in patients with tCRF. Moreover, this overestimation is particularly marked in some high risk subsets, including elderly patients and those presenting markers of a poor nutritional condition. Until this issue is further clarified, GFR should be estimated using Ccr-ur rather than MDRD-GFR in patients with tCRF, as also in older and malnourished patients with aCRF, as this may represent a more conservative and safer approach at the time of planning initiation of renal replacement therapy.

Related Concept Videos
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:25
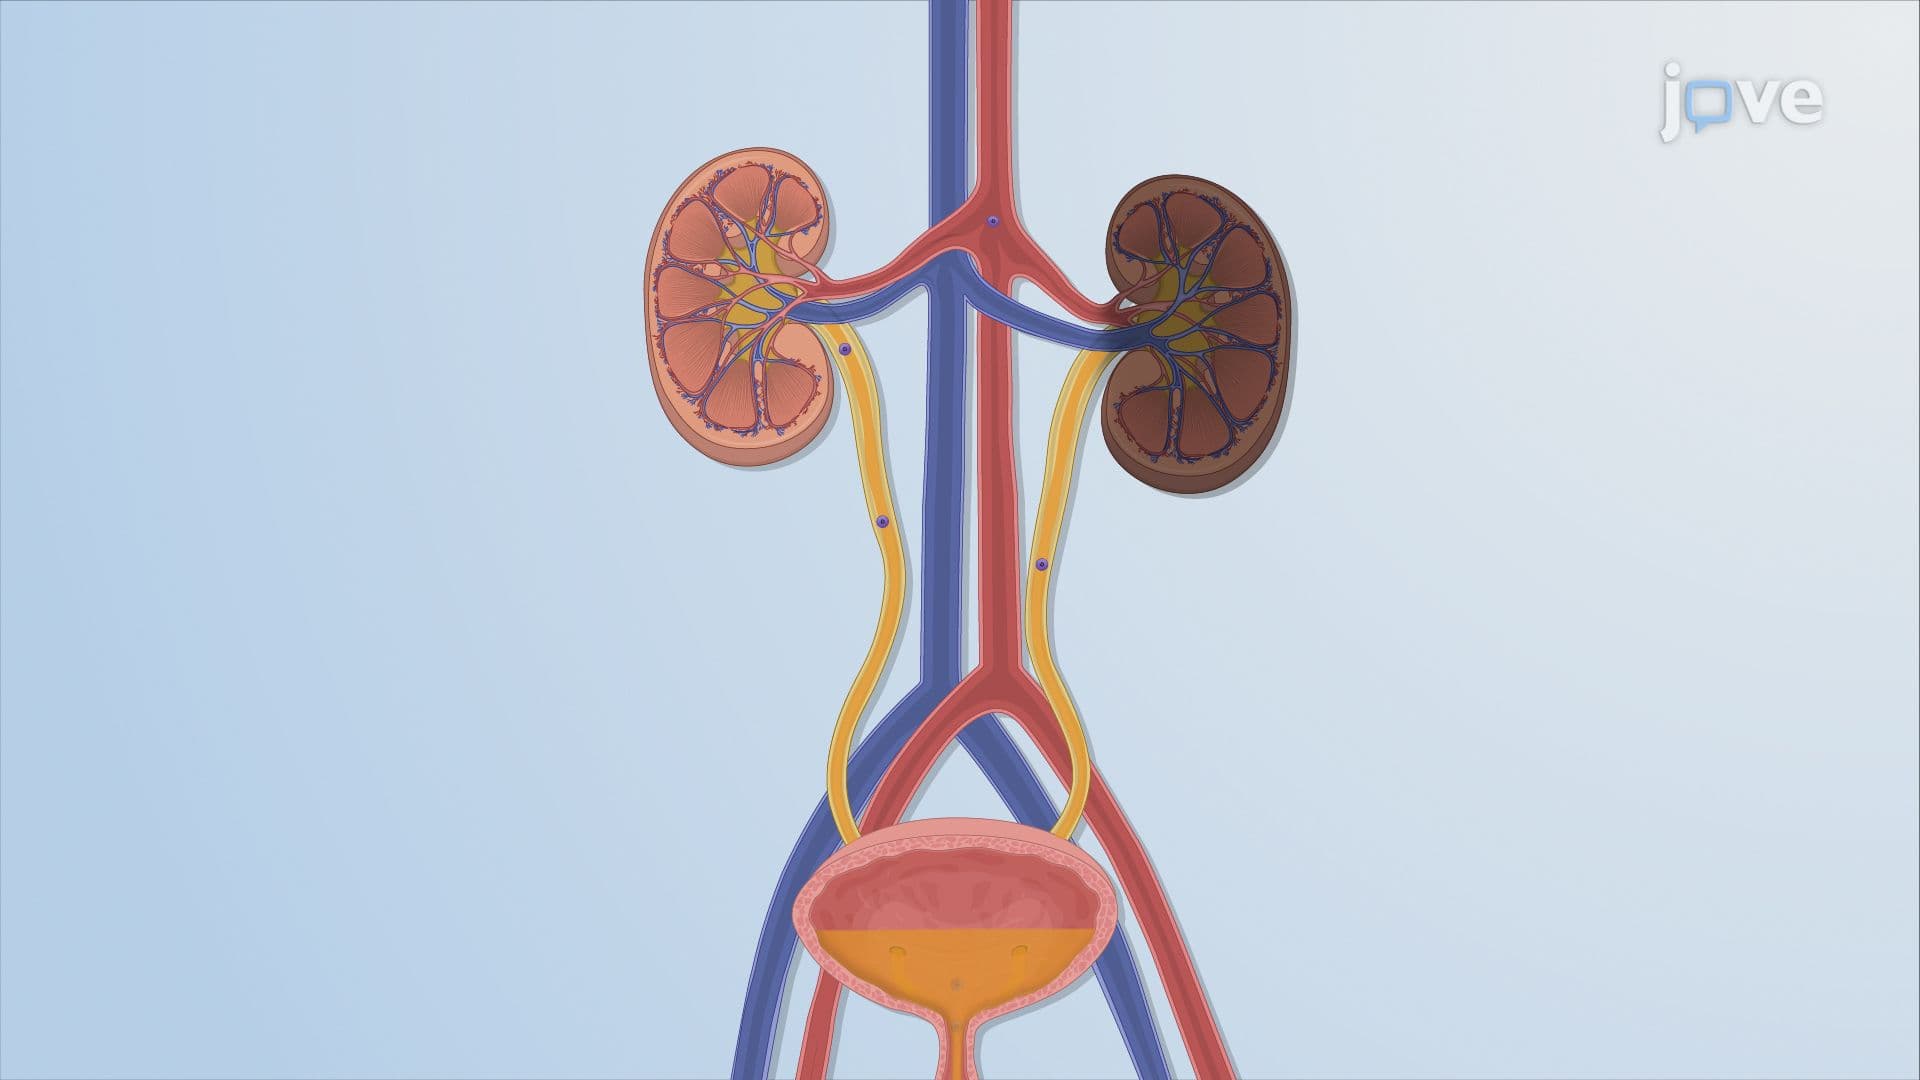
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate
 01:25
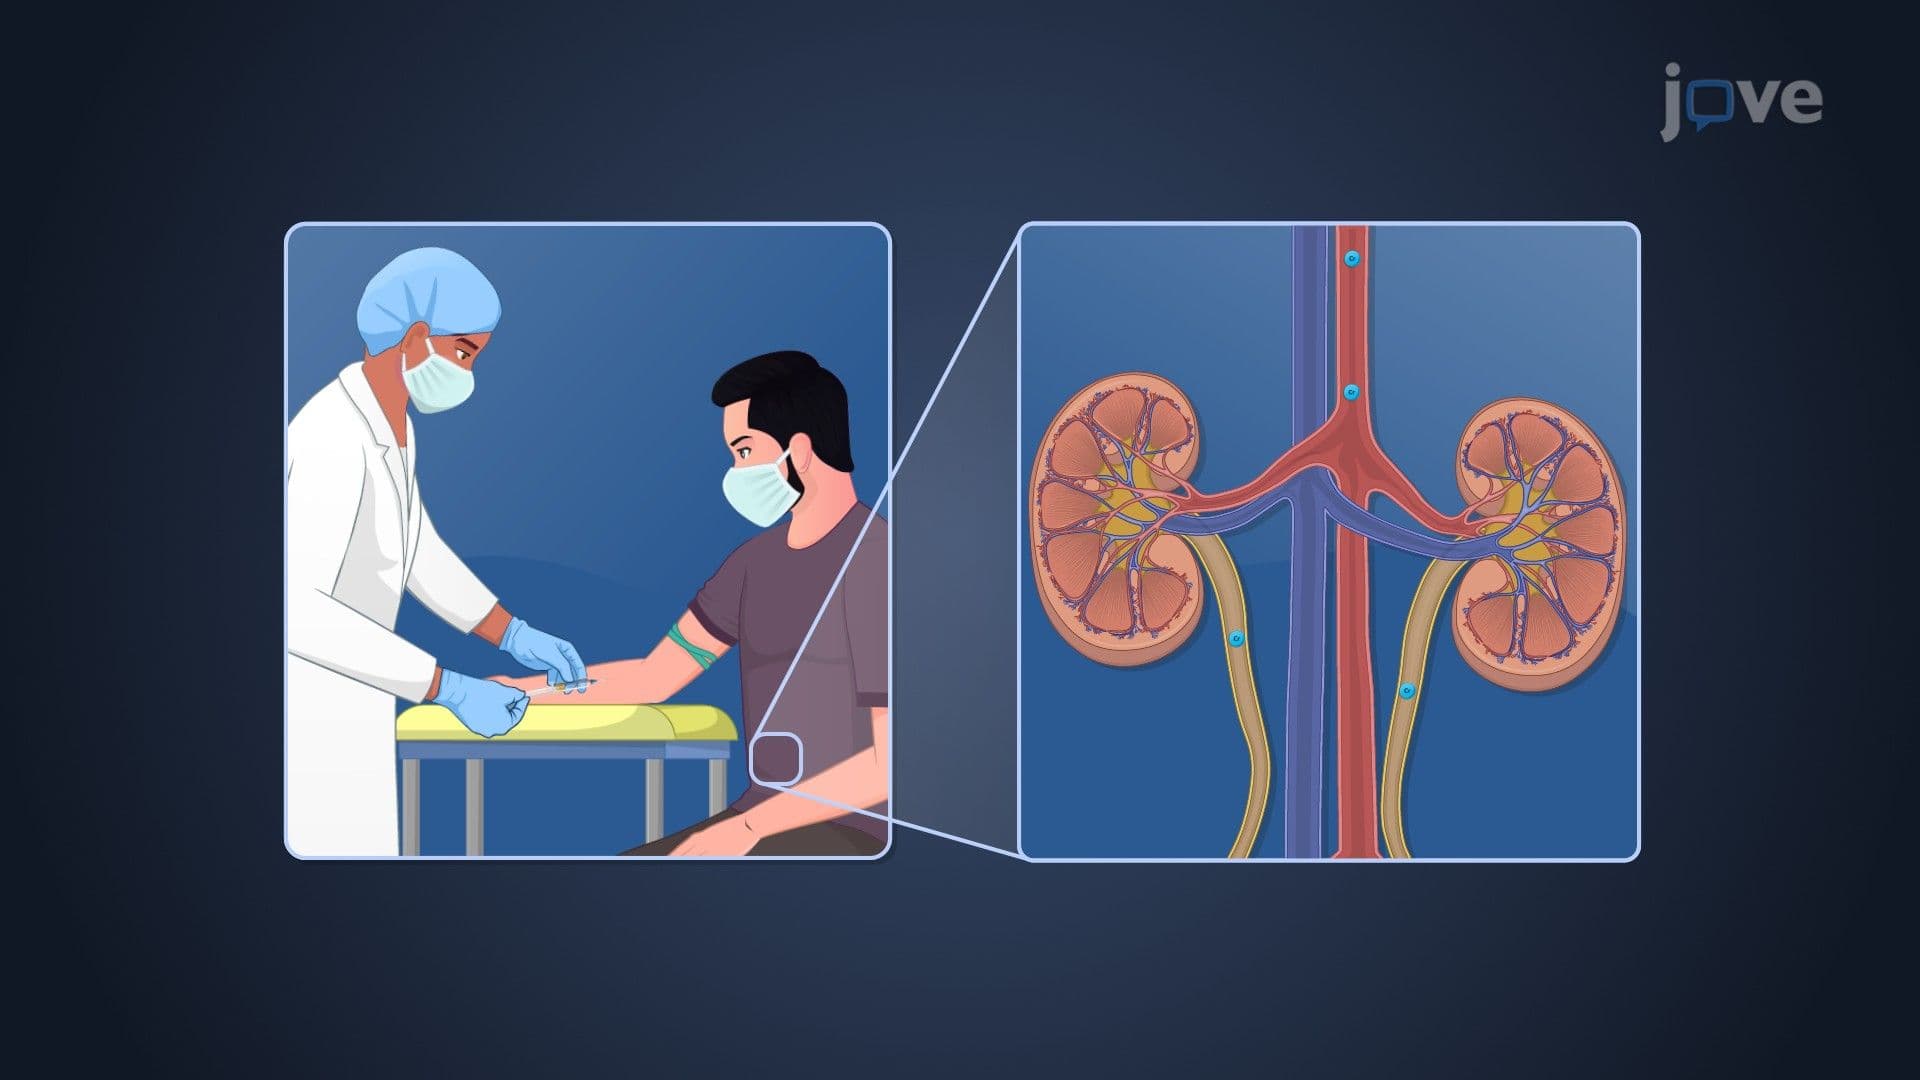
Drug Dosing in Renal Diseases: Measurement of Serum Creatinine Concentration and Clearance
 01:02
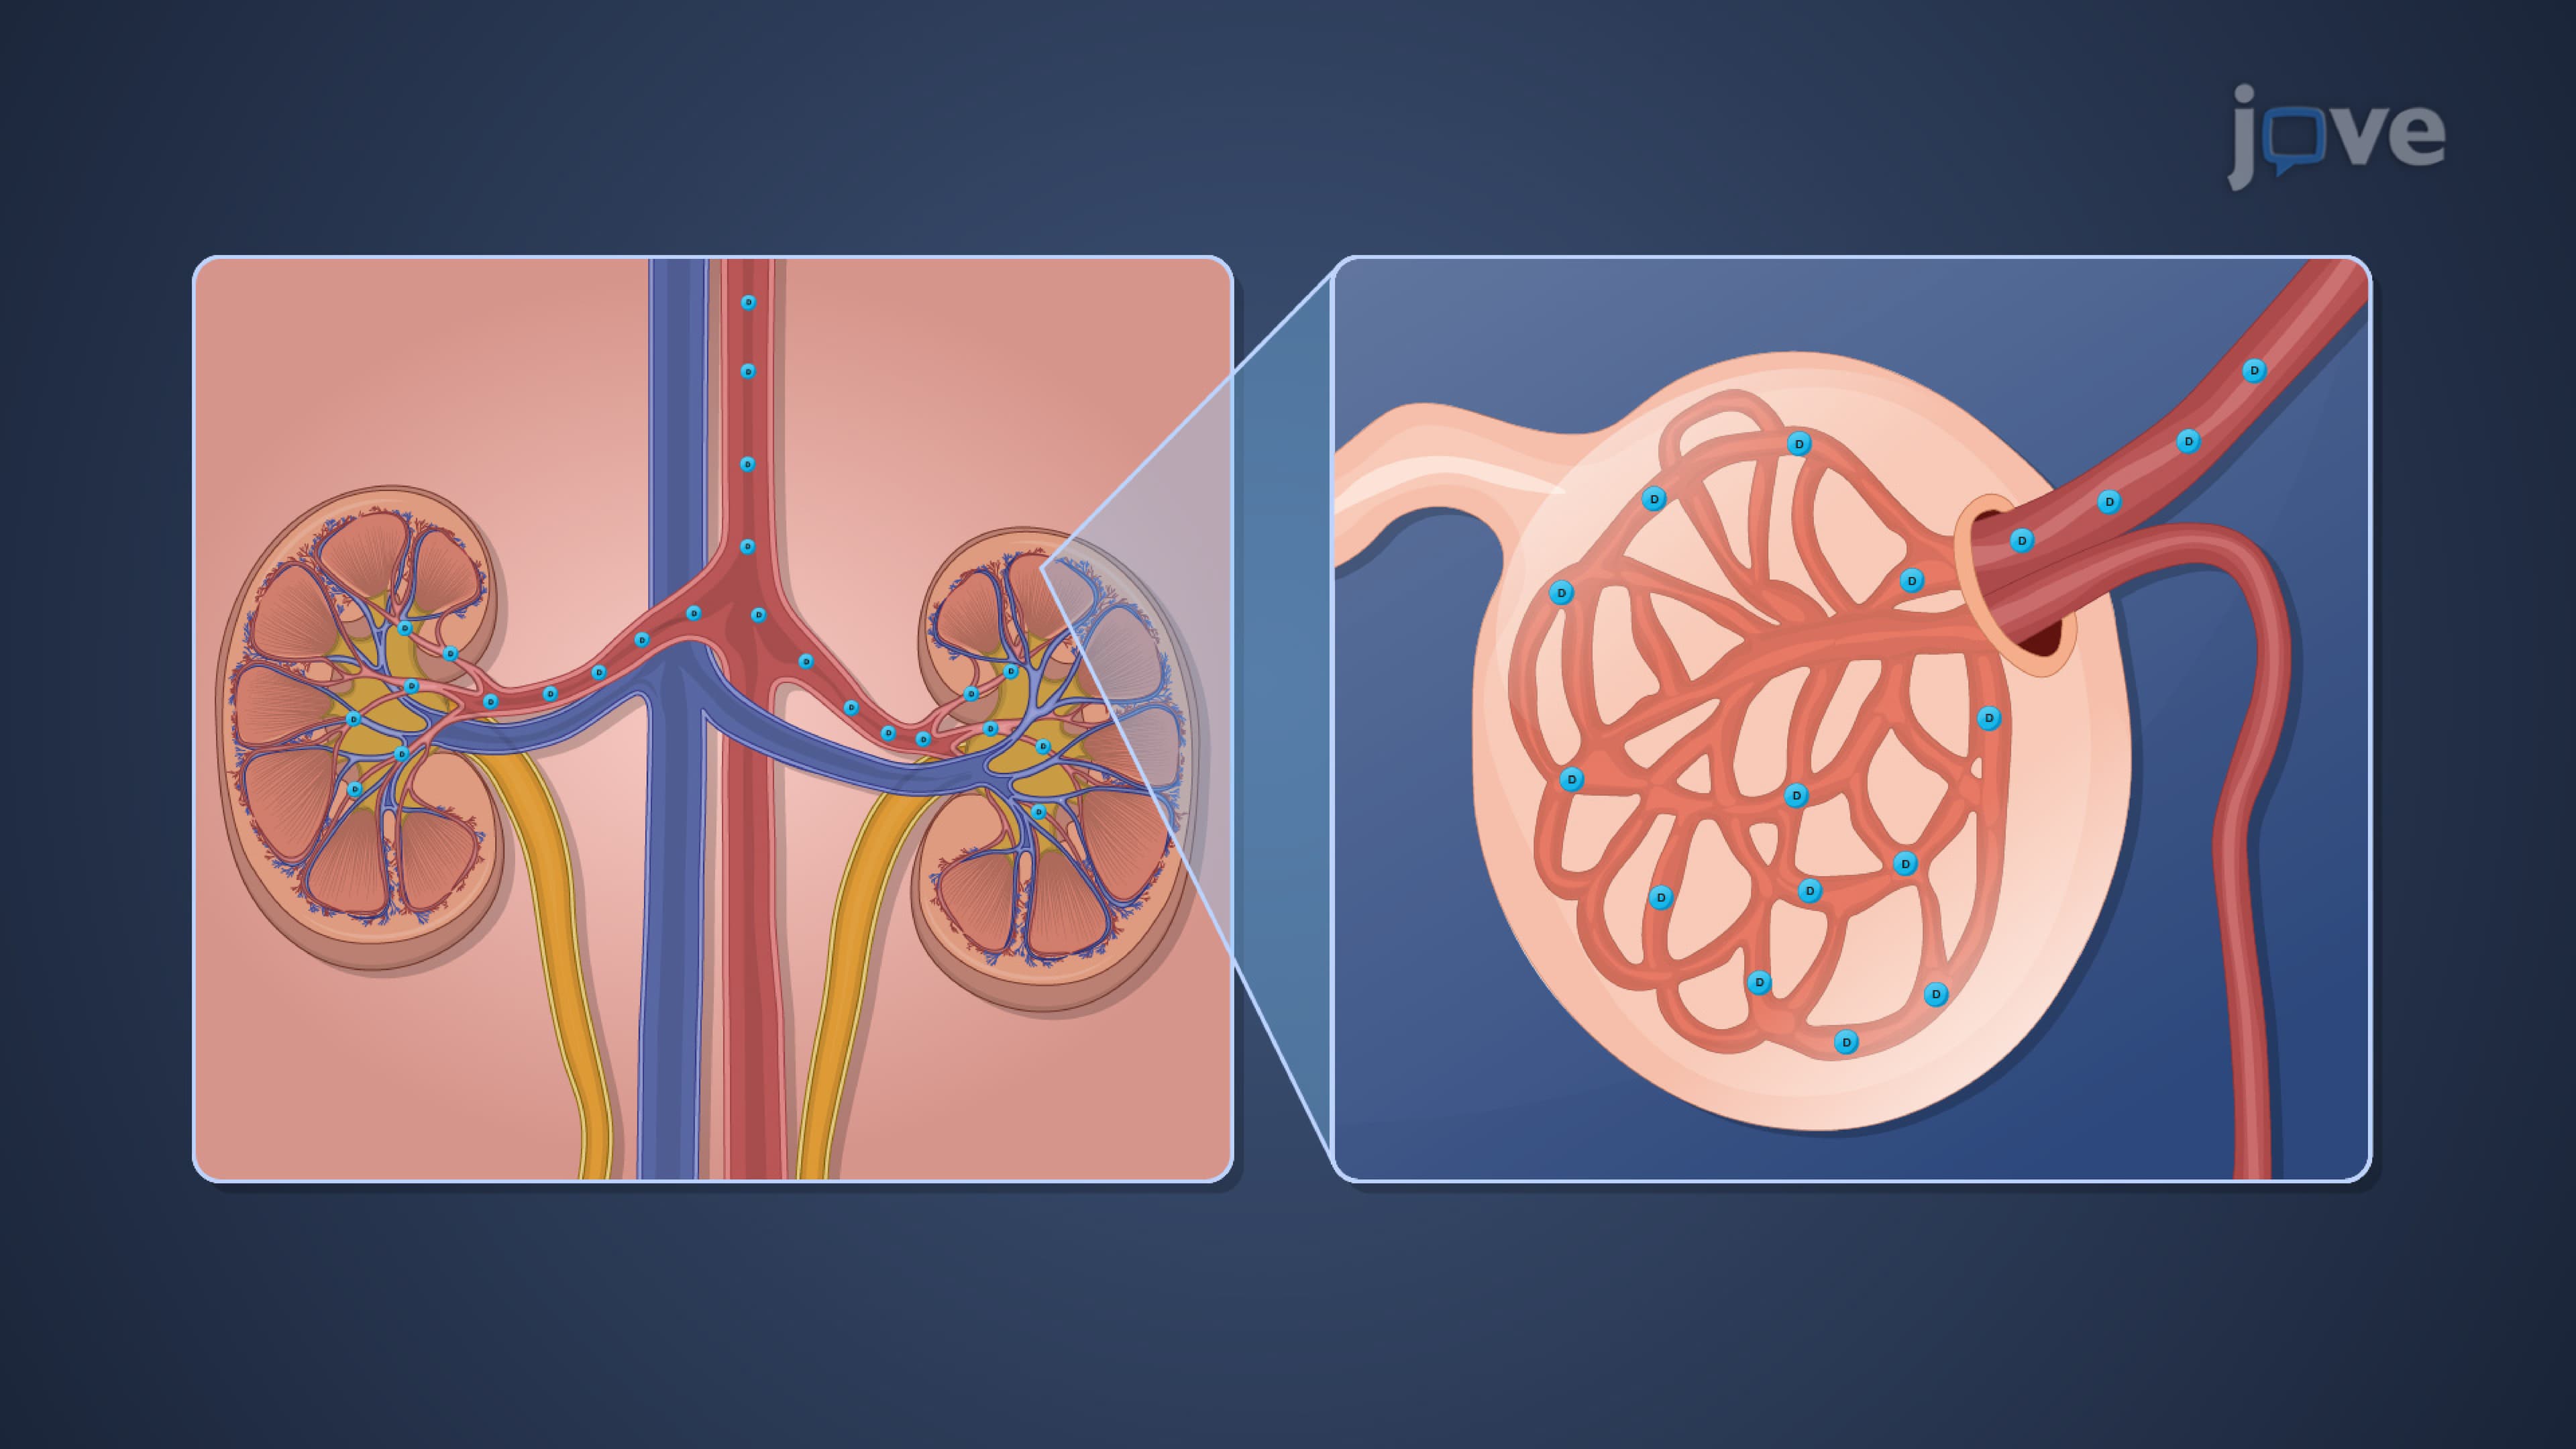
Renal Drug Excretion: Glomerular Filtration
Drugs gain access to the kidney via the renal artery, which progressively branches off into afferent arterioles.
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant