Related Experiment Video
Updated: Aug 15, 2026


5/6 Nephrectomy Using Sharp Bipolectomy Via Midline Laparotomy in Rats
Published on: April 4, 2025
Life-threatening hypokalaemia on a low-carbohydrate diet associated with previously undiagnosed primary
1Department of Diabetes and Metabolism, Medical School, William Leech Building, 1 Framlington Place, Newcastle upon Tyne NE2 4HH, UK. Andrew.Advani@ncl.ac.uk

Background:
Low-carbohydrate diets are popular and fashionable for weight loss despite lack of evidence about long-term effects. Many individuals attempting to lose weight have hypertension, especially those with diabetes, and the prevalence of hyperaldosteronism among hypertensive patients is higher than previously recognized. We present a patient with Type 2 diabetes and previously undiagnosed hyperaldosteronism who developed life-threatening hypokalaemia while following a low-carbohydrate diet.
Case Report:
A 60-year-old man with diet-treated Type 2 diabetes and hypertension presented with generalized muscle weakness and serum potassium of 1.9 mmol/l. He had succeeded in losing three and a half stones during the previous 4 months by adhering strictly to a low-carbohydrate diet. HbA(1c) was 4.8% and plasma aldosterone:renin ratios were elevated suggestive of increased aldosterone secretion. On a low-calorie mixed diet serum potassium levels were maintained in the low-normal range over the following 165 days. The adrenals were normal on CT scanning and blood pressure responded dramatically to the addition of spironolactone on day 212 (125/83 mmHg).
Conclusions:
The prevalence of primary hyperaldosteronism in the hypertensive population, based on elevation of plasma renin:aldosterone ratio, is approximately 6%. The majority of these people are normokalaemic and remain undiagnosed. However, when carbohydrate intake is restricted such individuals are at increased risk of potentially life-threatening metabolic derangements.
Related Concept Videos
 01:28
Antihypertensive Drugs: Potassium-Sparing Diuretics
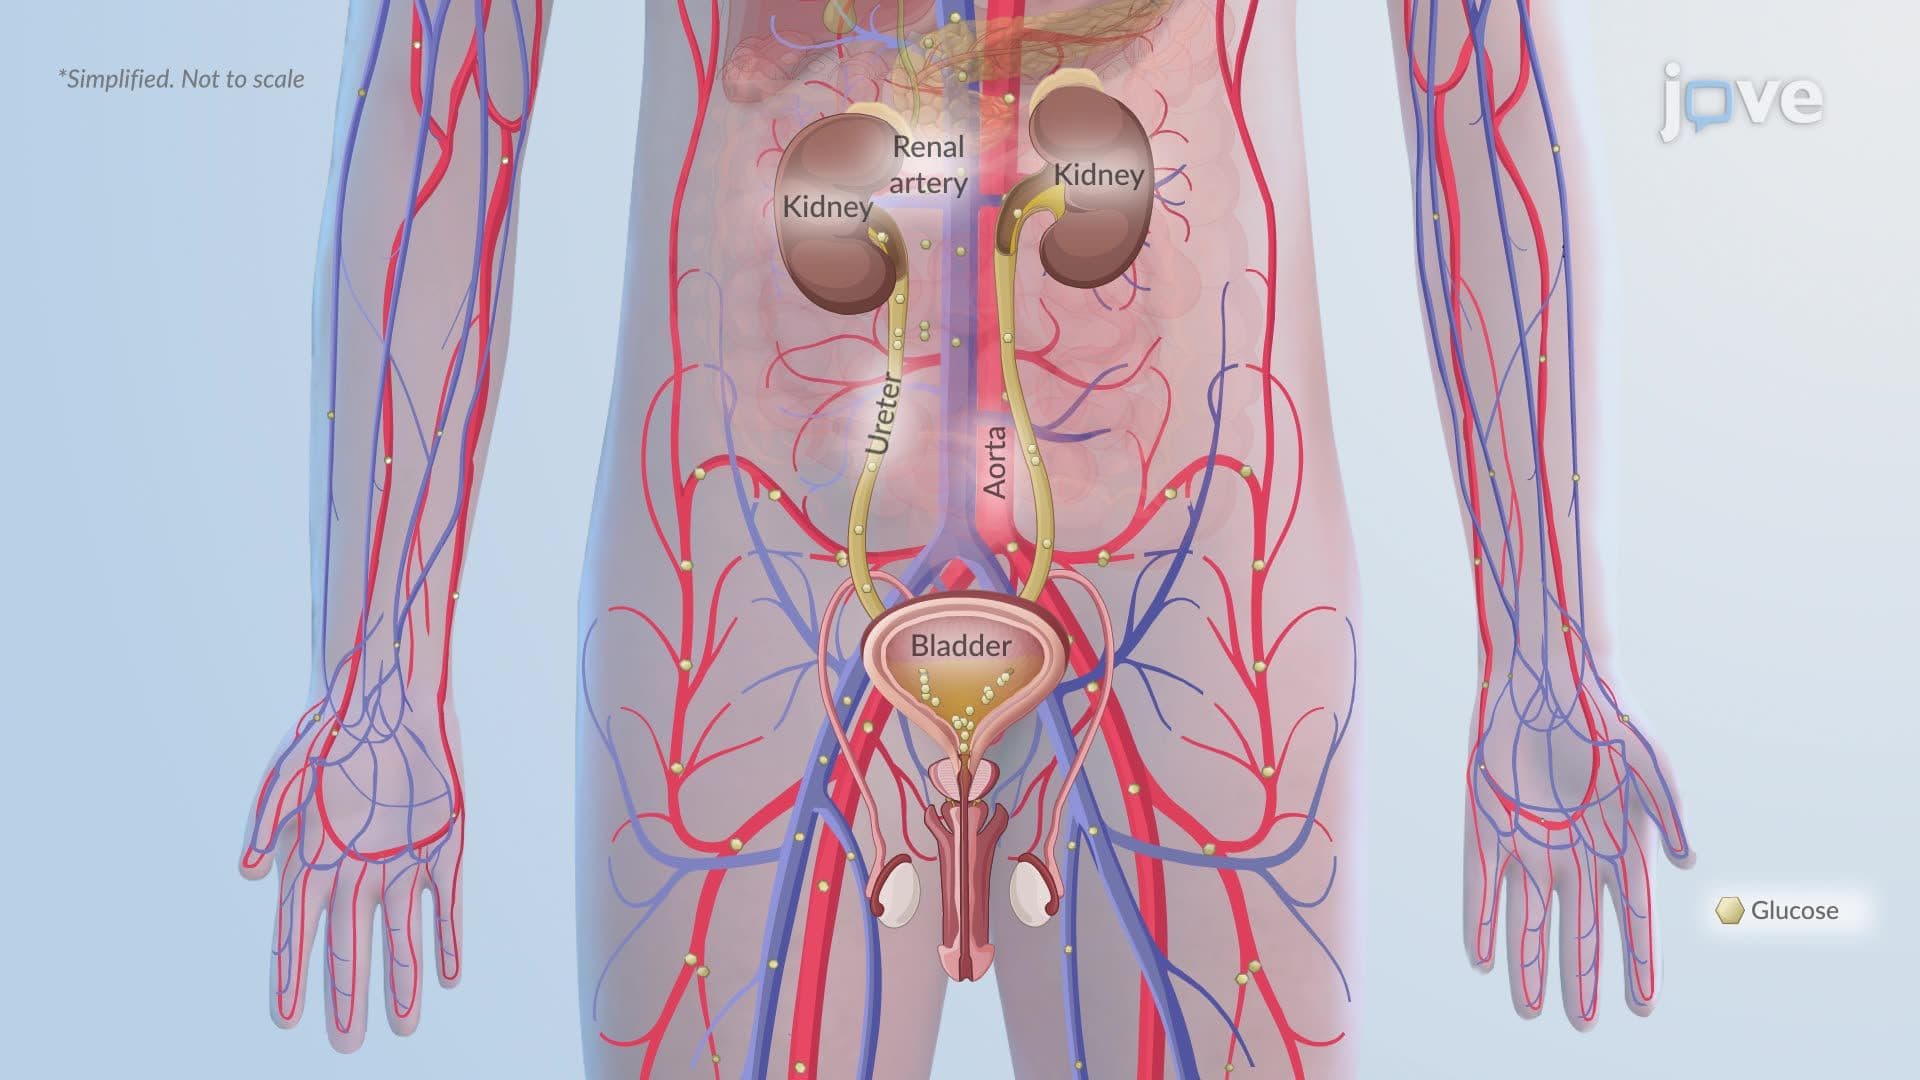 01:22
Diabetic Ketoacidosis ll: Pathophysiology
 01:25
Diabetic Ketoacidosis l: Introduction
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:20
Acute Kidney Injury V: Interprofessional Care