Related Experiment Video
Updated: Aug 15, 2026
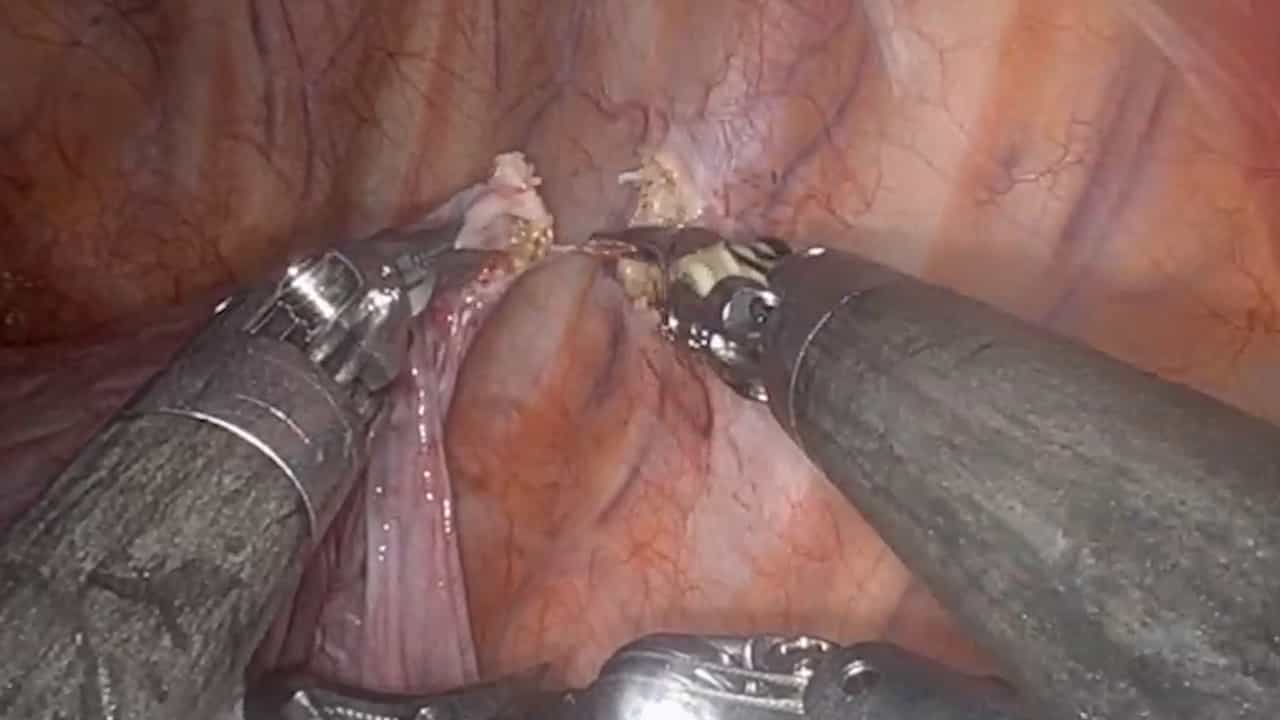

Robotic-assisted Left Pneumonectomy For Vanishing Lung Syndrome
Published on: January 23, 2026
Massive lung collapse with partial resolution after several years: a case report
Elke Govaere1, Dirk Van Raemdonck, Hugo Devlieger
1Dept of Pediatrics, University Hospital of Leuven, Herestraat 49, 3000 Leuven, Belgium. Elke.Govaere@olvz-aalst.be

Insights
Bronchitis obliterans, a rare lung complication in children, can be treated conservatively. This approach may lead to partial lung re-expansion, suggesting surgery as a last resort.
Area of Science:
- Pediatric Pulmonology
- Critical Care Medicine
Background:
- Bronchitis obliterans is a severe complication of pediatric respiratory infections.
- It leads to significant lung collapse (atelectasis).
- Historically, surgical lung resection was the standard treatment for survivors.
Observation:
- A case of infant bronchitis obliterans treated conservatively is presented.
- The infant underwent non-surgical management for the condition.
Findings:
- Partial lung re-expansion was observed 5 years post-initial event.
- Conservative management demonstrated potential for lung recovery.
Implications:
- This case supports conservative treatment for pediatric bronchitis obliterans.
- Pneumonectomy (lung removal) should be considered only when other options fail.
Background:
Bronchitis obliterans is a severe and extremely rare complication of respiratory tract infections in children and is characterized by massive atelectasis and collapse of the affected lung. Of the rare cases reported in the literature all surviving children underwent surgical resection of the collapsed lung.
Case Presentation:
We report an infant with bronchitis obliterans that was treated conservatively. 5 years after the initial event, partial lung re-expansion was documented.
Conclusion:
This case therefore supports a conservative treatment whenever possible with pneumonectomy only as a last treatment option.

Related Concept Videos
 01:10
Atelectasis II: Pathophysiology
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:08
Pneumothorax II: Pathophysiology
 01:17
Pulmonary Cycle: Exhalation
 01:30
Acute Respiratory Failure-III