Related Experiment Video
Updated: Aug 15, 2026

Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Resection extent versus postoperative outcomes of seizure and memory in mesial temporal lobe epilepsy
Eun Yeon Joo1, Hyun Jung Han, Eun Kyung Lee
1Department of Neurology, Samsung Medical Center and Center for Clinical Medicine, SBRI, Sungkyunkwan University School of Medicine, 50 Irwon-Dong, Gangnam-Gu, Seoul 135-710, Korea.

Objectives:
To investigate the effects of the resection of hippocampus and temporal neocortex on postsurgical seizure and memory outcomes in mesial temporal lobe epilepsy (mTLE) patients.
Methods:
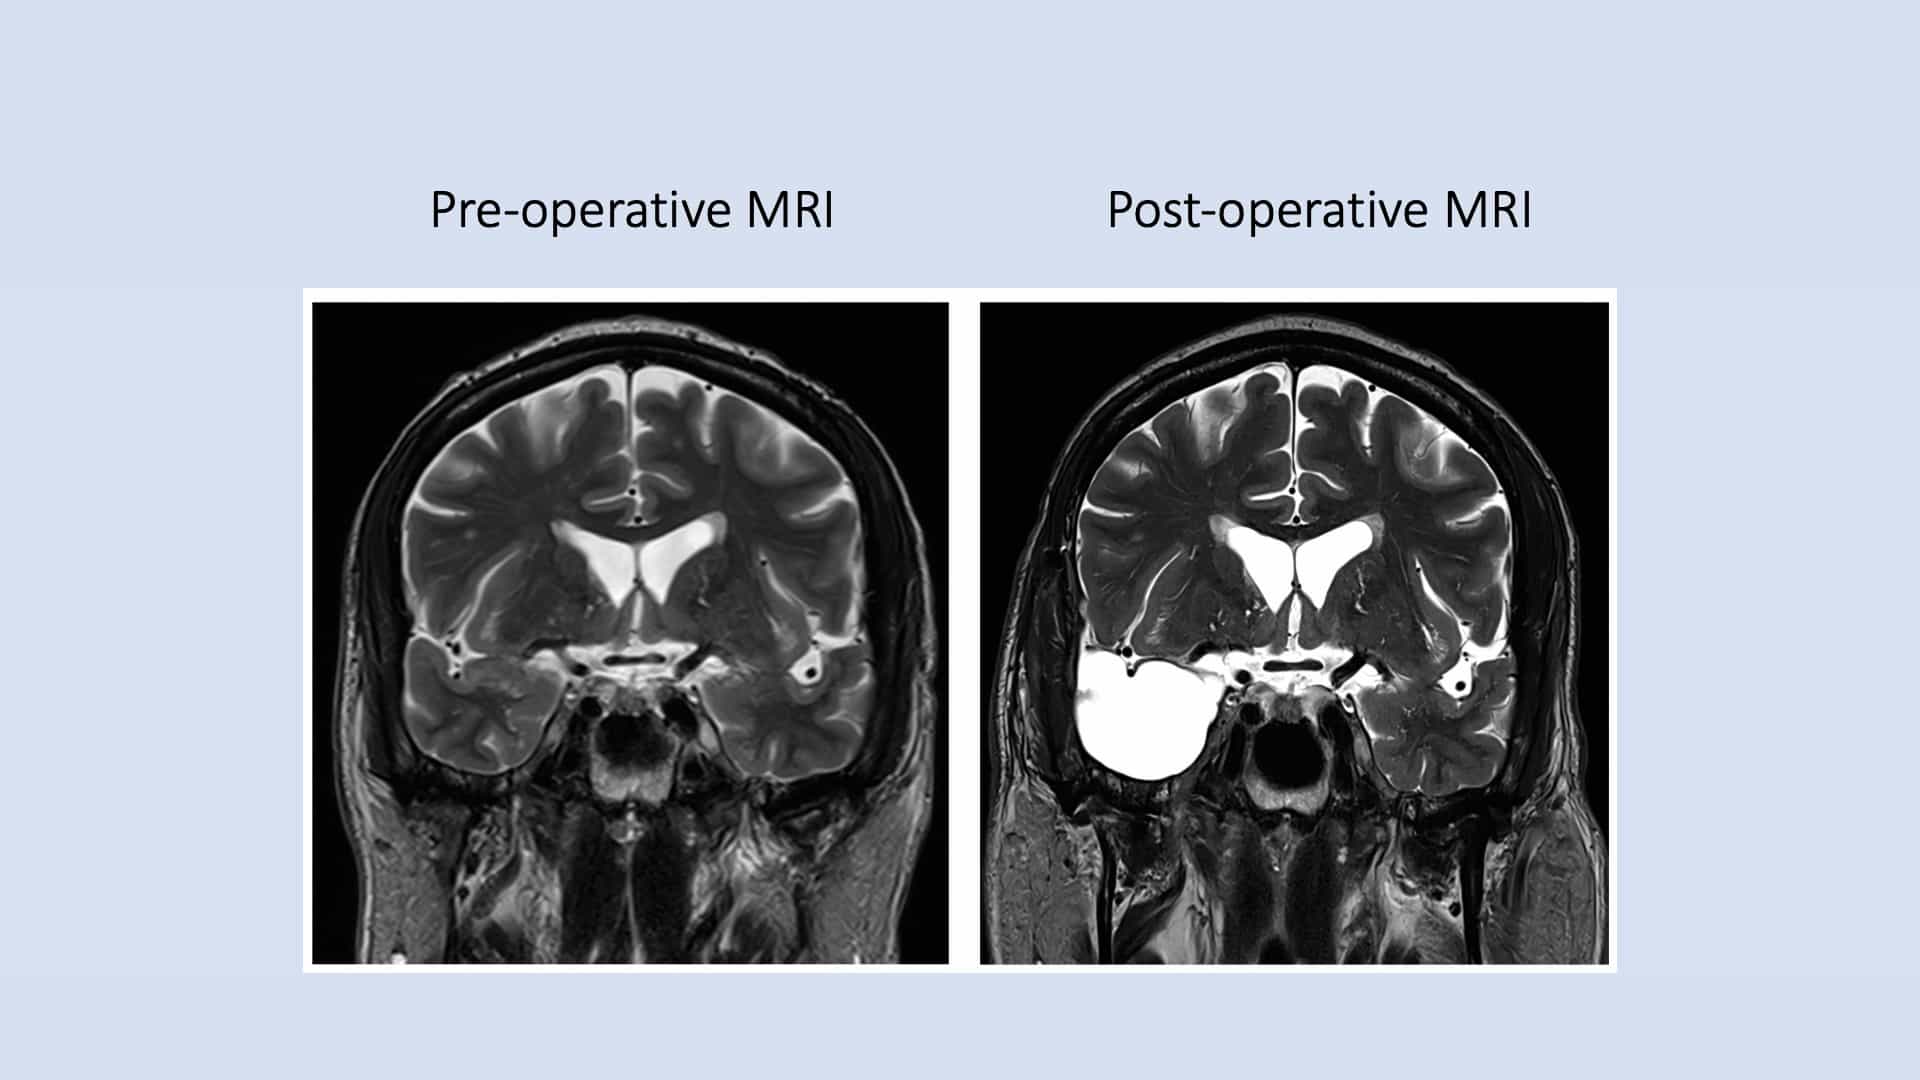
Sixty-eight mTLE patients underwent pre- and postsurgical brain magnetic resonance imaging (MRI). The patients were divided into seizure-free group (SF, N=54) and non-seizure-free group (NSF, N=14). The resection length of hippocampus was determined by the difference between presurgical and postsurgical hippocampus lengths in MRIs. The lengths of resected temporal gyri were measured on three-dimensional MRI reconstruction. Among SF group, 37 patients performed pre- and postsurgical neuropsychological tests. The postsurgical memory decline (PMD) was calculated by subtracting postsurgical memory score from presurgical one in verbal and visual memory tests.
Results:
The resection length of hippocampus in SF was significantly longer than in NSF (32.7 +/- 7.7 mm versus 25.1 +/- 7.3 mm, t-test, p=0.002), regardless of intersubject difference in the extent of hippocampal sclerosis (logistic regression, p=0.003) while the resection lengths of the lateral temporal gyri were not different between SF and NSF. Overall postsurgical change of verbal or visual memory was not significant. However, regression analysis showed a significant correlation between the resection length of inferior or basal temporal gyrus and verbal PMD (p<0.001) in left TLE patients with seizure-free outcome.
Conclusion:
More resection of hippocampus may predict a better postsurgical seizure-free outcome. The larger resection of inferior or basal temporal gyrus seems to be related to a postsurgical verbal memory decline in left TLE patients.
Insights
Greater hippocampal resection improves seizure control in mesial temporal lobe epilepsy (mTLE) patients. However, extensive temporal neocortex resection may increase verbal memory decline in left mTLE patients.
Area of Science:
- Neurosurgery
- Epilepsy Research
- Neuroimaging
Background:
- Mesial temporal lobe epilepsy (mTLE) is a common form of epilepsy often treated with surgery.
- Surgical outcomes regarding seizure control and memory function vary among patients.
- Understanding the relationship between resection extent and outcomes is crucial for patient management.
Purpose of the Study:
- To evaluate the impact of hippocampus and temporal neocortex resection on seizure and memory outcomes in mTLE patients.
- To identify predictors of successful seizure control and postsurgical memory decline.
Main Methods:
- Sixty-eight mTLE patients underwent pre- and postsurgical MRI for quantitative analysis of resection volumes.
- Patients were categorized into seizure-free (SF) and non-seizure-free (NSF) groups.
- Neuropsychological tests assessed verbal and visual memory changes, calculating postsurgical memory decline (PMD).
Main Results:
- Significantly larger hippocampal resection lengths were observed in the SF group compared to the NSF group (p=0.002).
- Resection lengths of lateral temporal gyri did not differ between groups.
- A significant correlation was found between larger inferior or basal temporal gyrus resection and verbal PMD in left TLE patients achieving seizure freedom (p<0.001).
Conclusions:
- Increased hippocampal resection volume is associated with a higher likelihood of seizure-free outcomes in mTLE.
- Extensive resection of the inferior or basal temporal gyrus may predict verbal memory decline in left mTLE patients with successful seizure control.
- Tailoring surgical resection extent is important to balance seizure control and cognitive preservation.