Efficiency of the Genius batch hemodialysis system with low serum solute concentrations: the case of lithium intoxication therapy
Related Experiment Videos
Annemieke Dhondt1, Alain Verstraete, Koen Vandewoude
1Renal Division, Department of Internal Medicine, Ghent University, Belgium. annemie.dhondt@Ugent.be

Background:
The Genius batch system consists of a 90-L closed reservoir, from which fresh dialysate is extracted at the top and to which spent dialysate is returned at the bottom. It was shown in long-term hemodialysis patients that almost the entire amount of unspent dialysate can be used before contamination of fresh with spent dialysate occurs. Separation is caused by differences in density, partly because of the presence of uremic solutes in spent dialysate. The question is raised whether this separation can be maintained during dialysis of patients who experience an intoxication without renal failure.
Methods:
A patient intoxicated with lithium was dialyzed using the Genius system, prepared at 37 degrees C, during 300 minutes. With dialysate flow set at 300 mL/min (5 mL/s) and in the absence of mixing, urea is not expected at the inlet dialysate tubing before minute 300.
Results:
In the dialysate inlet tubing, an abrupt increase in lithium and urea concentrations was observed 210 minutes after the start of the session, reflecting contamination of fresh with spent dialysate. At minute 210, only 60.9 L of 90 L of dialysate had crossed the dialyzer. In a control dialysis treatment in a patient with marked renal failure, this mixing occurred only at 300 minutes.
Conclusion:
In the present observation, it is shown that during Genius dialysis in a patient without renal failure, an earlier contamination of fresh with spent dialysate can occur, compared to conditions of renal failure.
Related Concept Videos
 01:30
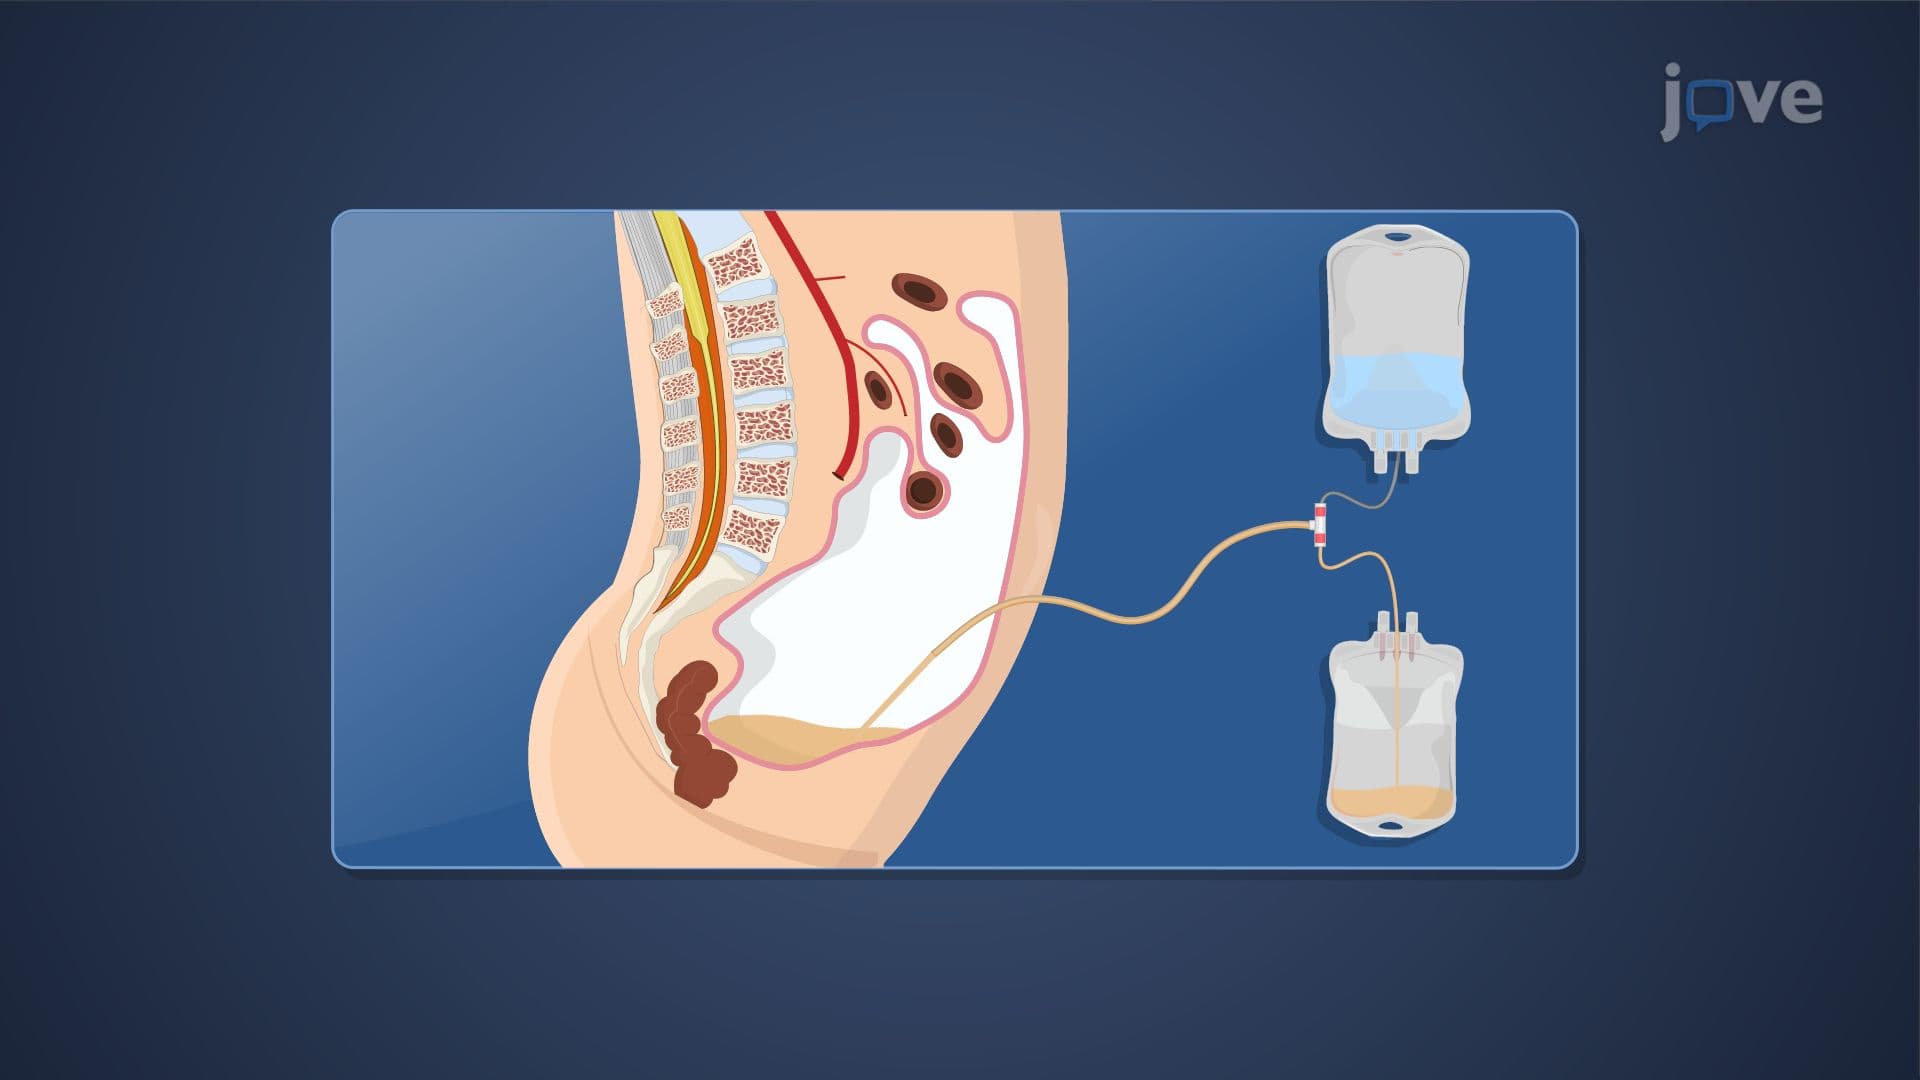
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:15
Dialysis
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:25
Extracorporeal Removal of Drugs: Hemoperfusion and Hemofiltration
 01:26
Enhanced Elimination of Poison
Antidotes serve a crucial role in counteracting the effects of poison by inhibiting enzymes responsible for producing harmful drug metabolites. In some cases, these toxic metabolites can be neutralized by endogenous cosubstrates, which are maintained at specific concentrations to prevent interaction with cellular macromolecules and subsequent cell death.
Renal excretion is the...