Related Experiment Video
Updated: Aug 14, 2026

Measurement and Analysis of Extracellular Acid Production to Determine Glycolytic Rate
Published on: December 12, 2015
Circulating anions usually associated with the Krebs cycle in patients with metabolic acidosis
Lui G Forni1, William McKinnon, Gwyn A Lord
1Department of Critical Care, Worthing Hospital, Worthing, West Sussex, UK. lui.forni@wash.nhs.uk

Introduction:
Acute metabolic acidosis of non-renal origin is usually a result of either lactic or ketoacidosis, both of which are associated with a high anion gap. There is increasing recognition, however, of a group of acidotic patients who have a large anion gap that is not explained by either keto- or lactic acidosis nor, in most cases, is inappropriate fluid resuscitation or ingestion of exogenous agents the cause.
Methods:
Plasma ultrafiltrate from patients with diabetic ketoacidosis, lactic acidosis, acidosis of unknown cause, normal anion gap metabolic acidosis, or acidosis as a result of base loss were examined enzymatically for the presence of low molecular weight anions including citrate, isocitrate, alpha-ketoglutarate, succinate, malate and d-lactate. The results obtained from the study groups were compared with those obtained from control plasma from normal volunteers.
Results:
In five patients with lactic acidosis, a significant increase in isocitrate (0.71 +/- 0.35 mEq l-1), alpha-ketoglutarate (0.55 +/- 0.35 mEq l-1), malate (0.59 +/- 0.27 mEq l-1), and d-lactate (0.40 +/- 0.51 mEq l-1) was observed. In 13 patients with diabetic ketoacidosis, significant increases in isocitrate (0.42 +/- 0.35 mEq l-1), alpha-ketoglutarate (0.41 +/- 0.16 mEq l-1), malate (0.23 +/- 0.18 mEq l-1) and d-lactate (0.16 +/- 0.07 mEq l-1) were seen. Neither citrate nor succinate levels were increased. Similar findings were also observed in a further five patients with high anion gap acidosis of unknown origin with increases in isocitrate (0.95 +/- 0.88 mEq l-1), alpha-ketoglutarate (0.65 +/- 0.20 mEq l-1), succinate (0.34 +/- 0.13 mEq l-1), malate (0.49 +/- 0.19 mEq l-1) and d-lactate (0.18 +/- 0.14 mEq l-1) being observed but not in citrate concentration. In five patients with a normal anion gap acidosis, no increases were observed except a modest rise in d-lactate (0.17 +/- 0.14 mEq l-1).
Conclusion:
The levels of certain low molecular weight anions usually associated with intermediary metabolism were found to be significantly elevated in the plasma ultrafiltrate obtained from patients with metabolic acidosis. Our results suggest that these hitherto unmeasured anions may significantly contribute to the generation of the anion gap in patients with lactic acidosis and acidosis of unknown aetiology and may be underestimated in diabetic ketoacidosis. These anions are not significantly elevated in patients with normal anion gap acidosis.

Related Concept Videos
 01:29
Roles of Electrolytes: Chloride and Bicarbonate
Conditions such as hypochloremia can arise from insufficient chloride reabsorption by the kidneys, often compounded by extended bouts of diarrhea, vomiting, or...
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and HCO3− values are examined to...
 01:29
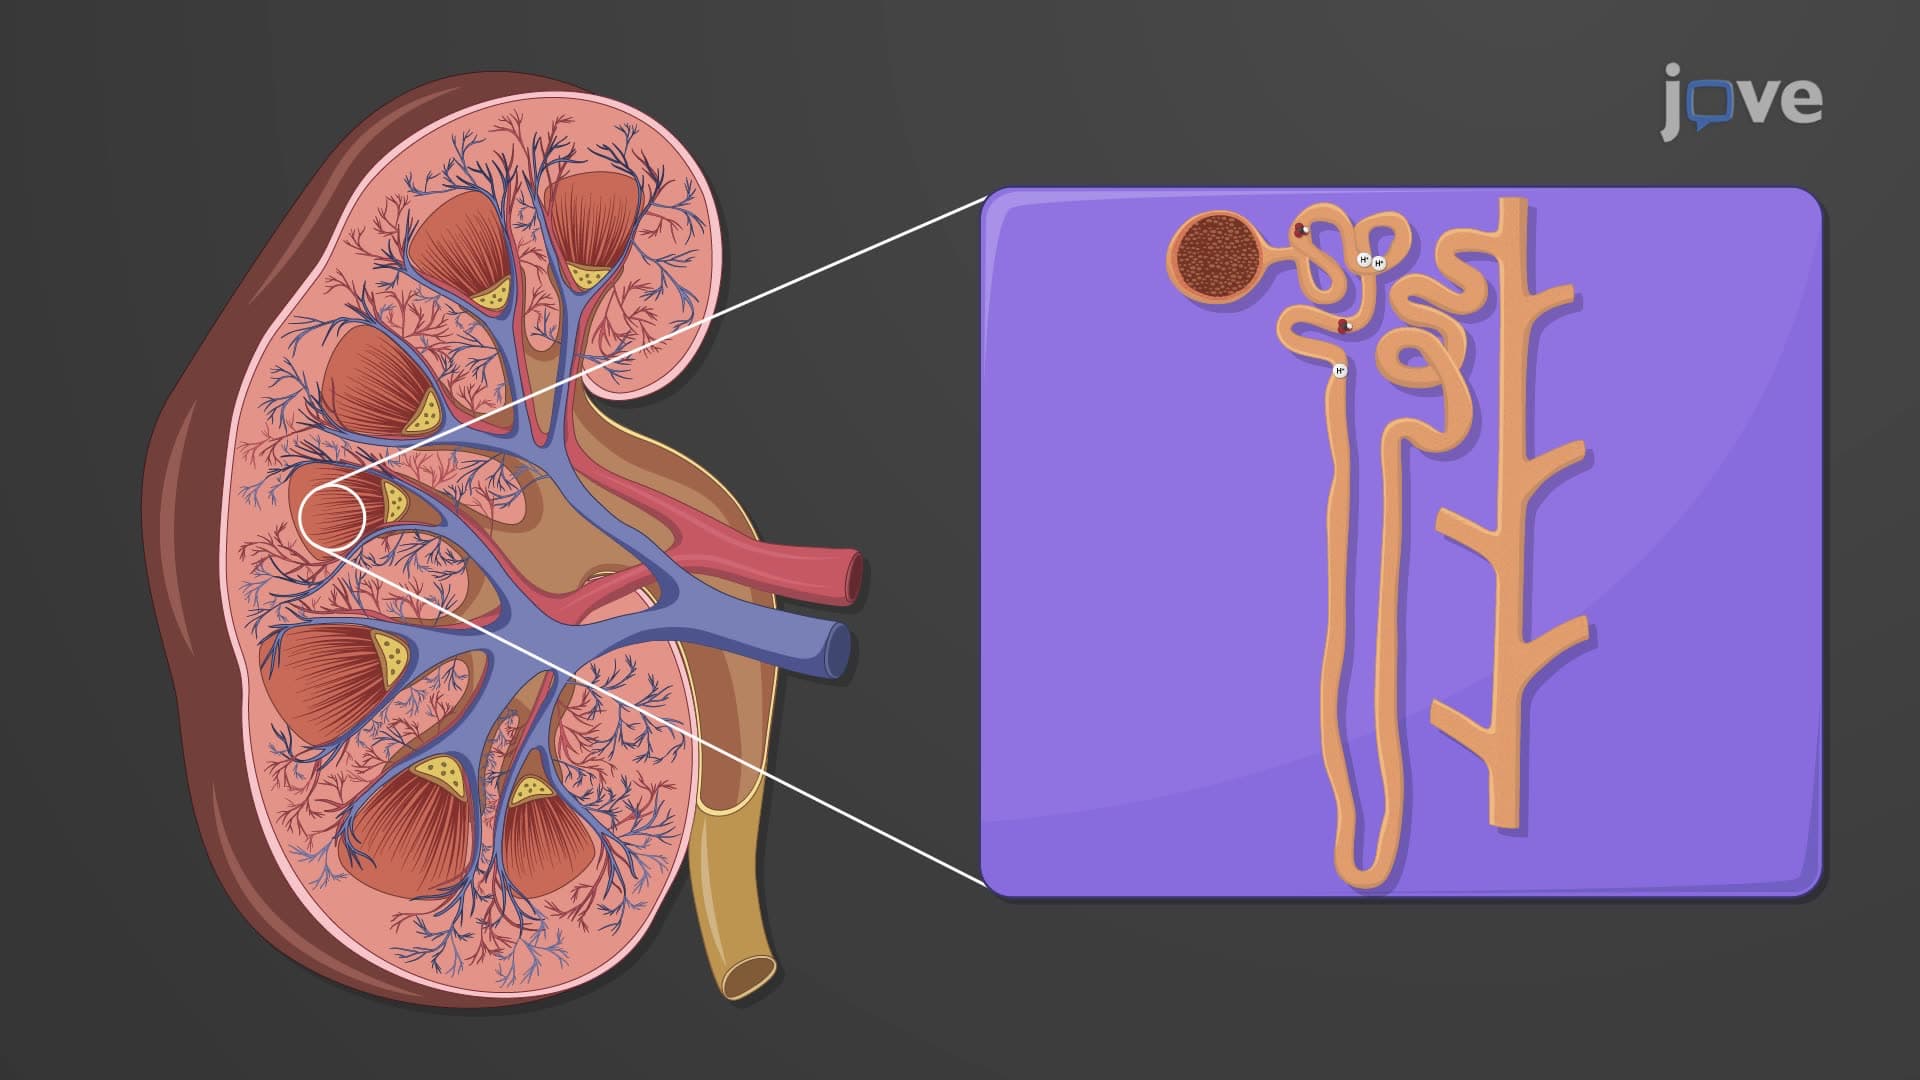
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:29
Disorders of Acid-Base Balance
Respiratory Acidosis and Alkalosis
Respiratory acidosis occurs due to an increase in the partial pressure of carbon dioxide PCO2 in the blood. It often arises from shallow breathing or impaired gas exchange caused by...
 01:22
Bicarbonate-Carbonic Acid Buffer
 01:25
Acid-Base Balance
When the pH of arterial blood rises above 7.45, it results in a condition called alkalosis. Conversely, a drop below 7.35 leads to...