Related Experiment Videos

Acute severe spinal cord dysfunction in a child with meningitis: Streptococcus pneumoniae and Mycoplasma pneumoniae

Celine Manteau1, Jean Michel Liet, Jocelyne Caillon

  • 1Paediatric Intensive Care Unit, Mothers' and Children's Hospital, Nantes Teaching Hospital, Nantes, France.

Abstract

Insights

An 11-year-old experienced sudden tetraplegia due to pneumococcal meningitis. Prompt treatment with ceftriaxone, erythromycin, and dexamethasone led to complete neurological recovery.

Area of Science:

  • Neurology
  • Infectious Diseases
  • Pediatrics

Background:

  • Pneumococcal meningitis can lead to severe neurological complications.
  • Mycoplasma pneumoniae coinfection is a potential, though less common, factor in pediatric meningitis.

Observation:

  • An 11-year-old presented with abrupt onset tetraplegia during pneumococcal meningitis.
  • Brainstem-spinal cord junction showed hyperintensities on MRI.
  • Serological tests confirmed Mycoplasma pneumoniae infection.

Findings:

  • The patient received ceftriaxone for pneumococcal meningitis and erythromycin and dexamethasone for suspected Mycoplasma pneumoniae coinfection.
  • Neurological function fully recovered within 10 days.

Implications:

  • This case highlights the importance of considering and treating Mycoplasma pneumoniae coinfection in meningitis.
  • Aggressive management including antibiotics and corticosteroids can reverse severe neurological deficits in pediatric meningitis.

Related Concept Videos

Bacterial Meningitis I: Introduction01:22

Bacterial Meningitis I: Introduction

Bacterial meningitis is a severe, life-threatening inflammation of the meninges, particularly the pia mater and arachnoid mater, affecting the subarachnoid space, ventricles, and cerebrospinal fluid (CSF). If untreated, it can lead to significant neurological complications or death.Causative AgentsCommon pathogens vary with age and immune status. In adults, major organisms include Streptococcus pneumoniae, Neisseria meningitidis, and Haemophilus influenzae. Streptococcus agalactiae (group B...
Viral Meningitis01:18

Viral Meningitis

Viral meningitis is the most common form of meningitis and is often referred to as aseptic meningitis to indicate the absence of bacterial involvement. It is generally milder than bacterial meningitis, with symptoms including fever, headache, stiff neck, drowsiness, nausea, photophobia, and vomiting. Rarely, more severe manifestations or death may occur. Common causative agents include enteroviruses, particularly coxsackie A and B viruses and echoviruses, all members of the Enterovirus genus...
Bacterial Meningitis II: Pathophysiology01:26

Bacterial Meningitis II: Pathophysiology
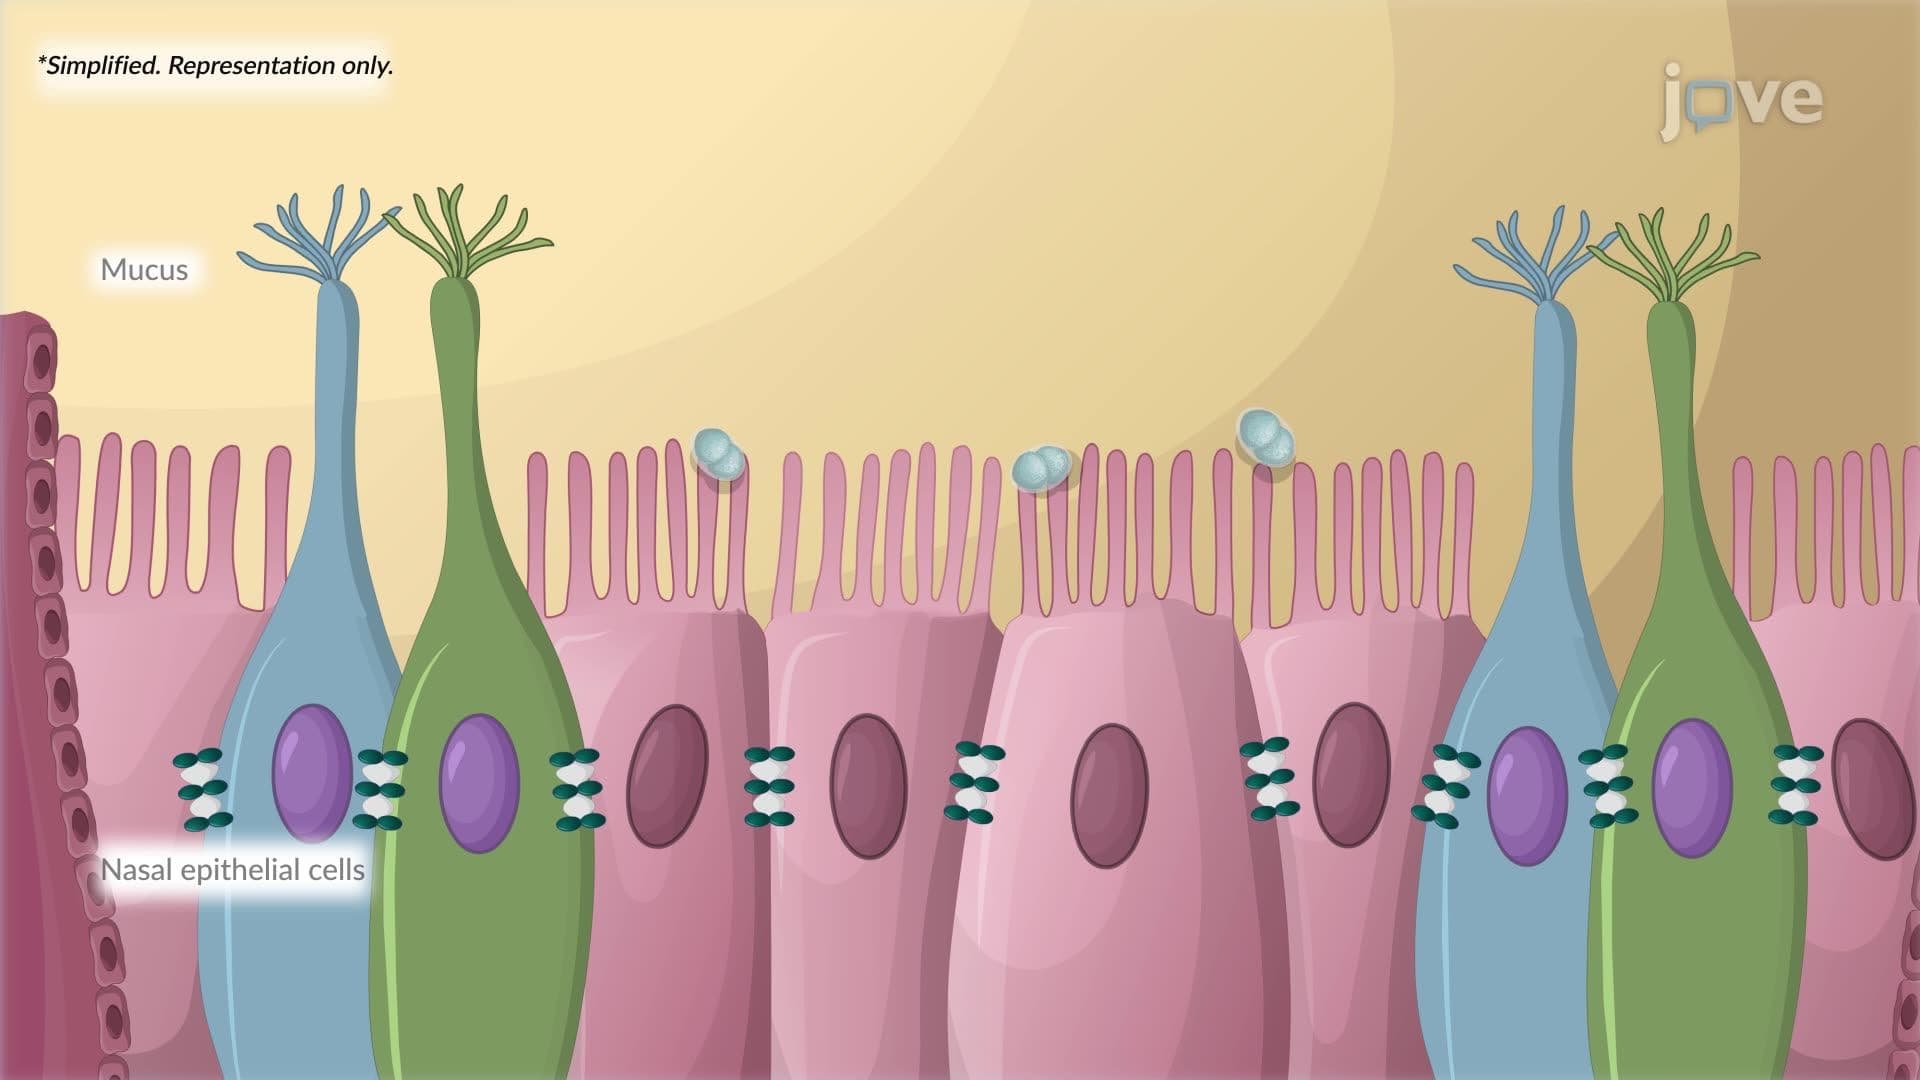
Bacterial meningitis typically begins when pathogens such as Neisseria meningitidis and Streptococcus pneumoniae colonize the nasopharynx and invade the bloodstream. This process is facilitated by bacterial virulence factors, such as polysaccharide capsules, which resist phagocytosis and complement-mediated killing. Less commonly, bacteria reach the central nervous system via contiguous spread from infections like otitis media or sinusitis, through congenital or acquired dural defects, or...
Bacterial Meningitis01:24

Bacterial Meningitis

Bacterial meningitis is a severe infectious disease involving inflammation of the meninges, the protective membranes surrounding the brain and spinal cord. It occurs when pathogenic bacteria cross the blood–brain barrier and enter the cerebrospinal fluid. Common causative organisms include Neisseria meningitidis, Streptococcus pneumoniae, Haemophilus influenzae type b, Listeria monocytogenes, and Escherichia coli K1. The exact route of entry varies by pathogen and host condition.Routes of Entry...
Atypical Pneumonia01:14

Atypical Pneumonia

Atypical pneumonia, often caused by Mycoplasma pneumoniae, is a form of pulmonary infection that differs from the classical presentation of bacterial pneumonia in both its cause and clinical symptoms. Mycoplasma pneumoniae is a pleomorphic bacterium notable for its lack of a rigid cell wall. This structural characteristic imparts resistance to beta-lactam antibiotics and significantly influences the bacterium’s behavior within the human host.Other pathogens responsible for the disease include...
Secondary Spinal Cord Injury llI: Pathophysiology01:25

Secondary Spinal Cord Injury llI: Pathophysiology

Early Ischemia and Ionic ImbalanceWithin minutes of spinal cord injury, a secondary cascade begins, progressing over hours to weeks. Vascular damage reduces blood flow, causing ischemia and mitochondrial dysfunction. ATP depletion leads to ion pump failure, membrane depolarization, sodium influx, potassium efflux, and water accumulation, resulting in cellular swelling. Increased intracellular calcium further disrupts mitochondria and accelerates cellular injury.Excitotoxicity and Neuronal...

