Related Experiment Video
Updated: Aug 14, 2026
Surgical Techniques for Catheter Placement and 5/6 Nephrectomy in Murine Models of Peritoneal Dialysis
Published on: July 19, 2018
[Use of fragmin in program hemodialysis of patients with terminal chronic renal failure]

Abstract:
The subjects of the study were 60 patients at the end stage of chronic renal failure of various origins, who were on program hemodialysis (PHD) in Dialysis Center of City hospital #20. The main group consisted of 25 patients, who were administered fragmin (Pfizer, USA), a low-molecular heparin, for hypocoagulation during the procedure of hemodialysis. The drug was administered in a bolus dose of 5000 aXa ICU into the arterial line after connecting it to a fistula needle. The control group (35 patients) received unfranctionated heparin (UFH) in a conventional way (a bolus of 2000 to 2500 IU before the beginning of the procedure, followed by 1200 to 1500 IU/h in a continuous infusion, stopped 1 hour prior to the end of the dialysis). The following parameters were measured at the beginning and the end of the procedure: the number of thrombocytes, hemoglobin and hematocrit levels, activated partial thromboplastin time, activated coagulation time, antithrombin III level, and anti-Xa factor activity. Standard regimen of UFH administration allowed satisfactory hypocoagulation, but the necessary dose was hard to select. A bolus dose of fragmin led to adequate hypocoagulation in all the patients: there were no fibrin or blood clots in the lines or the dialyzer, or hemorrhage from the sites of puncture after the procedure. Anti-Xa-factor activity grew after a bolus injection of fragmin. By the end of the procedure the inhibitory activity of fragmin towards Xa-factor remained at the level of 0.44 +/- 0.7 IU/ml. The results show that a single dose of fragmin is effective and safe during a standard procedure of hemodialysis lasting up to 5 hours.
Related Concept Videos
 01:24
Hemodialysis II: Procedure and Complications
 01:25
Hemodialysis I: Introduction
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:30
Continuous Renal Replacement Therapy
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:30
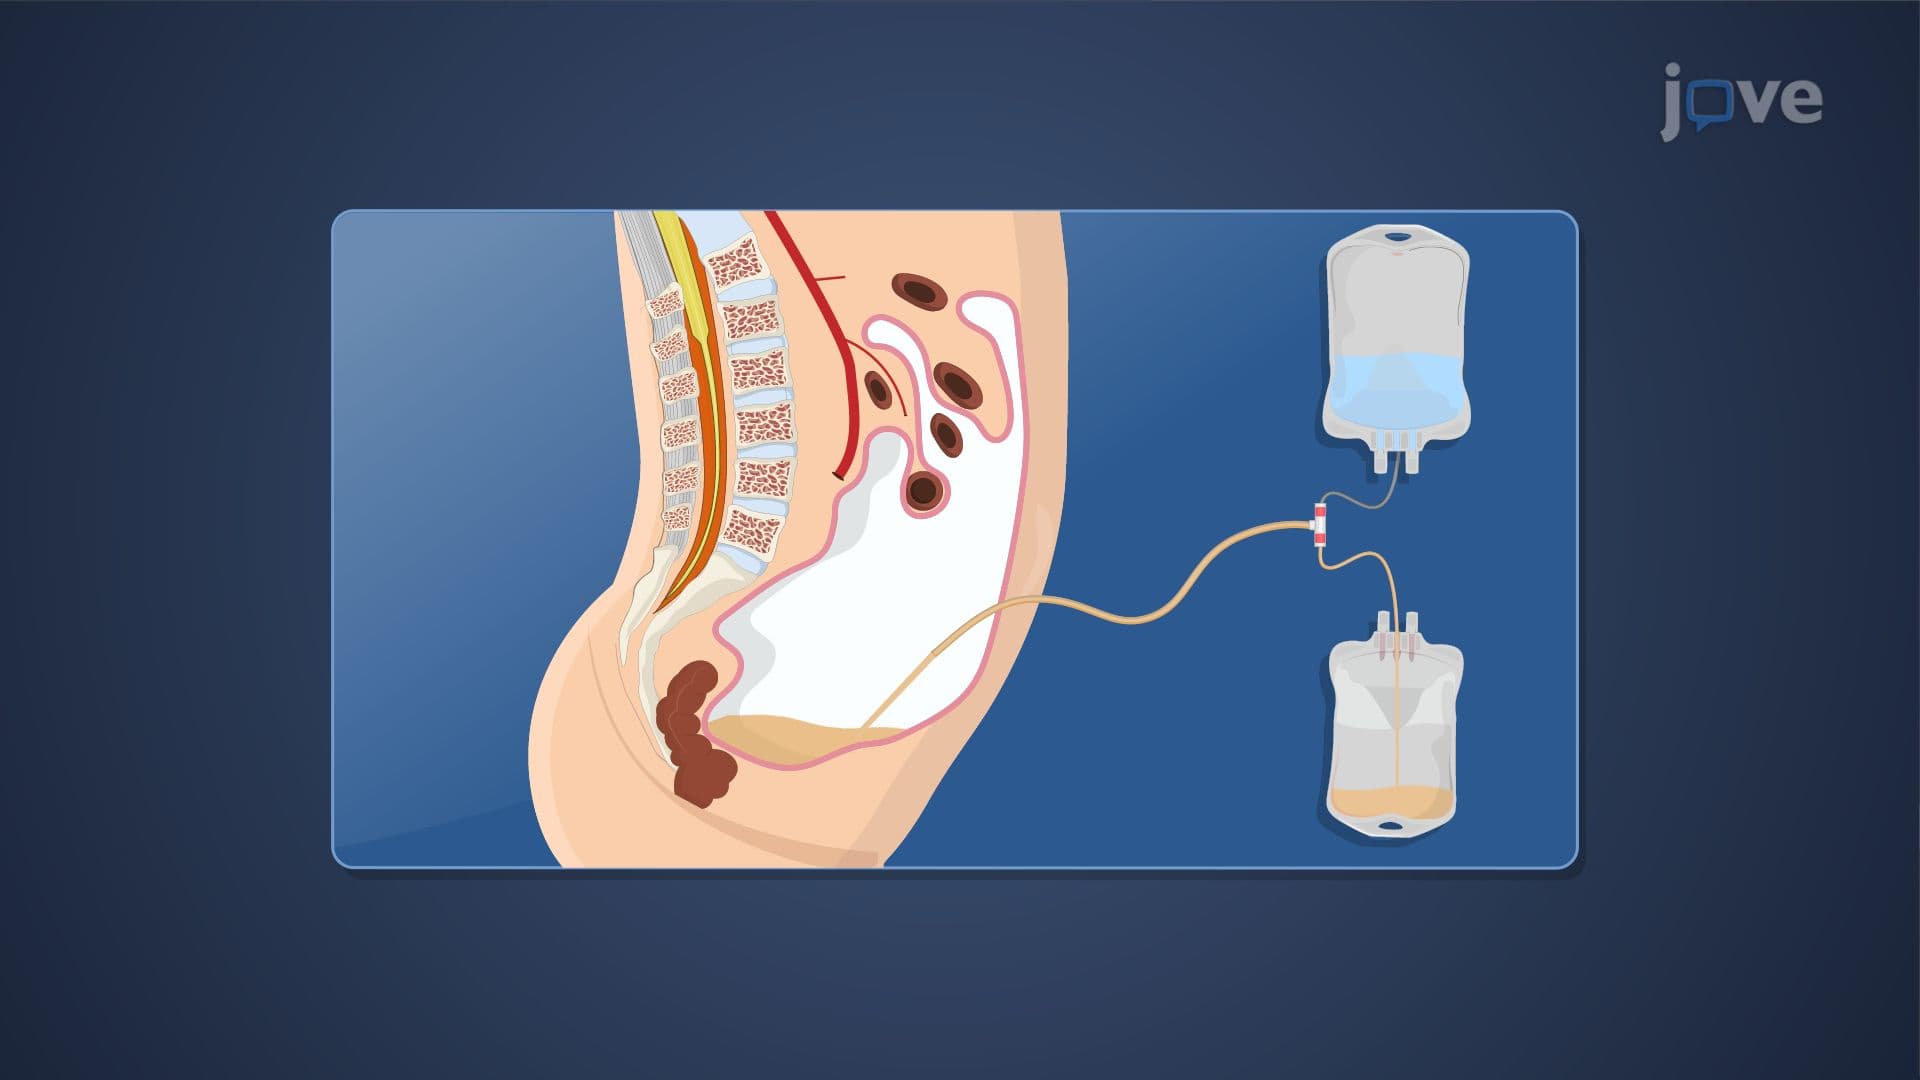
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis