
Large hiatal hernia and iron deficiency anaemia: clinico-endoscopical findings
1Department of Gastro-enterelogy, AZ Groeninge, Kortrijk, Belgium.

Background:
Iron deficiency anaemia (IDA) in men and postmenopausal women is mostly due to chronic gastrointestinal blood loss. One of the most common missed lesions while performing upper endoscopy in the work-up of IDA, are Cameron lesions, located at the neck of a large hiatal hernia.
Aims:
Description of the bio-clinical and endoscopic findings of a large hiatal hernia, diagnosed in patients presenting with iron deficiency anaemia. Furthermore, a review of the literature concerning the diagnostic and therapeutic management of these patients will be outlined.
Study:
We retrospectively evaluated 36 patients, presenting with IDA (hemoglobin < 10 g/dl) associated with a large hiatal hernia.
Results:
Cardiopulmonary complications of anaemia were the presenting symptoms, rather than gastrointestinal related complaints or bleeding. Cameron lesions were visualized only in 18 (50%) of our patients at their first presentation. There was no obvious correlation between the presence of Cameron lesions and visible gastrointestinal blood loss. Initially, almost all of our patients were treated medically. Seven underwent surgical repair of the hiatal hernia and all remained asymptomatic afterwards.
Conclusion:
We conclude that a hiatal hernia, with or without visible Cameron lesions, is a real and maybe underestimated cause of IDA. Finding a large hiatal hernia on upper endoscopy, together with a negative colonoscopy, completes the diagnostic work-up of IDA in most of these elderly patients. Currently, no guidelines concerning the optimal therapeutic management of this problem are available. Therapy may depend upon the need of transfusion, the efficiency of medical treatment, the risks of surgery and the preference and general condition of the patient.
Related Concept Videos
 01:25
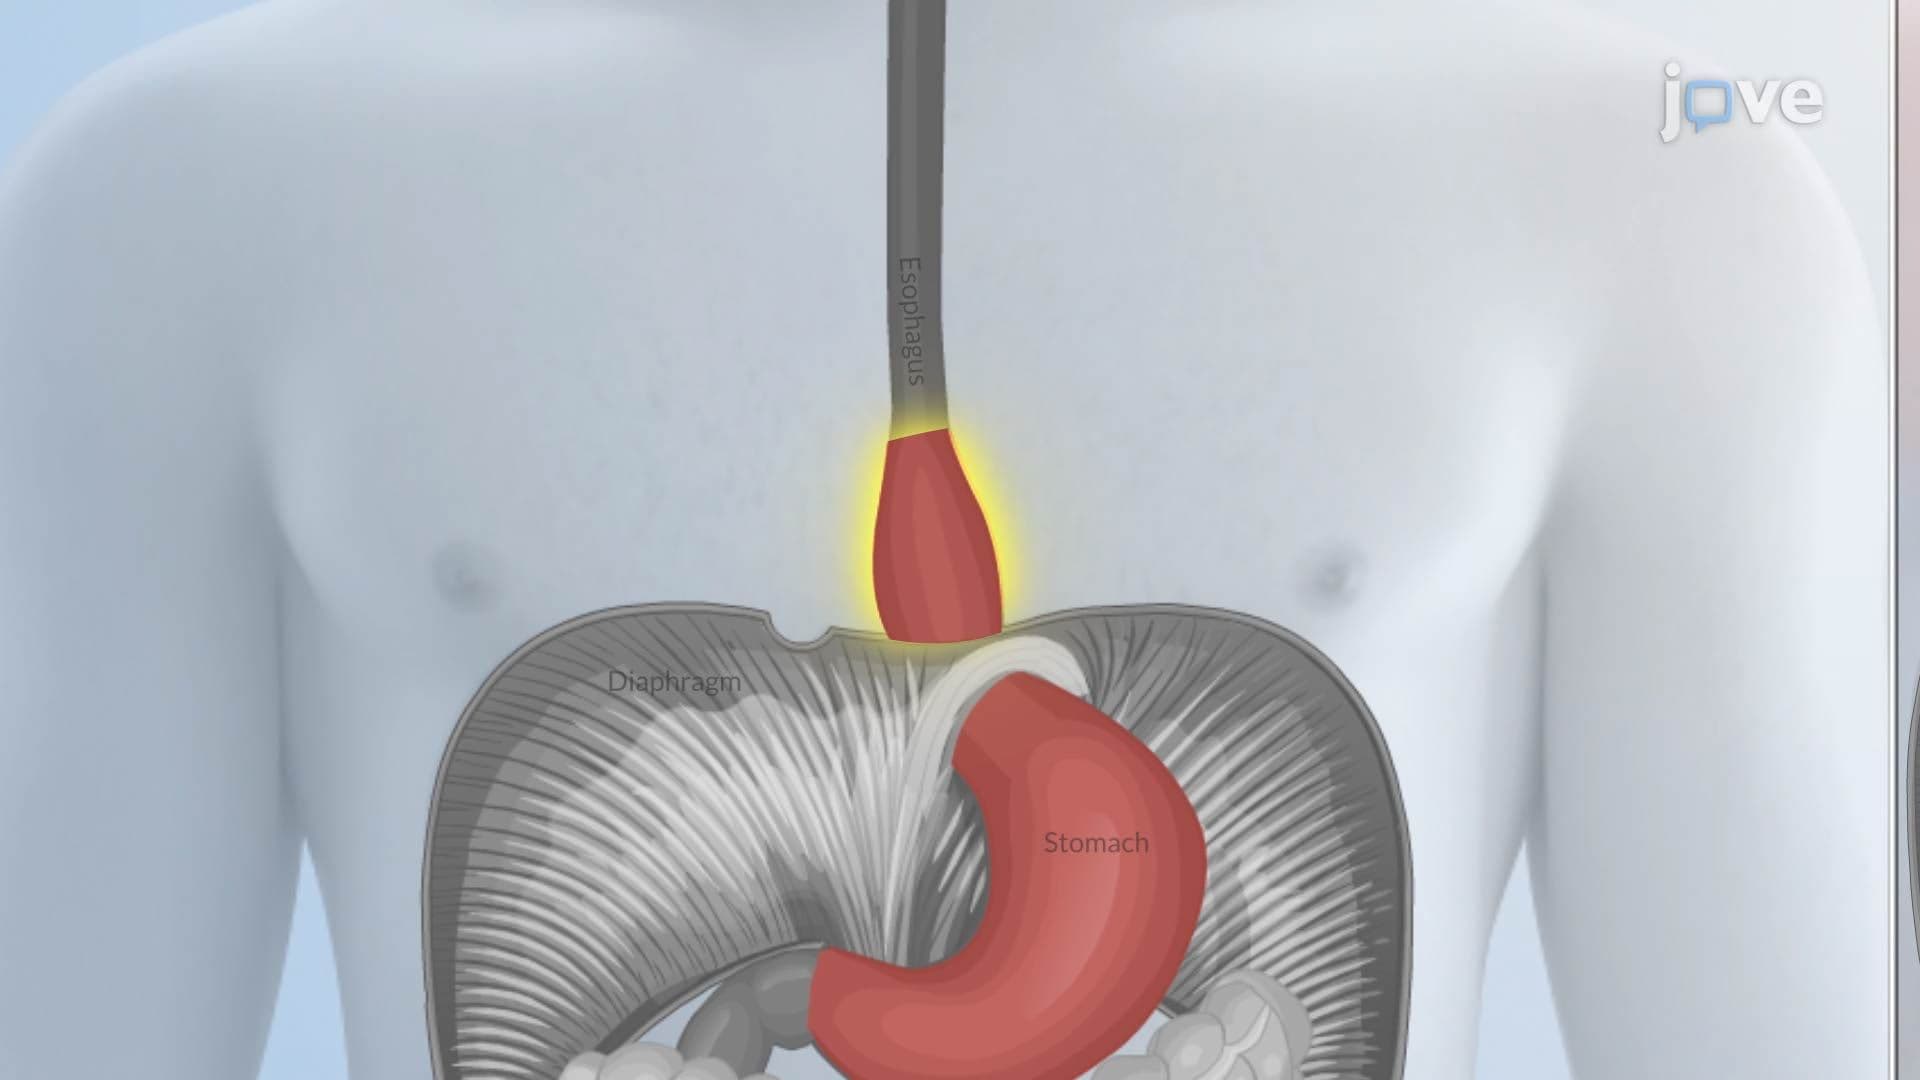
Hiatal Hernia
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...