Related Experiment Video
Updated: Aug 14, 2026
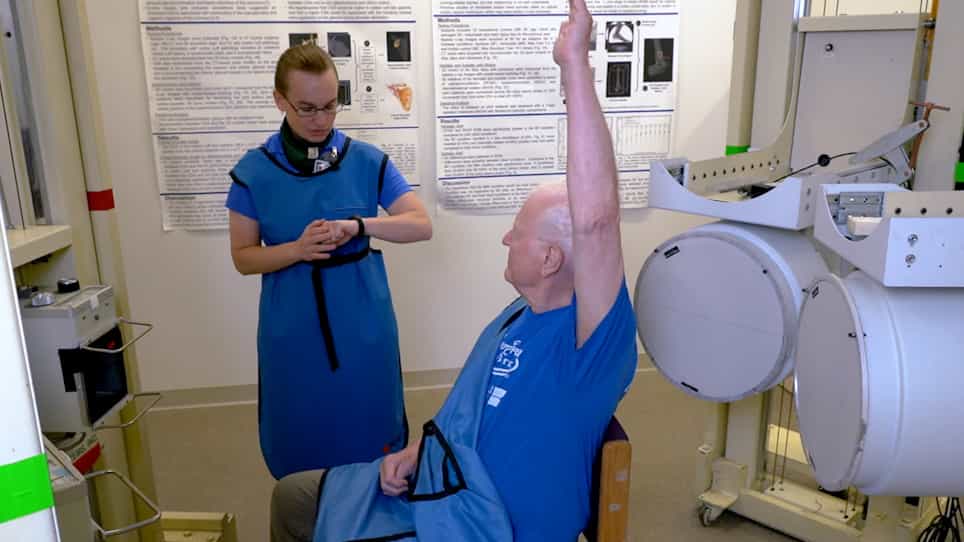
Measuring 3D In-vivo Shoulder Kinematics using Biplanar Videoradiography
Published on: March 12, 2021
Glenohumeral range of motion deficits and posterior shoulder tightness in throwers with pathologic internal
Joseph B Myers1, Kevin G Laudner, Maria R Pasquale
1ATC, Neuromuscular Research Laboratory, UPMC Center for Sports Medicine, 3200 South Water Street, Pittsburgh, PA 15203, USA. myersjb@upmc.edu

Background:
Alterations in glenohumeral range of motion, including increased posterior shoulder tightness and glenohumeral internal rotation deficit that exceeds the accompanying external rotation gain, are suggested contributors to throwing-related shoulder injuries such as pathologic internal impingement. Yet these contributors have not been identified in throwers with internal impingement.
Hypothesis:
Throwers with pathologic internal impingement will exhibit significantly increased posterior shoulder tightness and glenohumeral internal rotation deficit without significantly increased external rotation gain.
Study Design:
Case control study; Level of evidence, 3.
Methods:
Eleven throwing athletes with pathologic internal impingement diagnosed using both clinical examination and a magnetic resonance arthrogram were demographically matched with 11 control throwers who had no history of upper extremity injury. Passive glenohumeral internal and external rotation were measured bilaterally with standard goniometry at 90 degrees of humeral abduction and elbow flexion. Bilateral differences in glenohumeral range of motion were used to calculate glenohumeral internal rotation deficit and external rotation gain. Posterior shoulder tightness was quantified as the bilateral difference in passive shoulder horizontal adduction with the scapula retracted and the shoulder at 90 degrees of elevation. Comparisons were made between groups with dependent t tests (P < .05).
Results:
The throwing athletes with internal impingement demonstrated significantly greater glenohumeral internal rotation deficit (P = .03) and posterior shoulder tightness (P = .03) compared with the control subjects. No significant differences were observed in external rotation gain between groups (P = .16).
Clinical Relevance:
These findings could indicate that a tightening of the posterior elements of the shoulder (capsule, rotator cuff) may contribute to impingement. The results suggest that management should include stretching to restore flexibility to the posterior shoulder.

Related Concept Videos
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...
 01:23
Muscles of the Shoulder
Anterior Thoracic Muscles
The anterior thoracic muscles include the serratus anterior, subclavius, and...