Related Experiment Video
Updated: Feb 11, 2026


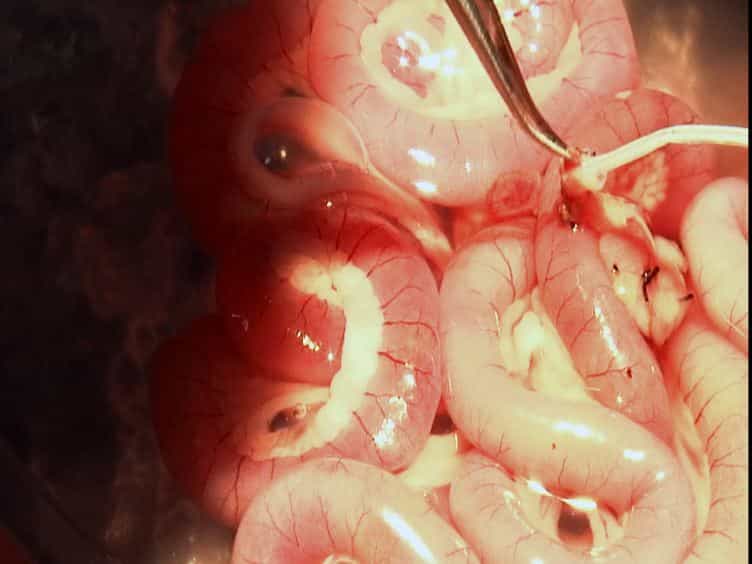
Murine Ileocolic Bowel Resection with Primary Anastomosis
Published on: October 29, 2014
Influence of time on risk of bowel resection in complete small bowel obstruction
Nina A Bickell1, Alex D Federman, Arthur H Aufses
1Department of Health Policy, Mount Sinai School of Medicine, New York, NY 10029, USA.

Background:
Little is known about the effect of passing time on risk of resection among patients with complete small bowel obstruction. We sought to provide a benchmark of the relationship of time from symptom onset to surgical treatment on the need for resection in patients with complete small bowel obstruction.
Study Design:
We performed an observational study of patients with surgically treated complete small bowel obstruction at an inner-city urban tertiary referral center and a municipal hospital. Patients were sampled randomly retrospectively (n=60), and prospectively (n=81), for a final sample of 141. Detailed clinical and time data were abstracted from medical records including out-of-hospital examinations. Risk of resection was calculated using actuarial life table methods. Linear regression was used to determine factors affecting time to treatment.
Results:
All patients were treated surgically for obstruction; 45% underwent resection. Resected patients had longer (11 days versus 8 days; p=0.01) and more complicated (31% versus 14% in ICU; p=0.01) hospital stays. The risk of resection was 4% among patients with 24 hours of unresponsive symptoms; it increased to 10% to 14% through 96 hours, then dropped slightly but did not disappear. Patients treated first with a tube had longer times between first examination and operation, system-time (40.6 hours versus 10.2 hours; p=0.0007), but this was not associated with an increased resection risk. System-times were shorter among patients seen first in the emergency department (median: 25.7 hours versus 59.7 hours; p=0.0001).
Conclusions:
Physicians should be cautious in postponing surgery beyond 24 hours in patients with unresponsive symptoms from complete obstruction. The risk of resection rises dramatically, remains elevated through 96 hours of unresolved symptoms, then declines but does not disappear.

Related Concept Videos
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...
 01:17
Irritable Bowel Syndrome I: Introduction
IBS is a chronic condition that can persist over a long period or recur frequently.
The pathogenesis of IBS involves a complex interplay of the following factors:
Altered...
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:30
Inflammatory Bowel Disease II: Crohn's Disease
Inflammatory bowel disease, commonly known as IBD, refers to a collection of disorders that lead to persistent inflammation of the gastrointestinal tract. The two types of IBD are ulcerative colitis, which impacts the colon, and Crohn's disease, which can involve any part of the gastrointestinal segment.
Crohn's disease
Crohn's disease is a chronic, systemic inflammatory bowel disease (IBD) that predominantly affects the gastrointestinal tract. It is marked by...
 01:29
Inflammatory Bowel Disease IV: Pharmacological Management
Pharmacologic...