Related Experiment Video
Updated: Aug 14, 2026
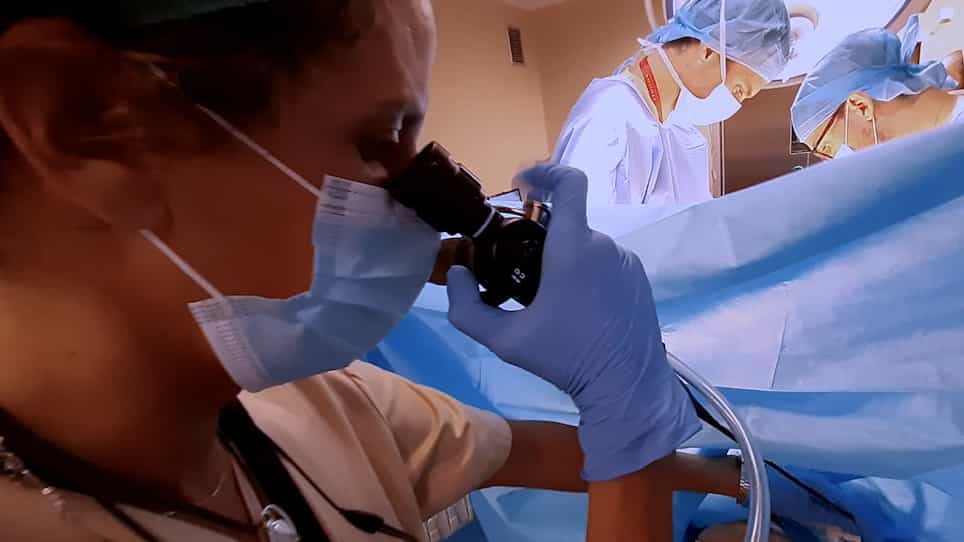
Lung Rapid Recovery Procurement Combined with Abdominal Normothermic Regional Perfusion in Controlled Donation after Circulatory Death
Published on: August 15, 2022
Intensive care unit extubation does not preclude extrarenal organ recovery from donors after cardiac death
Scott R Johnson1, Martha Pavlakis, Khalid Khwaja
1Division of Transplant Surgery, Department of Surgery, Beth Israel Deaconess Medical Center and Harvard Medical School, Boston, MA 02215, USA. srjohnso@bidmc.harvard.edu

Background:
We have sought to increase the utilization of both renal and extrarenal organs from donors after cardiac death (DCD), including DCD donors with ICU extubation.
Methods:
Extubation occurred in the intensive care unit (ICU; n=15) and operating room (OR; n=5). The charts of donors were reviewed for demographics, cause of death, time of asystole and cold perfusion. Recipient's charts were reviewed for graft function, length of hospitalization, serum creatinine (Cr) at discharge and last follow-up. Peak transaminases, amylase, and lipase for liver and pancreas recipients were also reviewed. Data are presented as means+/-SEM.
Results:
From December 2002 until December 2004, 20 DCD donors were utilized yielding 34 kidney transplants (33 recipients), five liver (1 liver-kidney), and two pancreas (SPK) transplants. Mean follow-up overall is 260 days. ICU extubation occurred in 26/33 (78.8%) kidneys, 3/5(60%) livers and 1/2 (50%) pancreata performed. Time from extubation to asystole was 15.9+/-1.9 min and overall warm ischemia time was 12.5+/-1.0 min. Serum Cr at discharge and at last follow-up for renal grafts are 4.3+/-0.5 and 1.9+/-0.3 mg/dl, respectively. Peak AST and ALT levels after OLTx were 3620+/-951 and 1955+/-266 i.u., respectively. Peak and discharge total bilirubin were 8.1+/-0.9 and 2.5+/-0.5 mg/dl. Length of hospitalization was 9.6+/-1.0 and 15.8+/-2.3 days for kidney and liver recipients, respectively. Both pancreas recipients were insulin free after transplant.
Conclusions:
ICU extubation should not eliminate extrarenal organs from consideration and may be preferable to OR extubation by improving family support and eliminating OR staff concerns about their role in end-of-life care.

Related Concept Videos
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:28
Kidney Transplant I: Introduction