Combining beta-adrenergic and peroxisome proliferator-activated receptor gamma stimulation improves lipoprotein composition in healthy moderately obese subjects
Related Experiment Video
Updated: Aug 14, 2026
Measurement of Basal and Forskolin-stimulated Lipolysis in Inguinal Adipose Fat Pads
Published on: July 21, 2017
Thomas A Hughes1, Frankie Stentz, Thomas Gettys
1Health Science Center, Department of Medicine, University of Tennessee, Memphis, TN 38163, USA. thughes303@aol.com

Abstract:
Current pharmacological regimens for hypertriglyceridemia and low high-density lipoprotein (HDL) are limited to the peroxisome proliferator-activated receptor (PPAR) alpha activating fibrates, niacin, and statins. This pilot study examined the impact of simultaneous stimulation of cyclic adenosine monophosphate with a beta-adrenergic agonist and PPARgamma with pioglitazone (PIO) on lipoprotein composition in moderately obese, healthy subjects. Subjects were treated with PIO (45 mg) to stimulate PPARgamma or a combination of ephedrine (25 mg TID), a beta-agonist, with caffeine (200 mg TID), a phosphodiesterase inhibitor (ephedrine plus caffeine), or both for 16 weeks. Lipoproteins were separated by gradient ultracentrifugation into very low-density lipoprotein (VLDL), intermediate-density lipoprotein, low-density lipoprotein (LDL), and 3 HDL (L, M, and D) subfractions. Apolipoproteins were measured by high-performance liquid chromatography. PIO alone reduced the core triglyceride (TG) content relative to cholesterol ester (CE) in VLDL (-40%), IDL (-25%), and HDL-M (-38%). Ephedrine plus caffeine alone reduced LDL CE (-13%), phospholipids (-9%), and apolipoprotein (apo) B (-13%); increased HDL-M LpA-I (HDL containing apoA-I without apoA-II, 28%), CE/TG (23%), and CE/apoA-I (8%) while reducing apoA-II (-10%); and increased HDL-L LpA-I (29%). Combination therapy reduced total plasma TG (-28%), LDL cholesterol (LDL-C, -10%), apoB (-16%), apoB/apoA-I ratio (-21%) while increasing HDL cholesterol (HDL-C, 21%), total plasma apoA-I (12%), LpA-I (43%), and apoC-I (26%). It also reduced VLDL total mass (-34%) and apoC-III (-39%), LDL CE (-13%), apoB (-13%), and total mass (-11%). Combination therapy increased HDL-L CE/TG (32%), apoC-I (30%), apoA-I (56%), and LpA-I (70%), as well as HDL-M CE (35%), phospholipids (24%), total mass (19%), apoC-I (25%), apoA-I (18%), and LpA-I (56%). In conclusion, simultaneous beta-adrenergic and PPARgamma activation produced beneficial effects on VLDL, LDL, HDL-L, and HDL-M. Perhaps the most important impact of combination therapy was dramatic increases in LpA-I and apoC-I in HDL-L and HDL-M, which were much greater than the sum of the monotherapies. Because LpA-I appears to be the most efficient mediator of reverse-cholesterol transport and a major negative risk factor for cardiovascular disease, this combination therapy may provide very effective treatment of atherosclerosis.
Related Concept Videos
 01:06
Lipid Digestion
 01:20
Lipid-Lowering Drugs: Statins and Miscellaneous Agents
 01:26
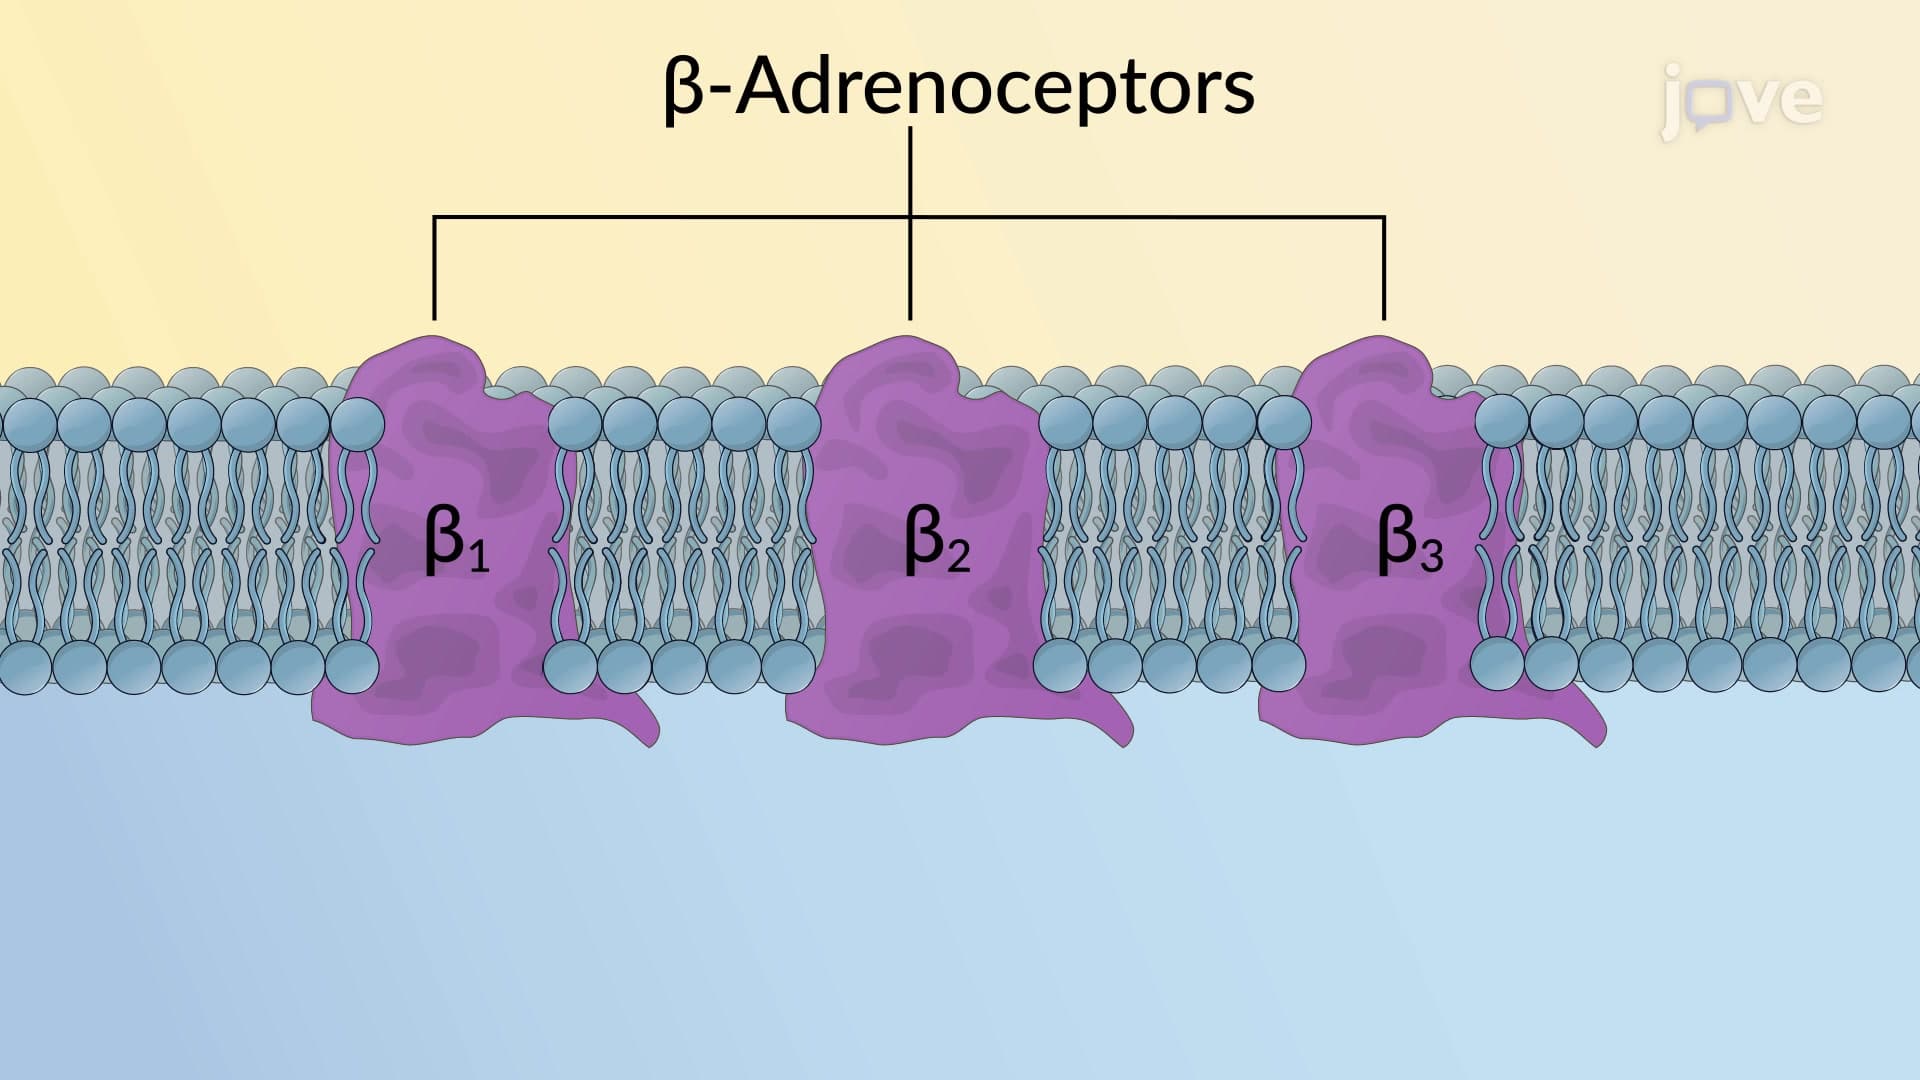
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:29
Cholesterol: Significance and Regulation
Considering cholesterol and...