Related Experiment Video
Updated: Aug 14, 2026

Trabecular Bone Microarchitecture Evaluation in an Osteoporosis Mouse Model
Published on: September 8, 2023
Review: developmental origins of osteoporotic fracture
Cyrus Cooper1, Sarah Westlake, Nicholas Harvey
1MRC Epidemiology Resource Centre and Centre for Developmental Origins of Health and Adult Disease, University of Southampton, Southampton General Hospital, Southampton , SO16 6YD, UK. cc@mrc.soton.ac.uk

Abstract:
Osteoporosis is a major cause of morbidity and mortality through its association with age-related fractures. Although most effort in fracture prevention has been directed at retarding the rate of age-related bone loss and reducing the frequency and severity of trauma among elderly people, evidence is growing that peak bone mass is an important contributor to bone strength during later life. The normal patterns of skeletal growth have been well characterised in cross-sectional and longitudinal studies. It has been confirmed that boys have higher bone mineral content (BMC), but not volumetric bone density, than girls. Furthermore, there is a dissociation between the peak velocities for height gain and bone mineral accrual in both genders. Puberty is the period during which volumetric density appears to increase in both axial and appendicular sites. Many factors influence the accumulation of bone mineral during childhood and adolescence, including heredity, gender, diet, physical activity, endocrine status, and sporadic risk factors such as cigarette smoking. In addition to these modifiable factors during childhood, evidence has also accrued that fracture risk might be programmed during intrauterine life. Epidemiological studies have demonstrated a relationship between birth weight, weight in infancy, and adult bone mass. This appears to be mediated through modulation of the set-point for basal activity of pituitary-dependent endocrine systems such as the HPA and GH/IGF-1 axes. Maternal smoking, diet (particularly vitamin D deficiency), and physical activity also appear to modulate bone mineral acquisition during intrauterine life; furthermore, both low birth size and poor childhood growth are directly linked to the later risk of hip fracture. The optimisation of maternal nutrition and intrauterine growth should also be included within preventive strategies against osteoporotic fracture, albeit for future generations.
More Related Videos


Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:40
Bone Remodeling
 01:31
Osteoclasts in Bone Remodeling
 01:29
Bone Formation by Intramembranous Ossification
The process begins when mesenchymal cells in the embryonic skeleton gather together and differentiate into osteogenic cells, which then develop into...
 01:24
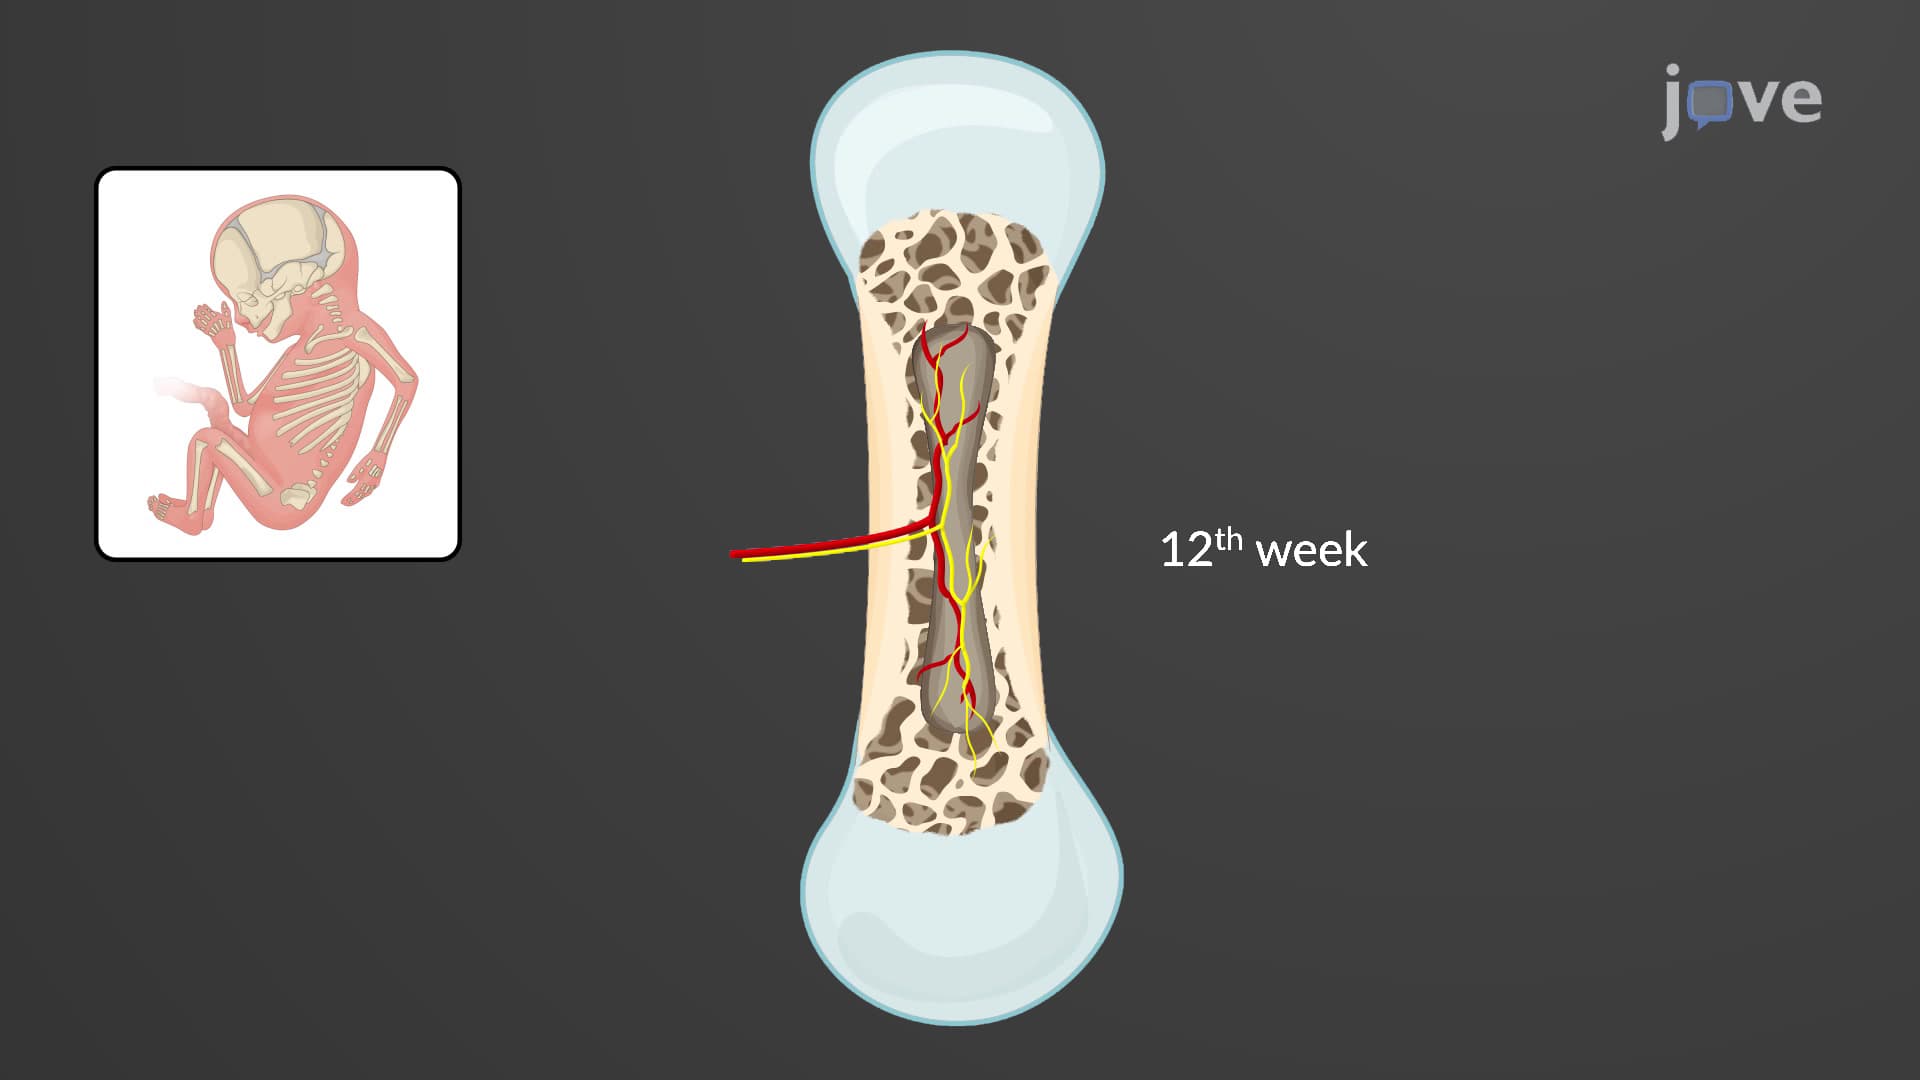
Bone Formation by Endochondral Ossification