Related Experiment Video
Updated: Aug 14, 2026


Quantifiable and Inexpensive Cell-Free Fluorescent Method to Confirm the Ability of Novel Compounds to Chelate Iron
Published on: February 23, 2024
Recent insights into interactions of deferoxamine with cellular and plasma iron pools: Implications for clinical use
J B Porter1, R Rafique, S Srichairatanakool
1Department of Haematology, University College London, London, United Kingdom. j.porter@ucl.ac.uk

Abstract:
Despite the availability of deferoxamine (DFO) for more than three decades, its rates of interaction with cellular iron pools in different tissues, and the effects of its pharmacokinetics on the interaction with plasma iron pools, remain incompletely understood. The positive charge of DFO, together with the negative resting potential in vertebrate cells, favors cellular uptake, whereas the low lipophilicity and high molecular weight counter this effect. The findings presented suggest a facilitated uptake of DFO into hepatocytes, being several hundred-fold faster than into red cells. Antibodies that selectively recognize ferrioxamine (FO) show that initial hepatocellular iron chelation is cytosolic, but later transposes to lysosomal and ultimately canalicular compartments. Strong FO staining is visible in myocytes within 4-8 h after commencing a subcutaneous DFO infusion, indicating effective chelation of myocyte iron. A methodology was developed to study the interaction of DFO and its metabolites with plasma iron pools by stabilizing DFO with aluminum ions, thereby preventing iron shuttling from non-transferrin-bound iron (NTBI) onto DFO after plasma collection. DFO removes only about a third of NTBI rapidly, and NTBI is rarely cleared completely. Increasing DFO dosing does not increase NTBI removal, but instead leads to a greater rebound in NTBI on cessation of intravenous infusion. Thus, intermittent infusions of high-dose DFO are less desirable than continuous infusions at low doses, particularly in high-risk patients. Here the benefits of continuous DFO on heart function occur before changes in T2*-visible storage iron, consistent with early removal of a toxic labile iron pool within myocytes.
More Related Videos

Related Concept Videos
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:24
Microbes and Other Elemental Cycles
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:14
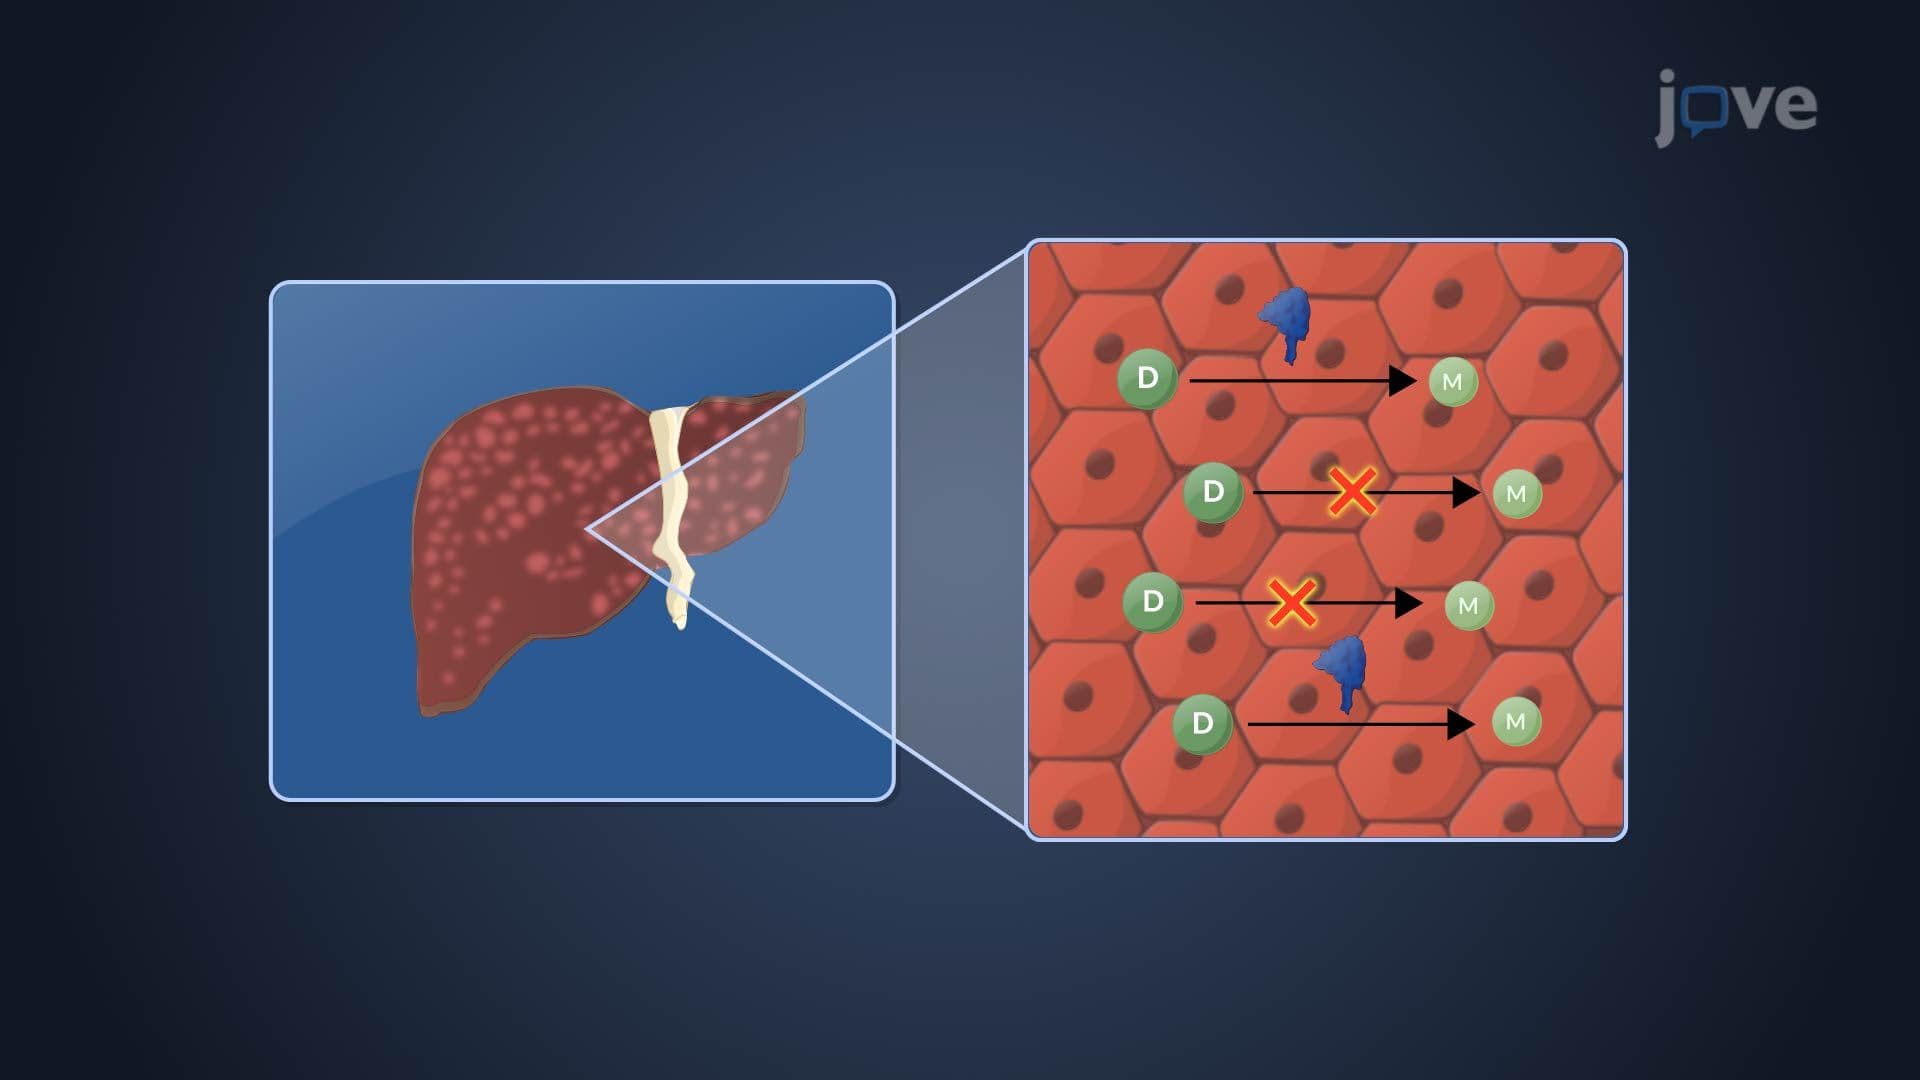
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug
 01:29
Therapeutic Drug Monitoring: Affecting Factors