Related Experiment Video
Updated: Aug 14, 2026

Oral Combinational Antiretroviral Treatment in HIV-1 Infected Humanized Mice
Published on: October 6, 2022
When do children convert from liquid antiretroviral to solid formulations?
Vincent W Yeung1, Ian C K Wong
1Centre for Paediatric Pharmacy Research, The School of Pharmacy, The Institute of Child Health and Great Ormond Street Hospital for Children NHS Trust, University of London, 29-39 Brunswick Square, London WC1N 1AX, UK.

Insights
Children typically switch from liquid to solid antiretroviral formulations around age seven. Stavudine users tend to transition to solid forms earlier than those on other medications.
Area of Science:
- Paediatric pharmacology
- Clinical pharmacy
- HIV/AIDS treatment
Background:
- Liquid antiretroviral formulations are standard for children but present challenges like stability, taste, and travel inconvenience.
- Solid formulations offer a preferred alternative for long-term management in older children, parents, and clinicians.
- Limited research exists on the optimal age for transitioning children from liquid to solid antiretroviral drug forms.
Purpose of the Study:
- To determine the age range for converting children from liquid to solid antiretroviral formulations (abacavir, didanosine, lamivudine, stavudine, zidovudine).
- To assess the retention time of five UK-based liquid antiretroviral formulations and identify factors influencing it.
Main Methods:
- A retrospective survey of medical records at Great Ormond Street Hospital for Children, London.
- Calculation of retention times from liquid treatment initiation to solid formulation conversion using SPSS software.
- Comparison of retention times across different antiretroviral preparations via Cox regression analysis.
Main Results:
- Analysis included 92 pediatric patients.
- The average age for conversion to solid formulations was 7.3 years.
- Patients on stavudine showed a significantly higher likelihood (P < 0.001) of switching to solid forms earlier than those on other medications; over 50% switched within nine months, compared to less than 25% for others.
Conclusions:
- Children generally transition to solid antiretroviral dosage forms around seven years of age.
- Stavudine is associated with an earlier switch to solid formulations in pediatric patients.
Background:
Liquid formulations are usually regarded as the gold standard in paediatric formulation; but sometimes, liquid formulations have stability and taste problems as well as being inconvenient for travelling. Therefore, for the management of long-term illness, some older children, parents and clinicians would prefer to use solid formulations. However, there is a lack of studies to investigate the age at which children are converted from liquid to solid formulations.
Objectives:
(1) To investigate the age range at which children convert from liquid antiretroviral drug formulations to solid formulations, the formulations are abacavir, didanosine, lamivudine, stavudine, and zidovudine. (2) To calculate how long children stay on each of five UK liquid formulations (retention time) and factors affecting the retention times of the above liquid formulations.
Method:
This was a retrospective medical records survey at Great Ormond Street Hospital for Children, London, United Kingdom. Patients' treatment details were entered into SPSS for Windows v. 11.0 and the retention times for the above liquid formulations were calculated i.e., from initiation of the liquid treatment to conversion to solid preparation. The retention times of different preparations were then compared using Cox regression analysis.
Results:
A total of 92 patients are included in the analysis. The overall average age at conversion was 7.3 years (95% CI 6.3-8.2). Patients on stavudine were more likely to switch to the corresponding solid dose form than the other four medicines (P < 0.001); more than 50% of patients on stavudine switched to solid formulation after nine months of treatment, however, less than 25% of patients on other formulations switched during the same period.
Conclusion:
Children taking antiretroviral liquid preparations change to solid dose forms at approximately seven years of age. However, for stavudine, children are more likely to take the solid form at an earlier age.
Related Concept Videos
 01:28
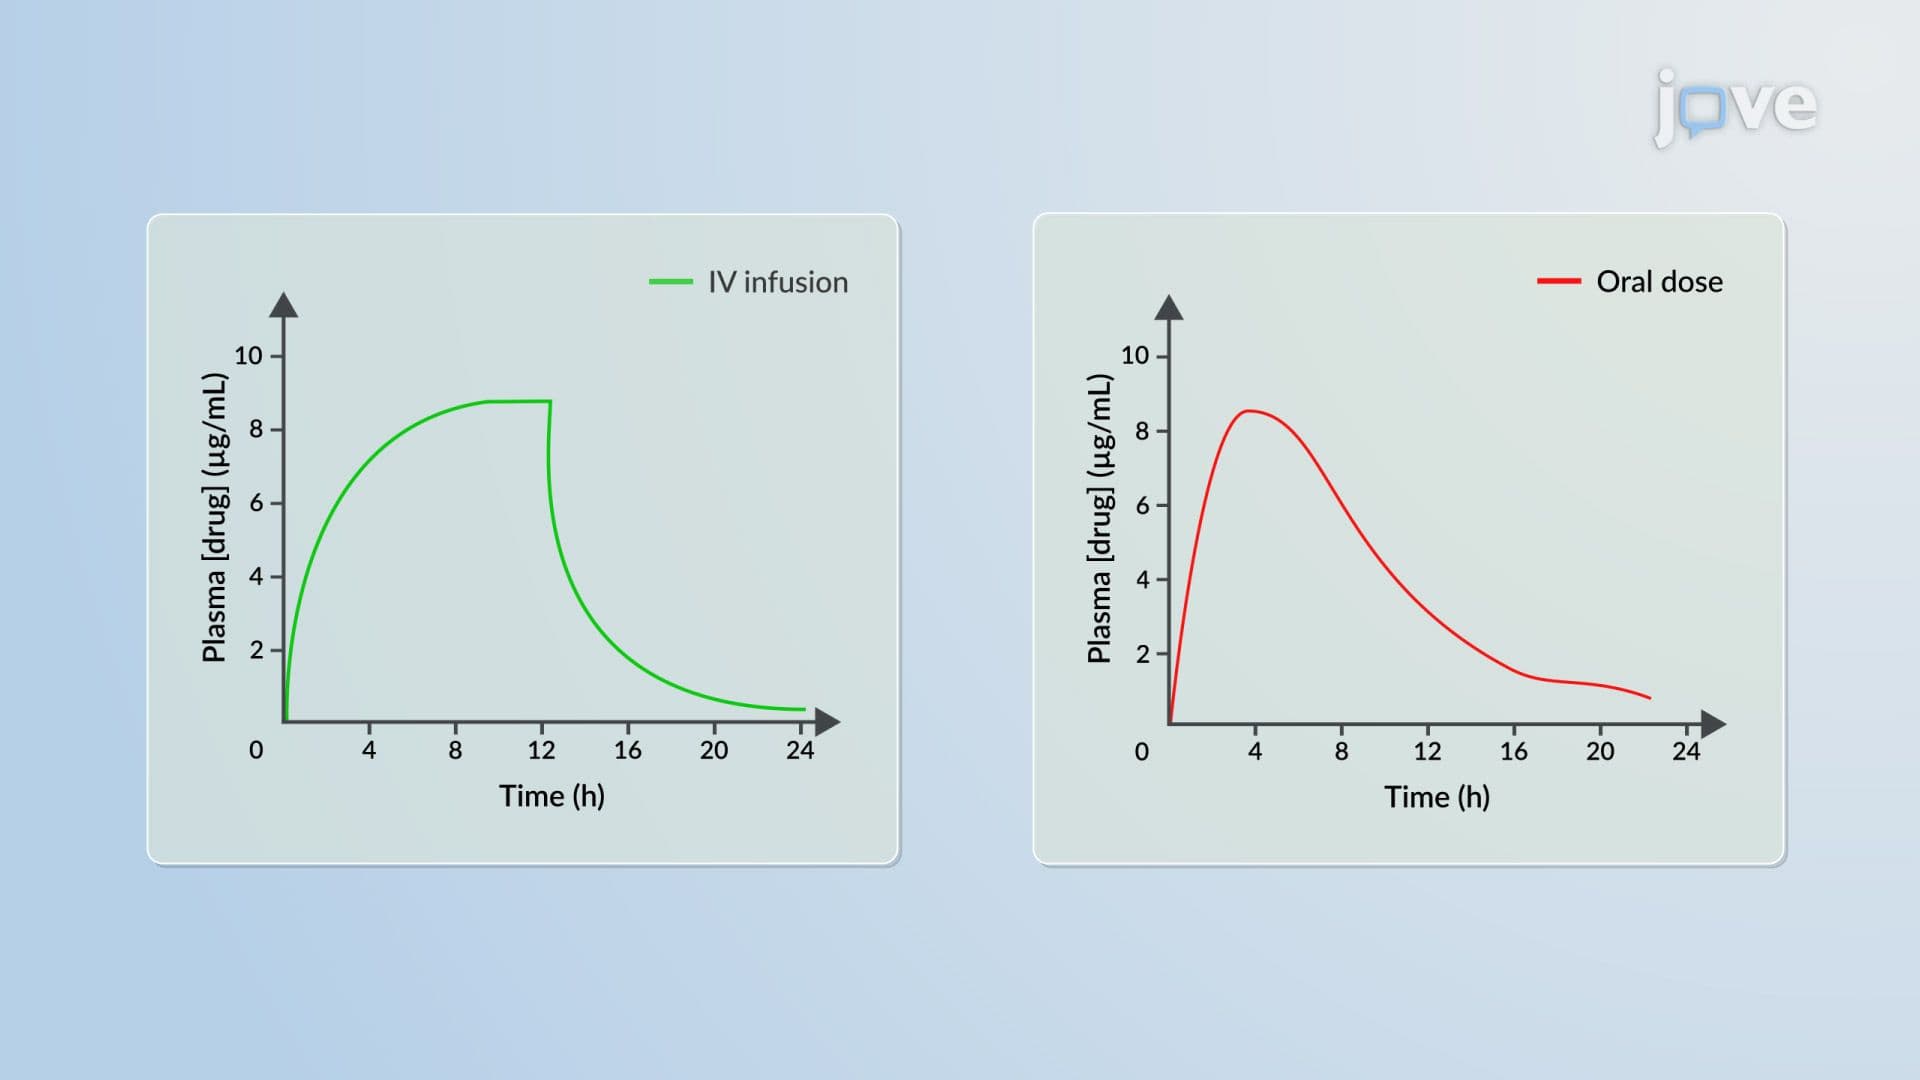
IV Infusion to Oral Dosing: Conversion Methods
 01:10
Retrovirus Life Cycles
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:29
Drug Dosing: Infants and Children
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism