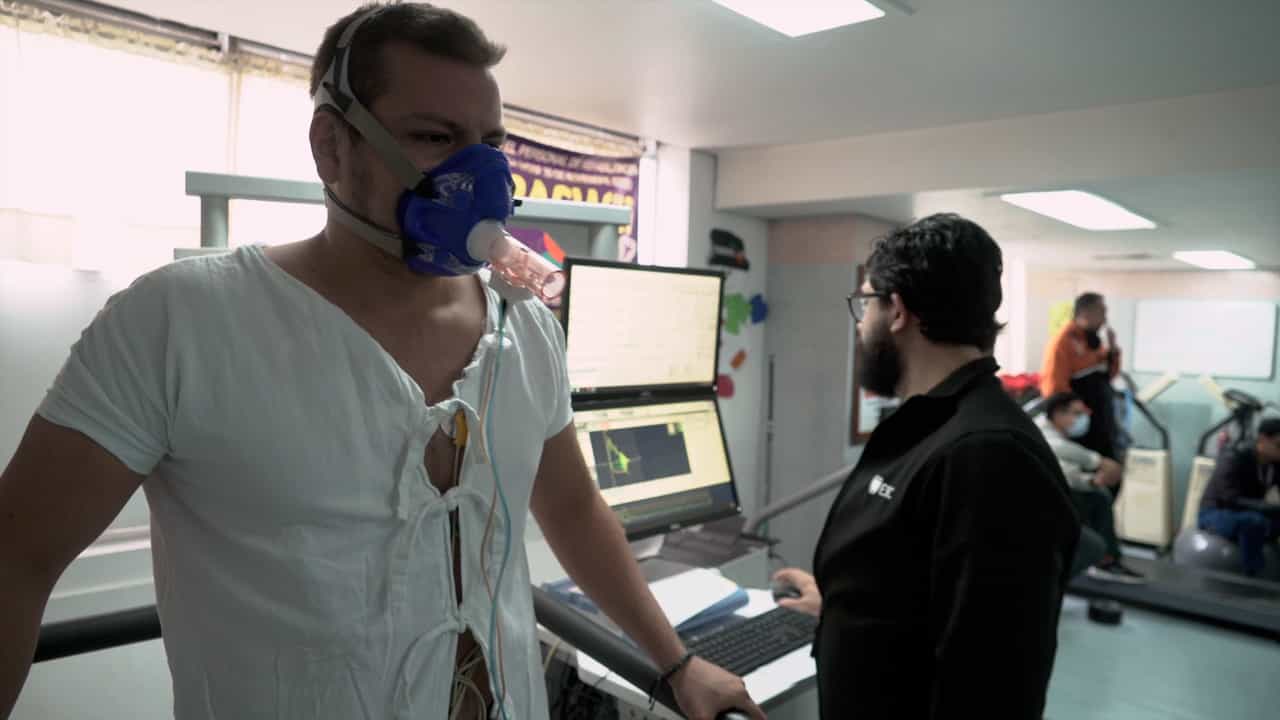

Three independent biological mechanisms cause exercise-associated hyponatremia: evidence from 2,135 weighed
T D Noakes1, K Sharwood, D Speedy
1University of Cape Town/Medical Research Council Research Unit for Exercise Science and Sports Medicine, Department of Human Biology, University of Cape Town/Sports Science Institute of South Africa, Newlands, 7700, South Africa. tdnoakes@sports.uct.ac.za

Abstract:
To evaluate the role of fluid and Na+ balance in the development of exercise-associated hyponatremia (EAH), changes in serum Na+ concentrations ([Na+]) and in body weight were analyzed in 2,135 athletes in endurance events. Eighty-nine percent of athletes completed these events either euhydrated (39%) or with weight loss (50%) and with normal (80%) or elevated (13%) serum [Na+]. Of 231 (11%) athletes who gained weight during exercise, 70% were normonatremic or hypernatremic, 19% had a serum [Na+] between 129-135 mmol/liter, and 11% a serum [Na+] of <129 mmol/liter. Serum [Na+] after racing was a linear function with a negative slope of the body weight change during exercise. The final serum [Na+] in a subset of 18 subjects was predicted from the amount of Na+ that remained osmotically inactive at the completion of the trial. Weight gain consequent to excessive fluid consumption was the principal cause of a reduced serum [Na+] after exercise, yet most (70%) subjects who gained weight maintained or increased serum [Na+], requiring the addition of significant amounts of Na+ (>500 mmol) into an expanded volume of total body water. This Na+ likely originated from osmotically inactive, exchangeable stores. Thus, EAH occurs in athletes who (i) drink to excess during exercise, (ii) retain excess fluid because of inadequate suppression of antidiuretic hormone secretion, and (iii) osmotically inactivate circulating Na+ or fail to mobilize osmotically inactive sodium from internal stores. EAH can be prevented by insuring that athletes do not drink to excess during exercise, which has been known since 1985.

Related Concept Videos
 01:25
Regulation of Water Intake
 01:20
Physiology of the Genitourinary System III: Urine Concentration and Dilution
 01:17
Hormonal Regulation of Blood Pressure
Epinephrine and Norepinephrine
The adrenal medulla releases epinephrine and norepinephrine, catecholamines that enhance and extend the sympathetic or "fight or flight" physiological response. These hormones escalate heart rate and the force of contraction while...
 01:26
Regulation of Sodium and Potassium
Sodium Regulation
Sodium ions make up approximately 90% of extracellular cations, with a normal blood plasma concentration of 136–148 mEq/L. A decrease in blood volume and pressure triggers the release of renin from granular cells in the juxtaglomerular complex (JGC), primarily in...
 01:25
Primary Motives: Hunger and Thirst
Hunger arises when the brain detects changes in the body's nutrient levels, including glucose, lipids, amino acids, and hormones such as ghrelin and leptin. The hypothalamus plays a central role in hunger regulation. The lateral hypothalamus acts...
 01:23
Formation of Concentrated Urine