Related Experiment Video
Updated: May 5, 2026
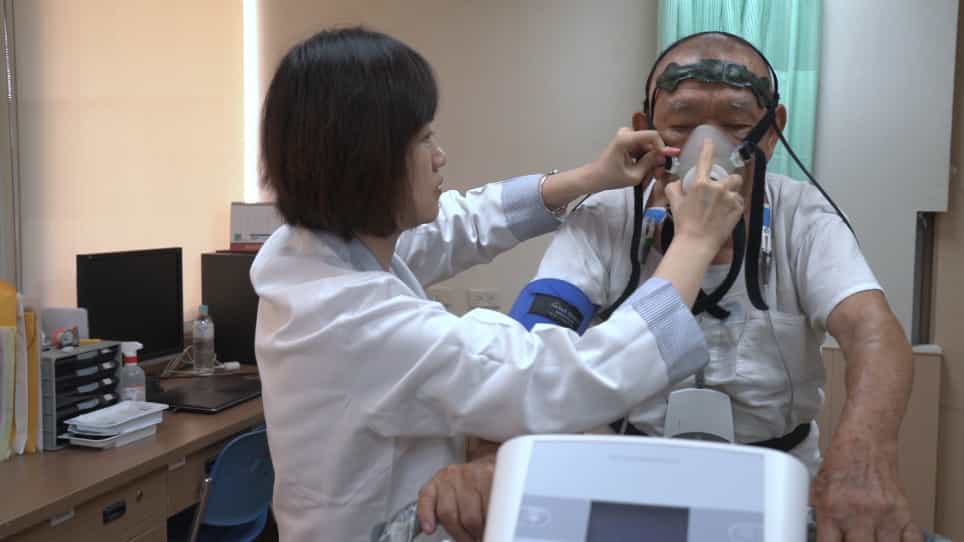

Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Sleep and exertional periodic breathing in chronic heart failure: prognostic importance and interdependence
Ugo Corrà1, Massimo Pistono, Alessandro Mezzani
1Divisione di Cardiologia, Salvatore Maugeri Foundation, IRCCS, Veruno, Italy. ucorra@fsm.it

Background:
Sleep and exertional periodic breathing are proverbial in chronic heart failure (CHF), and each alone indicates poor prognosis. Whether these conditions are associated and whether excess risk may be attributed to respiratory disorders in general, rather than specifically during sleep or exercise, is unknown.
Methods And Results:
We studied 133 CHF patients with left ventricular ejection fraction (LVEF) < or =40%. During 1170+/-631 days of follow-up, 31 patients (23%) died. Nonsurvivors had higher New York Heart Association class, ventilatory response (ve/vco2 slope), and apnea-hypopnea index (AHI) and lower peak vo2 (all P<0.01); lower LVEF and prescription of beta-blockers, and shorter transmitral deceleration time (all P<0.05). Exertional oscillatory ventilation (EOV), established by cyclic fluctuations in minute ventilation that persisted for > or =60% of exercise duration with an amplitude > or =15% of the average resting value, was significantly more frequent in nonsurvivors (42% versus 15%, P<0.01). Multivariable analysis selected AHI (hazard ratio [HR] 5.66, 95% CI 2.3 to 19.9, P<0.01), peak vo2 (HR 0.93, 95% CI 0.90 to 0.97, P<0.01), and beta-blocker prescription (HR 0.34, 95% CI 0.13 to 0.87, P<0.05) as predictors of cardiac events. The best cutoff for AHI was >30/h. EOV was significantly related to AHI >30/h (chi2 14.6, P<0.01): 78% of EOV patients showed AHI >30/h. Multivariable analysis, including breathing disorders alone (EOV, AHI >30/h) or in combination (EOV plus AHI >30/h), selected combined disorders as the strongest predictor of events (HR 6.65, 95% CI 2.6 to 17.1, P<0.01).
Conclusions:
In CHF, EOV is significantly associated with AHI >30/h. Although each breathing disorder alone is linked to total mortality, their combination has a crucial prognostic burden.
More Related Videos

Related Concept Videos
 01:26
Respiratory Volumes and Capacities I
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...
 01:23
Acute Respiratory Failure-IV
 01:22
Heart Failure VI: Adjunct Therapies