Related Experiment Video
Updated: Aug 7, 2026

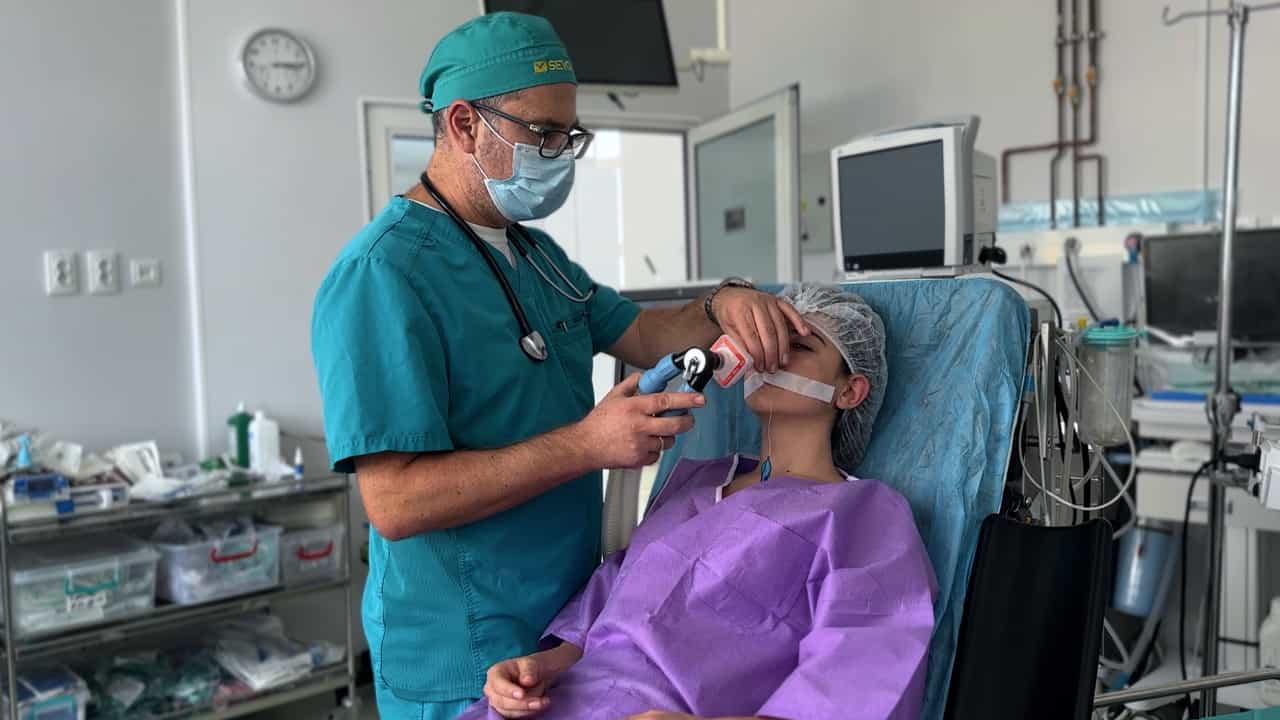
A Novel Rescue Technique for Difficult Intubation and Difficult Ventilation
Published on: January 17, 2011
The intubating laryngeal mask airway Fastrach for emergence after carotid endarterectomy
G S Voyagis1, V Dimitriou, J Brimacombe
1Department of Anaesthesia, Gennimatas & Sotiria Hospitals, Athens, Greece.

Abstract:
We determine the feasibility of using the intubating laryngeal mask airway Fastrach (ILM) as a ventilatory device during emergence from anesthesia after use as an airway intubator in patients undergoing carotid endarterectomy. Thirty-five patients (ASA 2-3, 53-84 yr) were studied. Induction was with midazolam/fentanyl/etomidate and maintenance was with sevoflurane 1-2% in O2 33-50% and N2O. Neuromuscular blockade was with cisatracurium. Tracheal intubation was with a flexible lightwand via the ILM. After successful intubation, the ILM remained in the pharynx, but with the cuff deflated. After surgery, but before anesthesia was discontinued, baseline cardiovascular variables were recorded. The ILM cuff was then reinflated, the tracheal tube removed, the anesthesia breathing system connected to the ILM and anesthesia discontinued. Any changes in the cardiovascular variables greater than +/- 20% baseline values were noted from cuff reinflation to 1 minute after ILM removal. Any adverse respiratory (laryngospasm, coughing, gagging, stridor, SpO2 <94%, end-tidal carbon dioxide >45 mmHg, regurgitation/aspiration) or electrocardiographic (ST segment or rhythm changes) events were also noted. Patients were questioned about postoperative sore throat at 2 and 24 hr. ILM insertion and intubation through the ILM were successful in all patients. Adequate ventilation was achieved in all patients before intubation and after extubation. The mean (range) time taken from cuff reinflation to ILM removal was 9 (5-21) min. The rate pressure product remained within +/- 20% baseline values in all patients. There were no adverse respiratory or electrocardiographic events. There were no adverse neurological events. The surgical field was satisfactory. Postoperative sore throat occurred in 14% at 2 hr and 0% at 24 hr. We conclude that the ILM can be used as a ventilatory device for emergence from anesthesia after use as an airway intubator for carotid endarterectomy.

Related Concept Videos
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques