Related Experiment Video
Updated: Aug 14, 2026
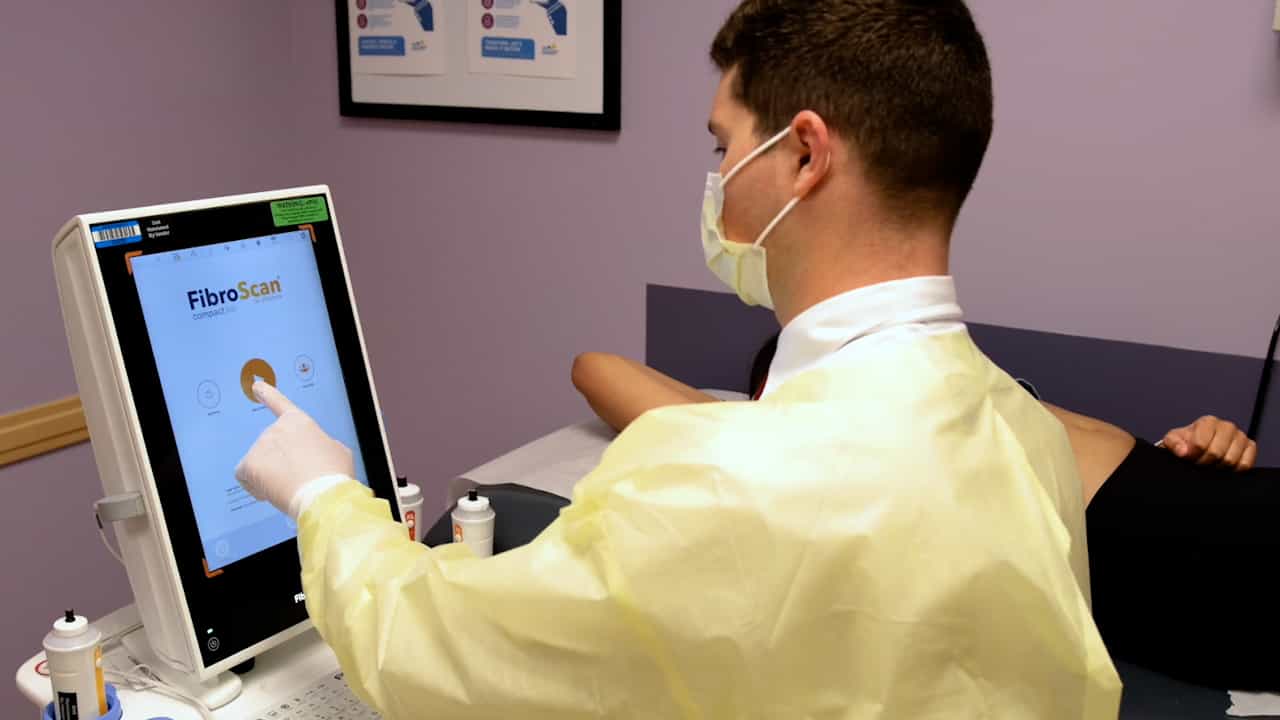

Implementation of Non-invasive Point of Care Transient Elastography for Evaluation of Liver Disease in Pediatric Populations with Cystic Fibrosis
Published on: August 29, 2025
National and regional analysis of exceptions to the Pediatric End-Stage Liver Disease scoring system (2003-2004)
Benjamin L Shneider1, Frederick J Suchy, Sukru Emre
1Department of Pediatrics, Mount Sinai School of Medicine, New York, NY 10029, USA. benjamin.shneider@mssm.edu

Insights
The Pediatric End Stage Liver Disease (PELD) score is not consistently used for pediatric liver transplant prioritization. Reassessment is needed to prevent deaths in children awaiting transplants.
Area of Science:
- Pediatric Hepatology
- Transplantation Medicine
- Health Services Research
Background:
- The Pediatric End Stage Liver Disease (PELD) scoring system was implemented in 2002 to prioritize children for liver transplantation.
- Accurate PELD score utilization is crucial for equitable organ allocation in pediatric liver transplant candidates.
Purpose of the Study:
- To evaluate the actual utilization of the PELD scoring system for pediatric liver transplant allocation between 2003 and 2004.
- To identify discrepancies and regional variations in PELD score application.
Main Methods:
- Analysis of the United Network for Organ Sharing (UNOS) database for pediatric liver transplants performed in 2003-2004.
- Assessment of PELD score usage, exceptions, and urgent listing criteria.
Main Results:
- The PELD score was not utilized in 53% of 682 pediatric liver transplants.
- Exceptions were made in 24% of cases, and 29% were listed as urgent without acute liver failure.
- Significant regional variability in PELD score utilization was observed, correlating with pediatric donor organ availability.
Conclusions:
- The current PELD scoring system demonstrates inconsistent application and potential underestimation of mortality risk.
- Urgent reassessment of the PELD system is necessary to improve liver allocation and reduce mortality in children awaiting transplants.
Abstract:
Since February 2002, the Pediatric End Stage Liver Disease (PELD) scoring system has been utilized as a means of prioritizing children for liver transplantation. The United Network for Organ Sharing database was queried to assess utilization of PELD in 2003 and 2004; 682 liver transplants were performed in pediatric recipients where the PELD score was potentially the primary determinant of liver allocation. In the majority of circumstances (53%) the actual calculated PELD score was not utilized to determine liver allocation. An exception to the PELD score was utilized in 24% of cases. An additional 29% of the children were listed as urgent (status 1) without having acute liver failure. There was considerable regional variability in the inability to utilize actual PELD scores for liver allocation to children. PELD utilization was higher in regions of the country where pediatric donor organs were more available, presumably because children have some priority for organs from pediatric donors. There were 87 deaths in children awaiting liver transplantation. The mean PELD score in children without acute liver failure or metabolic liver disease (n = 33) near the time of death was 24.2, which has a purported 3-month risk of mortality of less than 10%. In our opinion the assigned 3-month risk of mortality associated with PELD scores is understated. Three-month mortality risk is used to inter-convert the adult and pediatric scoring systems. Therefore exceptions to the scoring system are required when children compete with adults for donor organs. In conclusion, urgent reassessment of the PELD scoring system is needed to avoid morbidity and mortality in children.