Related Experiment Video
Updated: Jul 21, 2026


Tissue Engineering: Construction of a Multicellular 3D Scaffold for the Delivery of Layered Cell Sheets
Published on: October 3, 2014
Structural remodeling of cardiac myocytes in patients with ischemic cardiomyopathy
A M Gerdes1, S E Kellerman, J A Moore
1Department of Anatomy, University of South Florida, College of Medicine, Tampa 33612.

Insights
In ischemic cardiomyopathy (ICM), heart chamber dilation is primarily caused by cardiac myocytes increasing in length, not slippage. This change in myocyte shape contributes to increased heart wall stress.
Area of Science:
- Cardiovascular Biology
- Cardiac Remodeling
- Heart Failure Pathophysiology
Background:
- Chronic ischemic heart disease can cause ventricular dilation and congestive heart failure, a condition known as ischemic cardiomyopathy (ICM).
- The specific alterations in cardiac myocyte shape contributing to this ventricular dilation in ICM have not been previously understood.
Purpose of the Study:
- To investigate the changes in cardiac myocyte dimensions and shape within the context of ischemic cardiomyopathy.
- To determine whether intracellular changes (myocyte lengthening) or extracellular changes (myocyte slippage) are responsible for chamber dilation in ICM.
Main Methods:
- Isolated left ventricular myocytes were obtained from explanted human hearts of patients with ICM and from nonfailing donor hearts with normal coronary arteries (NCA).
- Myocyte dimensions, including length and width, were quantitatively assessed and compared between the ICM and NCA groups.
Main Results:
- Myocytes from ICM hearts were significantly longer (40% increase) and had a greater length/width ratio (49% increase) compared to myocytes from NCA hearts.
- No significant difference was observed in myocyte width or sarcomere length between the two groups.
- The observed increase in myocyte length closely mirrors the documented increase in end-diastolic diameter in patients with ICM.
Conclusions:
- Increased myocyte length, an intracellular alteration, is the primary driver of chamber dilation in ischemic cardiomyopathy.
- Maladaptive remodeling of myocyte shape, specifically increased length-to-width ratio, may exacerbate elevated cardiac wall stress in ICM.
Background:
Chronic ischemic heart disease may lead to ventricular dilation and congestive heart failure (ischemic cardiomyopathy [ICM]). The changes in cardiac myocyte shape associated with this dilation, however, are not known.
Methods And Results:
Left ventricular myocyte dimensions were assessed in cells isolated from explanted human hearts obtained from patients with ICM (n = 6) who were undergoing heart transplantation. Cells were also examined from three nonfailing donor hearts with normal coronary arteries (NCA). Compared with cells from patients with NCA, myocyte length was 40% longer in hearts from patients with ICM (197 +/- 8 versus 141 +/- 9 microns, p less than 0.01), cell width was not significantly different, and cell length/width ratio was 49% greater (11.2 +/- 0.9 versus 7.5 +/- 0.6, p less than 0.01). Sarcomere length was the same in myocytes from both groups. The extent of myocyte lengthening is comparable to the increase in end-diastolic diameter commonly reported in patients with ICM.
Conclusions:
These data suggest that increased myocyte length (an intracellular event), instead of myocyte slippage (an extracellular event), is largely responsible for the chamber dilation in ICM. Furthermore, maladaptive remodeling of myocyte shape (e.g., increased myocyte length/width ratio) may contribute to the elevated wall stress (e.g., increased chamber radius/wall thickness) in ICM.
Related Concept Videos
 01:13
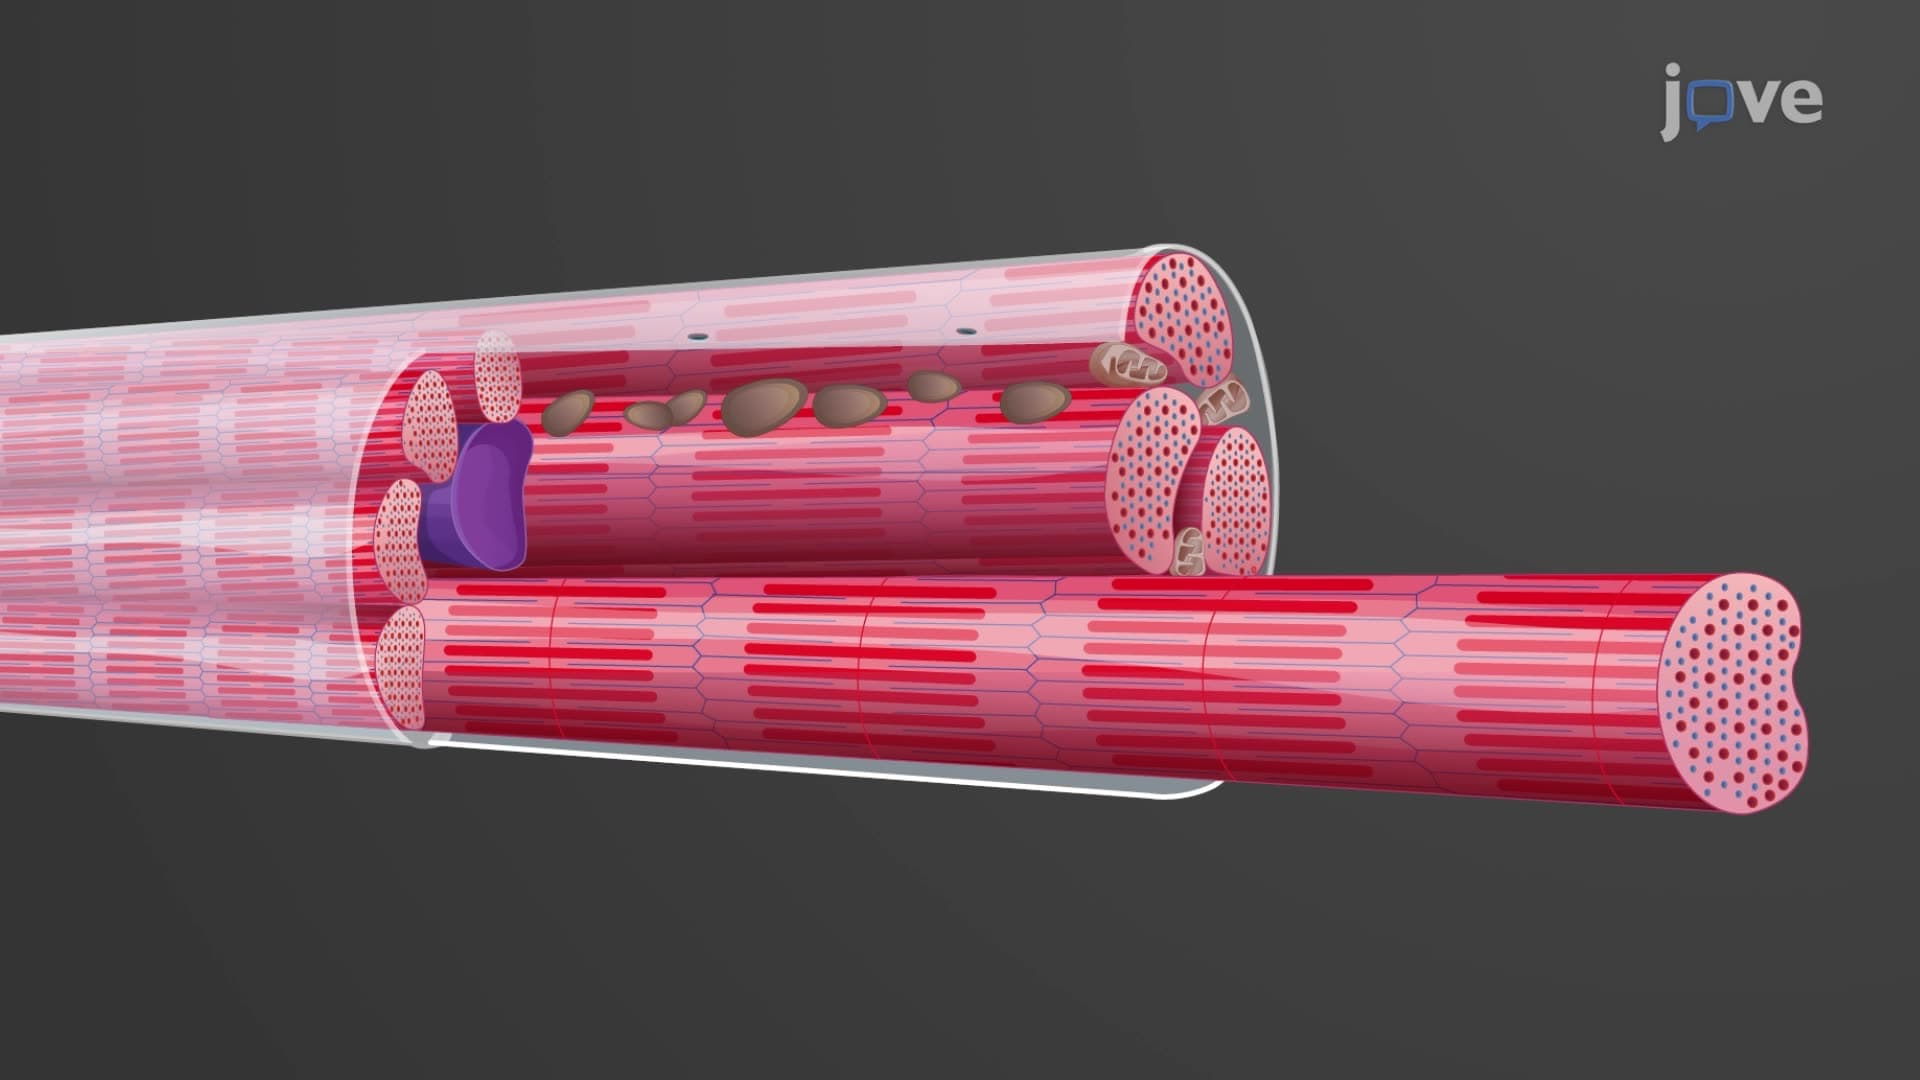
Structure of Cardiac Muscles
Compared to skeletal muscles, cardiac muscle cells are small and mostly have a single nucleus. Additionally, they are usually...
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:21
Myocarditis I: Introduction
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy V: Interprofessional Care
 01:29
Cardiomyopathy VI: Nursing Management