Related Experiment Video
Updated: Aug 13, 2026

Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Vertebral fractures in late adolescence: a 27 to 47-year follow-up
Anders Moller1, Ralph Hasserius, Jack Besjakov
1Department of Orthopaedics, Malmo University Hospital, Malmo, Sweden. ta.moller@spray.se

Abstract:
The long-term outcome of thoracic and lumbar fractures in late adolescence is sparsely described and it is unclear whether a fractured vertebral body in these years, as in young children, can be resituated in height. The purpose of this study was to in late adolescence determine the incidence, the long-term outcome and the modelling capacity in fractures of the thoracic and lumbar region. The incidence of vertebral fractures 1950-1971 in individuals aged 16-18 years was through the radiological archives evaluated in a city cohort of 228,878 citizens, of whom 13,893 were aged 16-18. A follow-up, 27-47 years after the injury, including subjective, objective and radiological evaluation was conducted in 18 boys and 5 girls. Twenty-nine boys and 11 girls were registered with a thoracic or lumbar vertebral fracture during the study period conferring an annual incidence of 0.14 per thousand. Of the 23 individuals that attended the follow-up, 14 had one-column compression fractures, one a Denis type A, six a Denis type B, one a Denis type D and one a Chance fracture. At injury, one had a partial paresis in one leg and one developed a transient paraparesis during the first week. All were treated non-operatively. At follow-up, 18 individuals had no complaints while 5 had occasional back pain, 20 were classified as Frankel E and 3 as Frankel D. The radiographic ratio of anterior height to posterior height of the fractured vertebral body was unchanged during the study period. Thoracic and lumbar vertebral fractures in late adolescence with no or minor neurological deficits have a predominantly favourable long-term outcome, even if no modelling capacity of the fractured vertebral body remains in late adolescence.
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:16
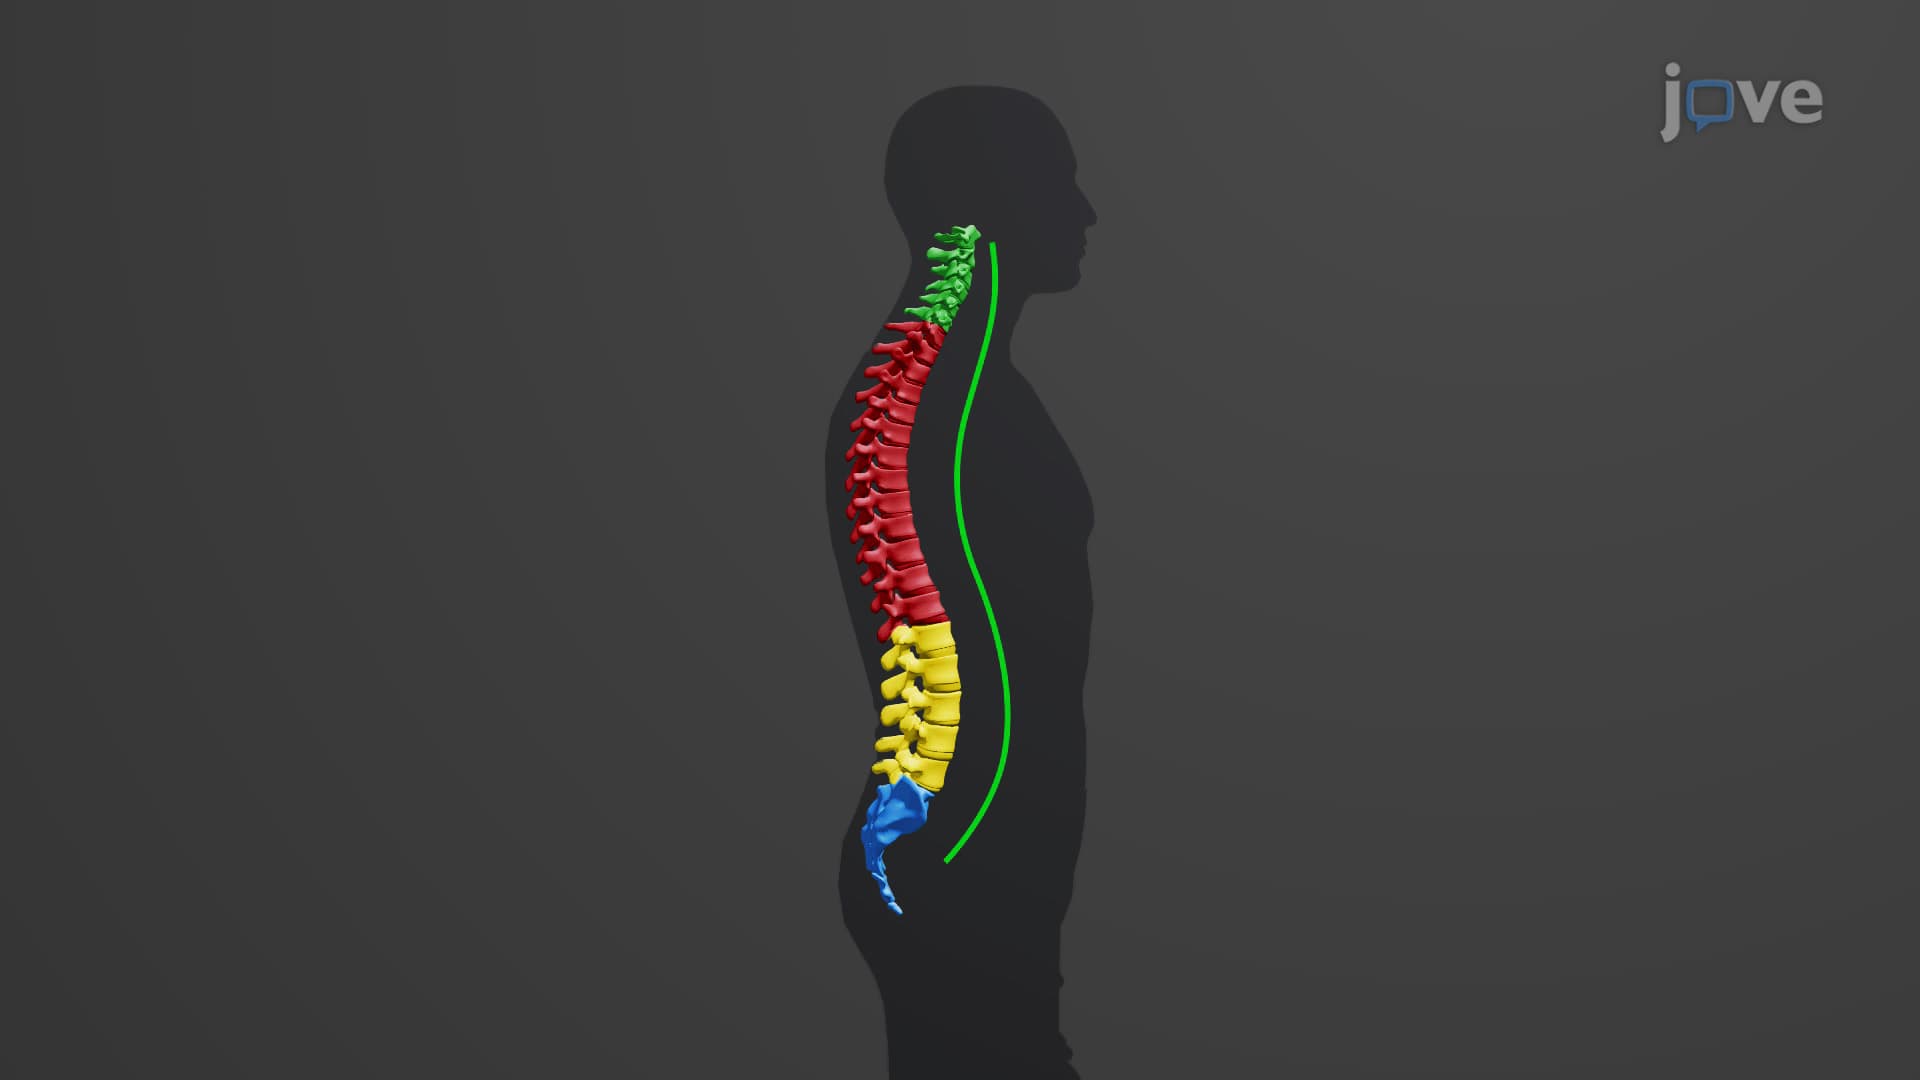
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...