Related Experiment Video
Updated: Aug 14, 2026


A Convenient Method for Extraction and Analysis with High-Pressure Liquid Chromatography of Catecholamine Neurotransmitters and Their Metabolites
Published on: March 1, 2018
Levels of catecholamine in plasma and cerebrospinal fluid in aneurysmal subarachnoid hemorrhage
A Dilraj1, J H Botha, V Rambiritch
1Department of Pharmacology, University of Durban-Westville, South Africa.

Despite intensive investigation into the cause of cerebral vasospasm (focal ischemic deficit) after subarachnoid hemorrhage, the morbidity and mortality associated with this condition remain high. Various studies have shown levels of catecholamine in plasma and cerebrospinal fluid (CSF) to be increased in subarachnoid hemorrhage, and it is possible that these vasoactive substances play an important role in the subsequent vasospasm. In an attempt to elucidate this possibility, the study presented here was undertaken to investigate the relationship between catecholamine levels in plasma and CSF and focal ischemic deficit (FID); the rupture of aneurysms on blood vessels supplying the hypothalamus as compared with the rupture of aneurysms on blood vessels supplying other areas of the brain; and the clinical outcome of the patients. Concentrations of adrenaline and noradrenaline in plasma and CSF samples obtained from 21 patients who had suffered aneurysmal subarachnoid hemorrhage were determined by a radioenzymatic technique. Significantly higher levels of adrenaline were found at the time of surgery in the CSF of patients with FID. A similar trend, though not statistically significant, was also observed for plasma. Patients with a rupture of aneurysms on blood vessels supplying the hypothalamus showed a tendency towards higher catecholamine levels in plasma and CSF. Subjects with a bad clinical outcome (i.e., those who were severely disabled or had died) had significantly higher levels of catecholamine in plasma than did those with a good clinical outcome (i.e., those with moderate or no disability). Further detailed analysis of the interrelationships showed that, within the group of patients with FID, those with rupture of aneurysms on blood vessels supplying the hypothalamus had significantly higher catecholamine levels in plasma than did those with rupture of aneurysms on other cerebral vessels. Furthermore, in the group of patients with rupture of aneurysms on blood vessels supplying the hypothalamus, those with a bad clinical outcome had significantly higher catecholamine levels in plasma than did those with a good clinical outcome. These findings lend support to the possibility that damage to the hypothalamus and subsequent elevations in catecholamine levels may be associated with FID and poor clinical outcome.
Despite intensive investigation into the cause of cerebral vasospasm (focal ischemic deficit) after subarachnoid hemorrhage, the morbidity and mortality associated with this condition remain high. Various studies have shown levels of catecholamine in plasma and cerebrospinal fluid (CSF) to be increased in subarachnoid hemorrhage, and it is possible that these vasoactive substances play an important role in the subsequent vasospasm. In an attempt to elucidate this possibility, the study presented here was undertaken to investigate the relationship between catecholamine levels in plasma and CSF and focal ischemic deficit (FID); the rupture of aneurysms on blood vessels supplying the hypothalamus as compared with the rupture of aneurysms on blood vessels supplying other areas of the brain; and the clinical outcome of the patients. Concentrations of adrenaline and noradrenaline in plasma and CSF samples obtained from 21 patients who had suffered aneurysmal subarachnoid hemorrhage were determined by a radioenzymatic technique. Significantly higher levels of adrenaline were found at the time of surgery in the CSF of patients with FID. A similar trend, though not statistically significant, was also observed for plasma. Patients with a rupture of aneurysms on blood vessels supplying the hypothalamus showed a tendency towards higher catecholamine levels in plasma and CSF. Subjects with a bad clinical outcome (i.e., those who were severely disabled or had died) had significantly higher levels of catecholamine in plasma than did those with a good clinical outcome (i.e., those with moderate or no disability). Further detailed analysis of the interrelationships showed that, within the group of patients with FID, those with rupture of aneurysms on blood vessels supplying the hypothalamus had significantly higher catecholamine levels in plasma than did those with rupture of aneurysms on other cerebral vessels. Furthermore, in the group of patients with rupture of aneurysms on blood vessels supplying the hypothalamus, those with a bad clinical outcome had significantly higher catecholamine levels in plasma than did those with a good clinical outcome. These findings lend support to the possibility that damage to the hypothalamus and subsequent elevations in catecholamine levels may be associated with FID and poor clinical outcome.


Related Concept Videos
 01:21
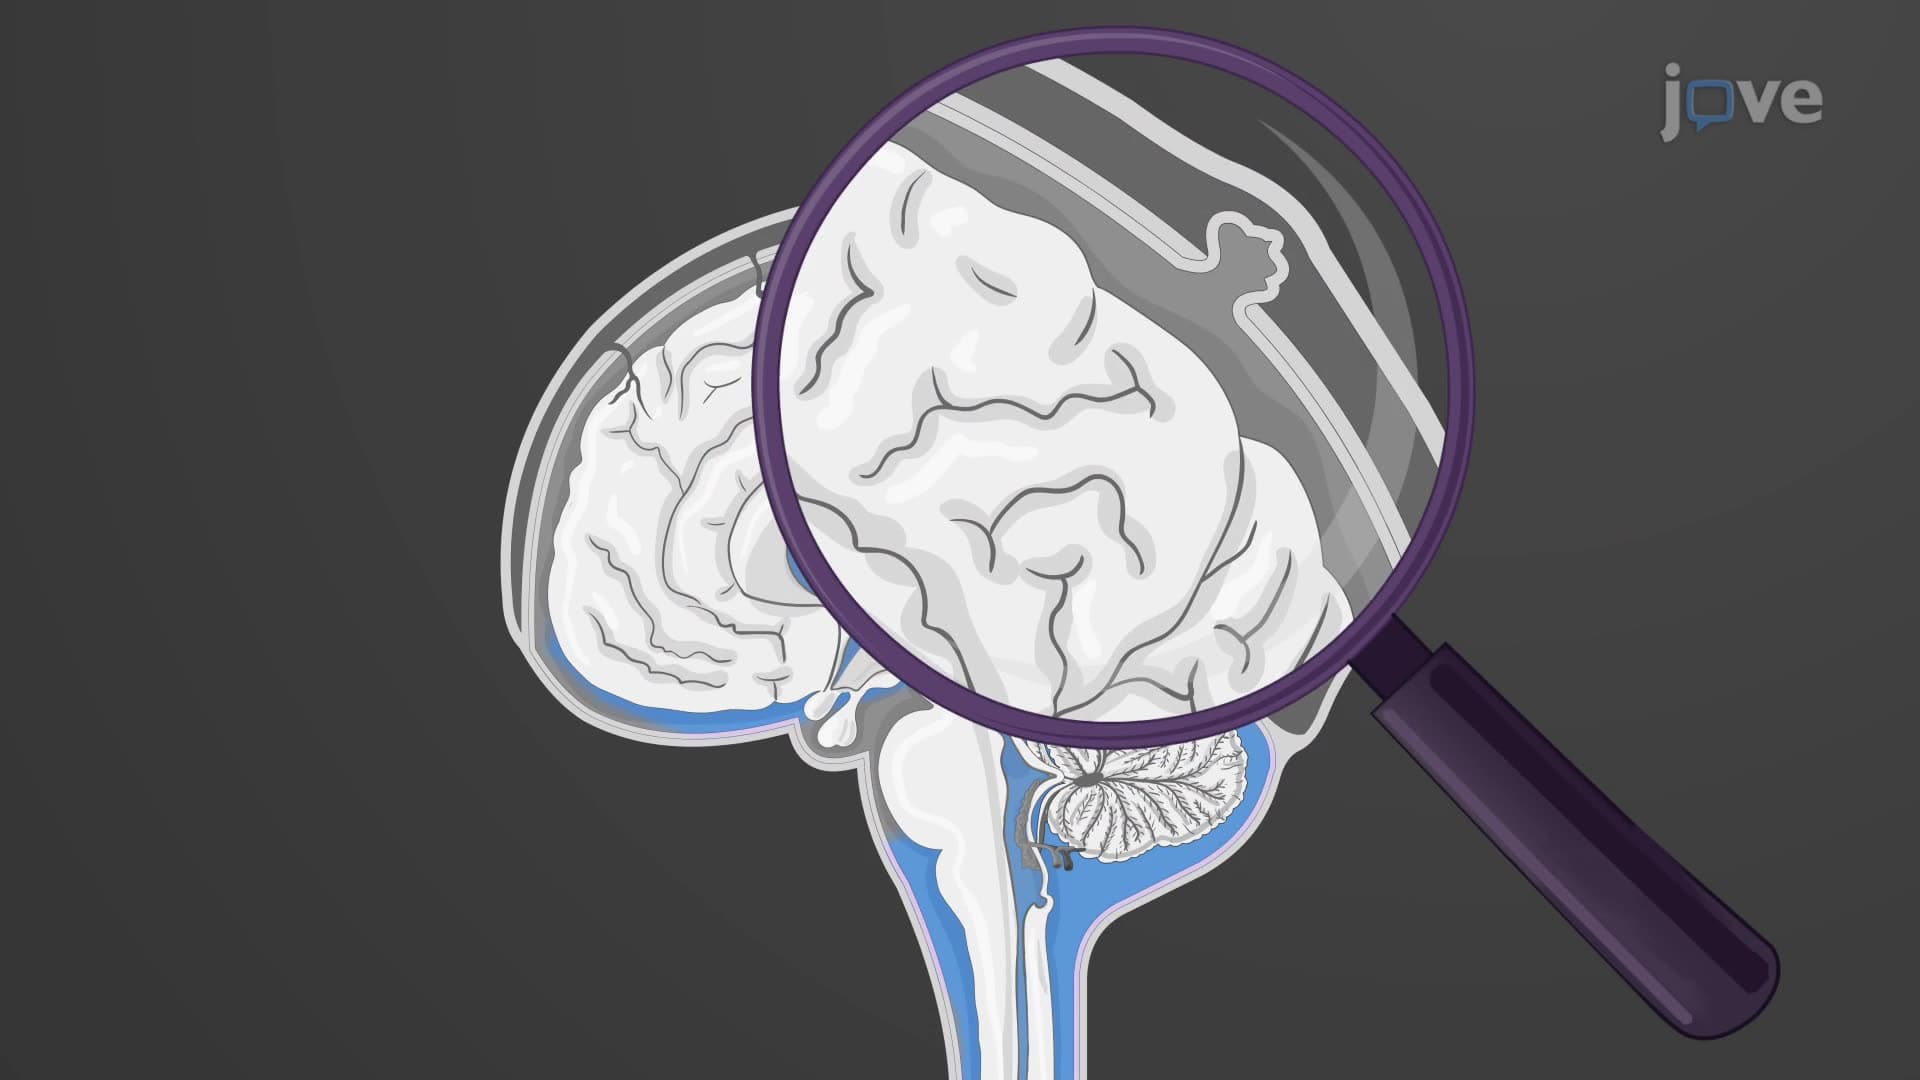
Cerebrospinal Fluid
CSF Production
CSF is produced mainly in the choroid plexus, a network of capillaries and ependymal cells located within the ventricular system of the brain.
 01:17
Hemorrhagic Stroke l: Introduction
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:14
Increased Intracranial Pressure l: Introduction
 01:19
Cerebral Edema l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology