Related Experiment Video
Updated: Aug 13, 2026

Application of Simplified Stent-bridging Pancreaticogastrostomy in Open Pancreaticoduodenectomy
Published on: March 17, 2026
Non-occlusive small bowel necrosis during enteral feeding after pancreaticoduodenectomy
K Thaler1, J Garreau, P D Hansen
1Department of Minimal Invasive Surgery, Legacy Health System, Oregon Health and Science University, Portland, Oreg, USA.

Background:
Early enteral tube feeding is widely used after major surgery and trauma. This article is intended to alert surgeons to the possibility of small bowel necrosis following enteral refeeding and to discuss etiology and clinical features.
Methods:
A case series from a single surgeon's database at a Tertiary Care Center is reported. Cases were drawnfrom a consecutive series of patients undergoing pylorus-preserving pancreaticoduodenectomy and placement of a needle catheter jejunostomy between January 1998 and June 2004.
Results:
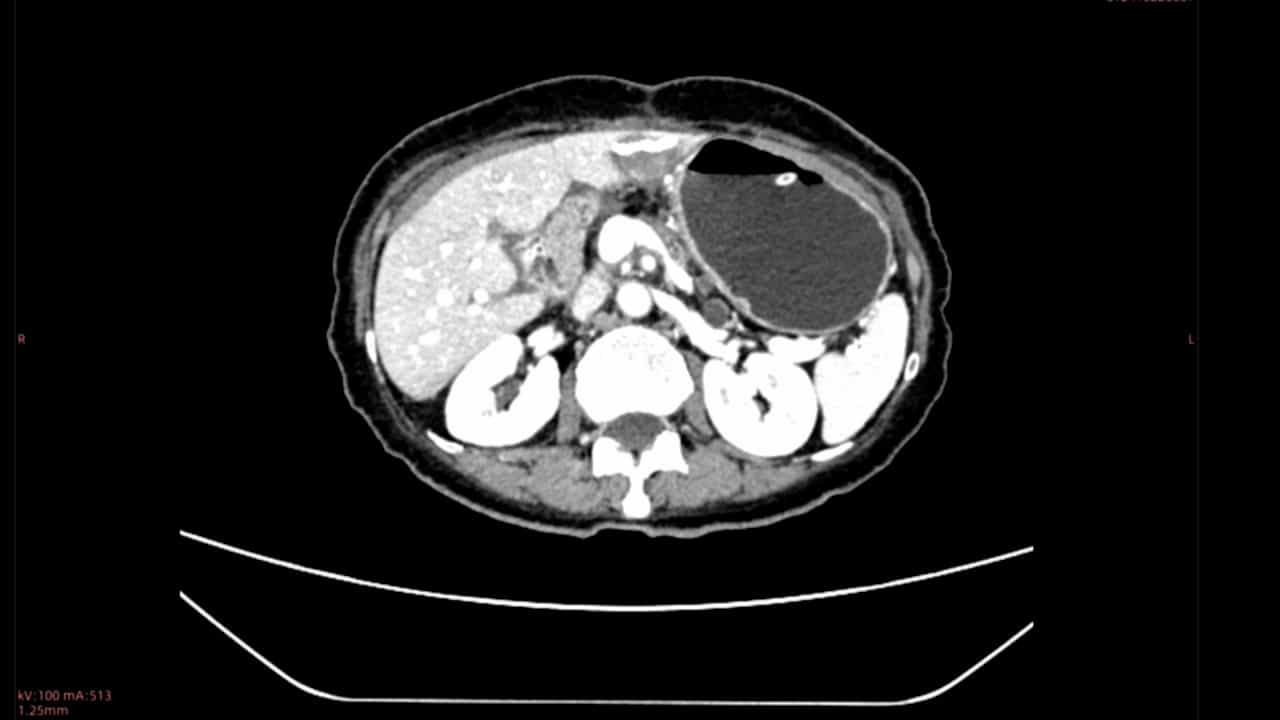
Two patients receiving early postoperative tube feeding developed sepsis with subsequent small bowel necrosis. Abdominal distension and signs of sepsis developed early postoperatively. Diagnosis was made based on characteristic computed tomography findings. Both patients underwent laparotomy with segmental bowel resection and survived.
Conclusion:
Non-specific septic symptoms associated with recurrent abdominal distension are ominous signs in patients receiving early postoperative enteral tube feeding and should prompt discontinuation of enteral nutrition. Within this scenario, CT imaging represents a valuable adjunct in the early assessment of these patients.
Related Concept Videos
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube through...
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:07
Intestinal Obstruction II: Pathophysiology