Related Experiment Video
Updated: Aug 13, 2026
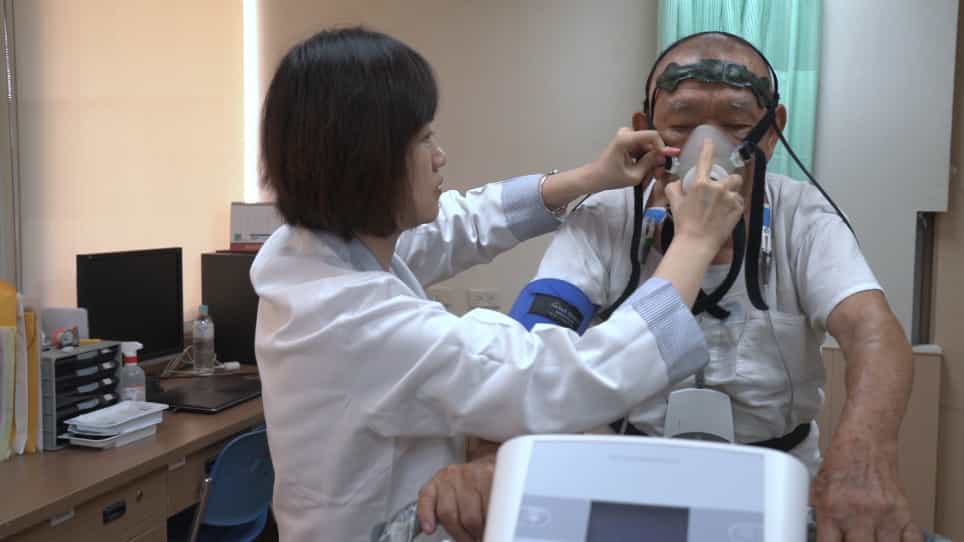

Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Cardiac output augmentation during hypoxemia improves cerebral metabolism after hypothermic cardiopulmonary bypass
Jess M Schultz1, Tara Karamlou, Irving Shen
1Division of Pediatric Cardiac Surgery, Doernbecher Children's Hospital, Oregon Health & Science University, Portland, Oregon 97239-3098, USA.

Background:
Hypothermic circulatory arrest (HCA) impairs cerebral oxygen delivery (CDO2) and cerebral oxygen consumption (CMRO2), which are further reduced by perioperative hypoxemia. This study investigates if continuous hypothermic low-flow cardiopulmonary bypass (HLF) or intermittent hypothermic low-flow cardiopulmonary bypass (IHLF) can prevent reductions in CDO2 and CMRO2 during hypoxemia.
Methods:
Eighteen neonatal piglets, cooled to 16 degrees to 18 degrees C with cardiopulmonary bypass (CPB), were randomly assigned into three groups: HCA, HLF (50 cc.kg(-1).min(-1)), or IHLF (1 minute of HLF for every 15 minutes of HCA). After 60 minutes of hypothermia, normothermic CPB (100 cc.kg(-1).min(-1)) was established and cerebral perfusion data measured at hyperoxemia (PaO2 150 to 250 mm Hg), hypoxemia (PaO2 50 to 60 mm Hg), and severe hypoxemia (PaO2 30 to 40 mm Hg), and with increased CPB flow (200 cc.kg(-1).min(-1)) during severe hypoxemia.
Results:
The CMRO2 (in mL O2.100 g(-1).min(-1)) was lower after HCA (2.5 +/- 0.3), compared with HLF (4.1 +/- 0.5, p = 0.02) and IHLF (6.2 +/- 0.8, p = 0.002). Within groups, the change from hyperoxemia to severe hypoxemia resulted in decreased CMRO2: HCA (1.3 +/- 0.2, p = 0.004), HLF (3.0 +/- 0.5, p = 0.01), and IHLF (2.9 +/- 0.5, p = 0.01). During severe hypoxemia, increasing CPB flow (from 100 cc.kg(-1).min(-1) to 200 cc.kg(-1).min(-1)) improved CMRO2: HCA (1.9 +/- 0.5, p = 0.05), HLF (4.2 +/- 0.5, p = 0.05), and IHLF (7.4 +/- 0.5, p = 0.04).
Conclusions:
Hypoxemia reduces CDO2 and CMRO2 despite the method of hypothermic CPB. Increased CPB flow during hypoxemia can restore both CDO2 and CMRO2 to values found with hyperoxemia and slower CPB flows. Augmenting cardiac output during periods of perioperative hypoxemia may prevent cerebral injury after exposure to hypothermic cardiopulmonary bypass.

Related Concept Videos
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be met...
 01:19
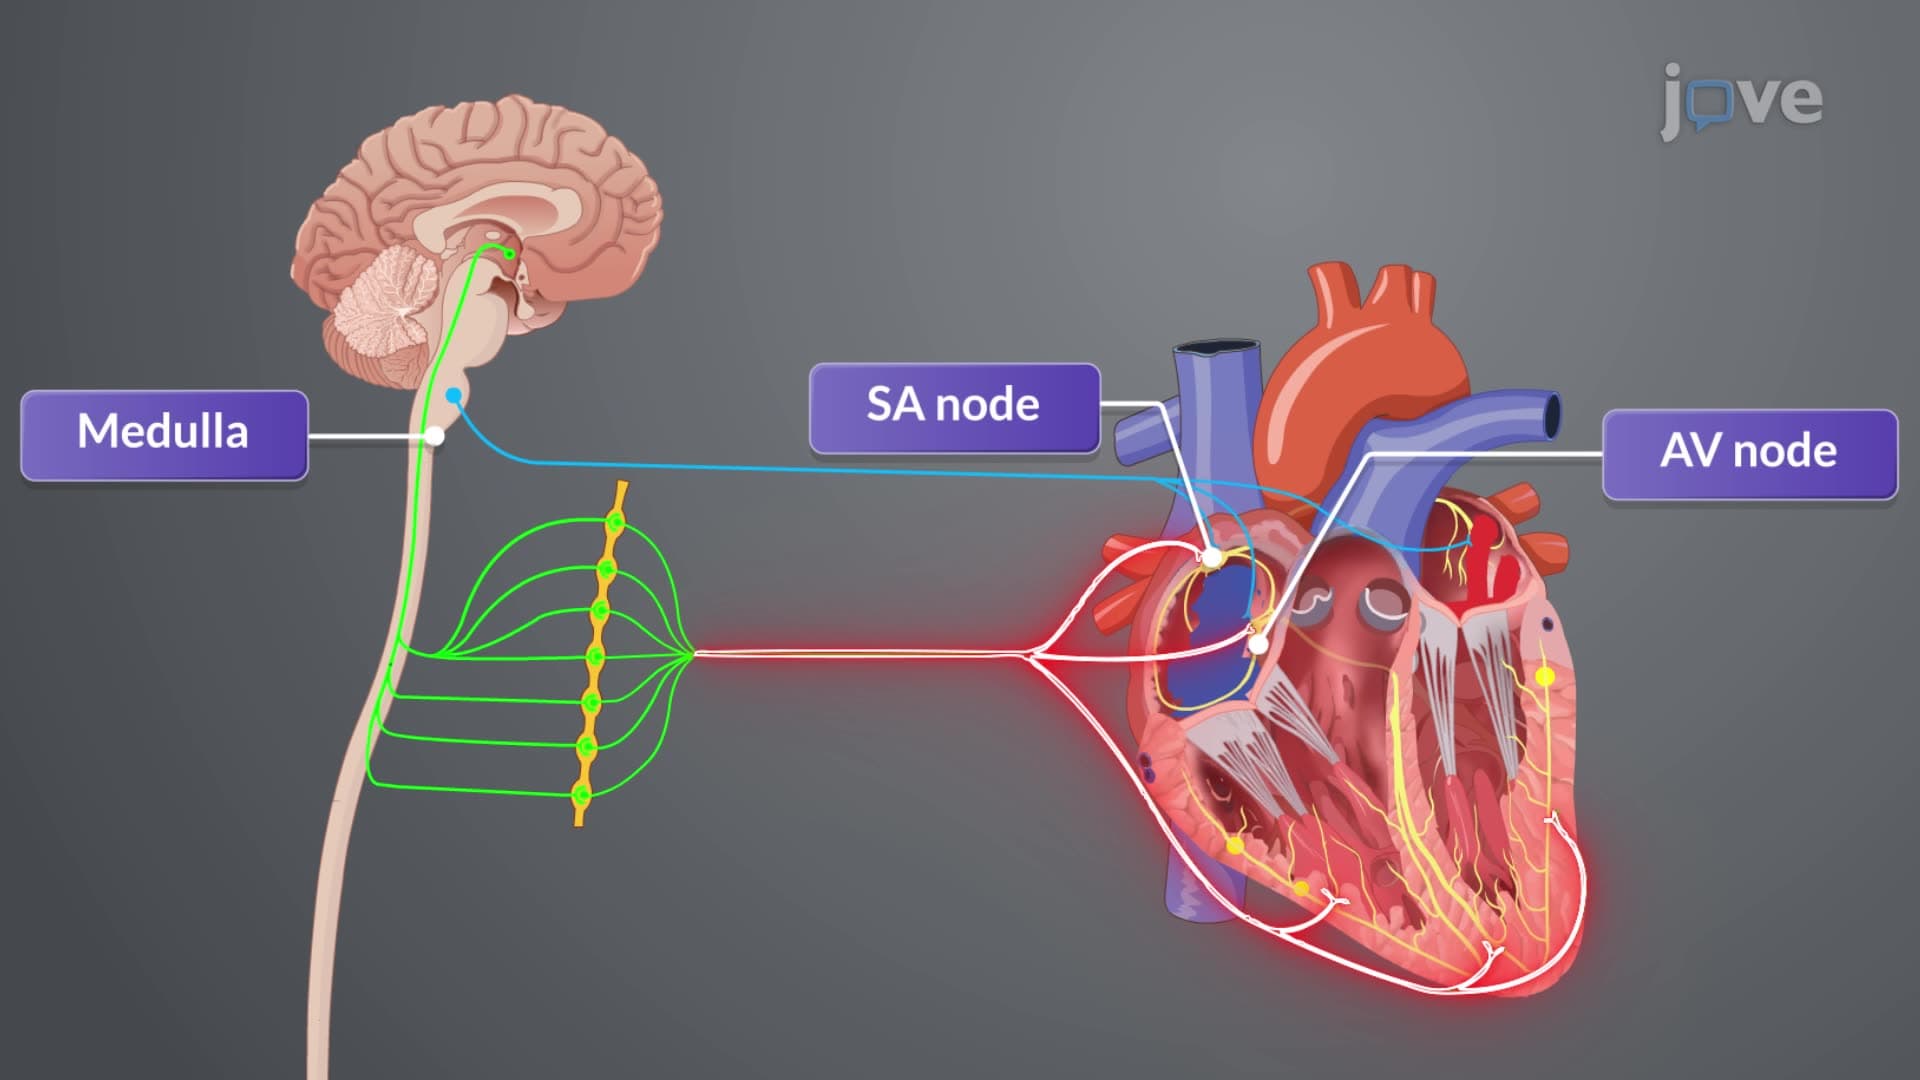
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart rate...
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical cardiac output averages...
 01:16
Treatment for Pulmonary Arterial Hypertension: Oxygen Therapy for Respiratory Failure
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue, improving...