Related Experiment Video
Updated: Aug 13, 2026
Oxygenation-sensitive Cardiac MRI with Vasoactive Breathing Maneuvers for the Non-invasive Assessment of Coronary Microvascular Dysfunction
Published on: August 17, 2022
Deterioration of body oxygen metabolism by vasodilator and/or vasoconstrictor administration during cardiopulmonary
Koichi Sato1, Masakazu Sogawa, Osamu Namura
1Division of Thoracic and Cardiovascular Surgery, Niigata University Graduate School of Medical and Dental Sciences, Asahimachi street 1-757, Niigata, Japan.

Abstract:
During cardiopulmonary bypass (CPB), tissue perfusion injury occurs even if perfusion pressure is maintained. Although a vasodilator and a vasoconstrictor are clinically administered if bypass flow is maintained, they may restore perfusion pressure without improving tissue perfusion. We evaluated the influence of vasodilators and vasoconstrictors on the whole body during CPB. Fifty-six patients with valvular disease who received moderately hypothermic CPB without blood transfusion were divided into four groups, depending upon whether a vasodilator and/or a vasoconstrictor was administered, and postoperative data were compared. Bypass flow and aortic pressure were maintained at 2.4 l/min/m and 5090 mm Hg. Body weight, dilution, hematocrit level, CPB, and aortic clamp duration, blood temperature, bypass flow, perfusion pressure, base excess levels during CPB, cardiac index, arterial and mixed venous oxygen pressure, and alveolar-arterial oxygen distribution after CPB were comparable among the four groups. However, the time to extubation was significantly longer. Blood lactate levels, measured for patients returned to the ward, were significantly higher in the agent-administered groups than in the no-agent group, whereas blood lactate levels on extubation and blood creatinine levels on postoperative day 1 were comparable among the groups. Vasodilator and/or vasoconstrictor administration during CPB may deteriorate the body oxygen metabolism, which might imply tissue perfusion and worsen the complications induced by hypoperfusion during CPB.


Related Concept Videos
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:27
Oxygen Transport in the Blood
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:16
Treatment for Pulmonary Arterial Hypertension: Oxygen Therapy for Respiratory Failure
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue, improving...
 01:20
Respiration and Gaseous Exchange
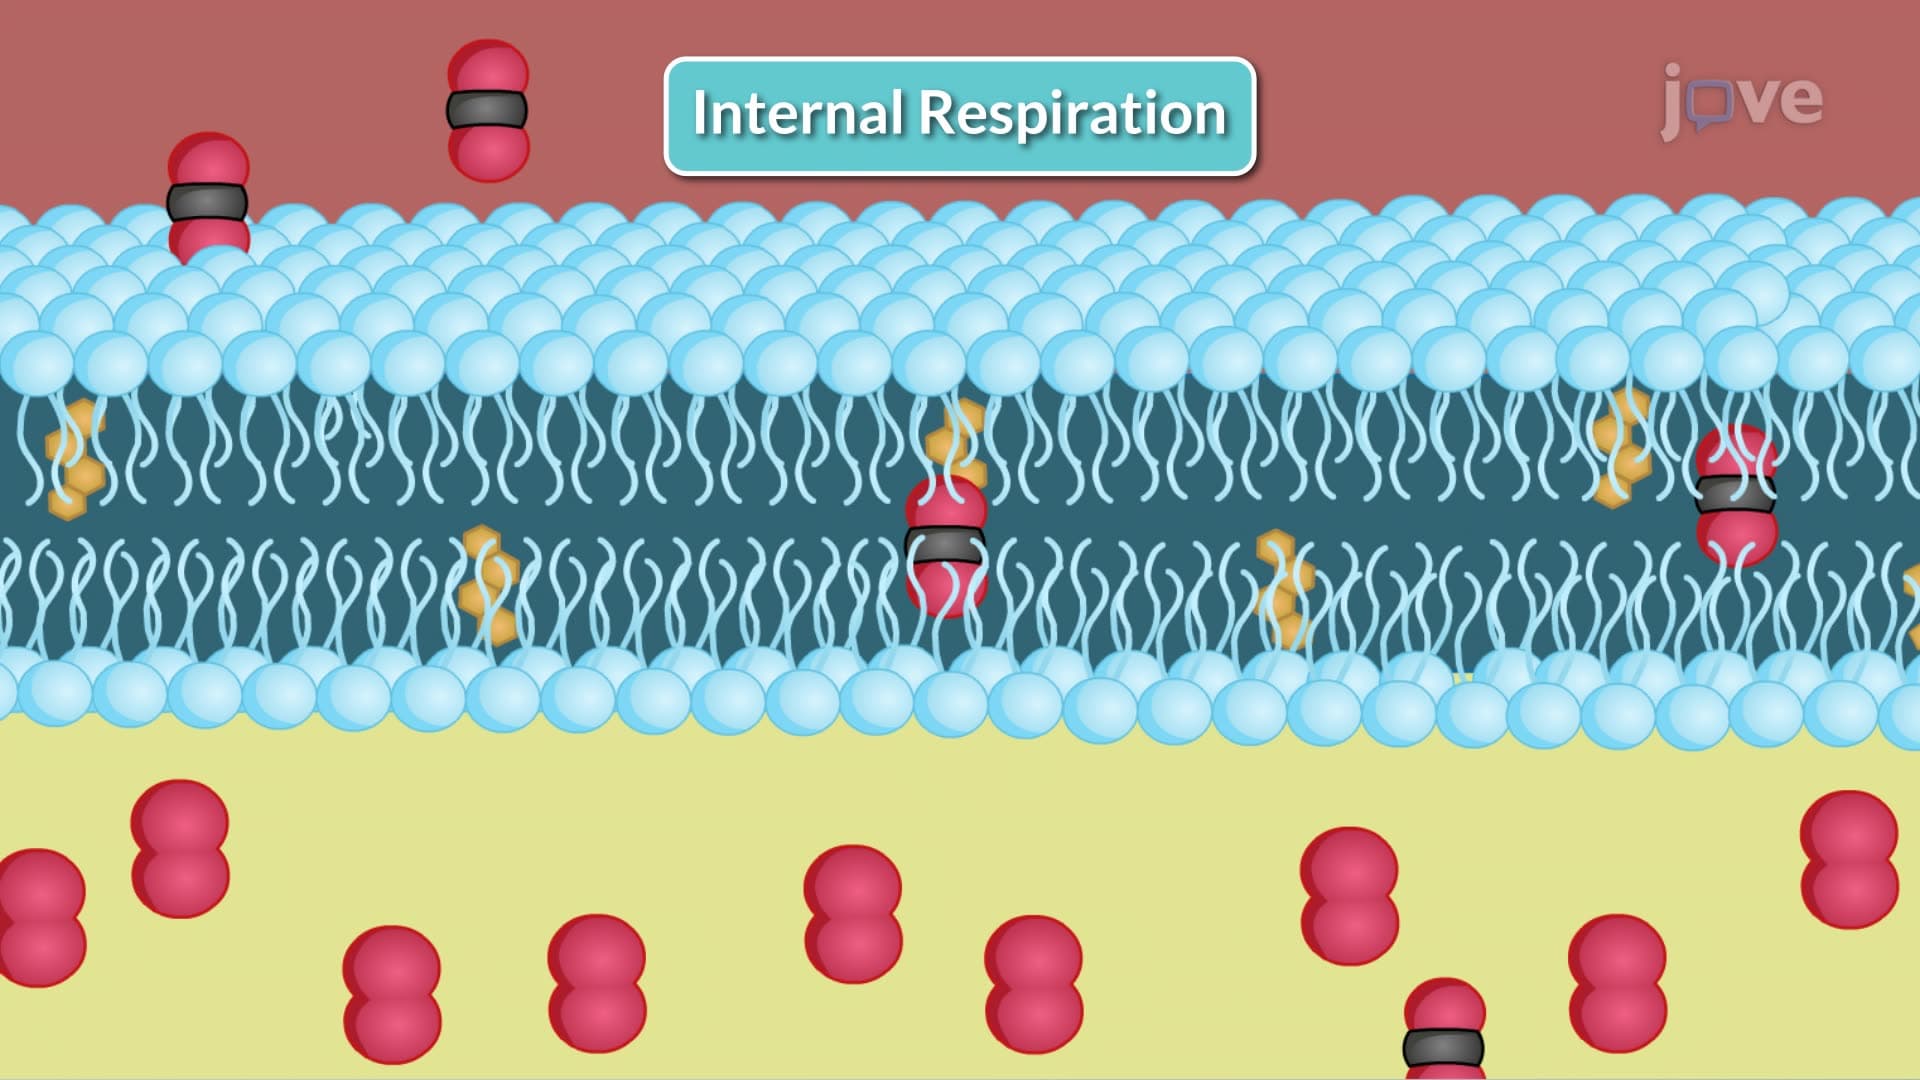
Respiration involves the exchange of gases, especially oxygen (O2) and carbon dioxide (CO2), between the alveoli and body cells, a process facilitated by blood circulation. As a result, the cardiovascular system, which involves the...
 01:23
Acute Respiratory Failure-IV