Related Experiment Video
Updated: Aug 13, 2026
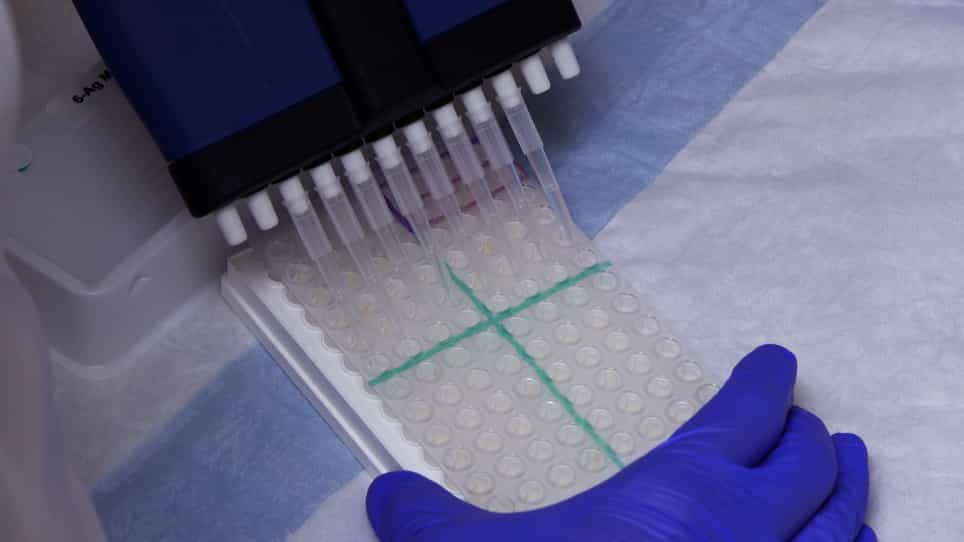

A High-Throughput Multiplexed Screening for Type 1 Diabetes, Celiac Diseases, and COVID-19
Published on: July 5, 2022
Screening for subclinical complications in young type 1 diabetic patients: experience acquired in Brussels
1Clinique de Diabétologie, Hôpital Universitaire des Enfants Reine Fabiola, Université Libre de Bruxelles, Bruxelles, Belgium. hdorchy@ulb.ac.be

Insights
Screening for diabetic complications like retinopathy, neuropathy, and nephropathy should begin at puberty. Early detection and improved metabolic control can prevent irreversible lesions in children with diabetes.
Area of Science:
- Pediatric diabetology
- Clinical endocrinology
- Diabetic complications research
Background:
- Clinical studies since the 1970s highlight the need for early detection of diabetic complications.
- Subclinical retinopathy, neuropathy, and nephropathy can be reversed with improved metabolic control.
- Understanding risk factors and early markers is crucial for preventing long-term complications.
Purpose of the Study:
- To establish optimal screening times for subclinical diabetic complications in children.
- To identify early indicators of retinopathy, neuropathy, and nephropathy.
- To investigate the relationship between metabolic control and the development of these complications.
Main Methods:
- Longitudinal clinical studies and specific diagnostic tests including fluorescein angiography, EEG, nerve conduction studies, and biochemical markers.
- Analysis of risk factors such as age at diagnosis, puberty, metabolic control, BMI, and cholesterol levels.
- Evaluation of novel markers like microtransferrinuria, urinary acid glycosaminoglycans, and C-reactive protein.
Main Results:
- Screening for retinopathy, neuropathy, and nephropathy should commence at puberty, at least 3 years post-diagnosis.
- Early abnormalities like microaneurysms and nerve fiber desynchronization can precede overt lesions.
- Risk factors identified include diabetes duration, younger age at diagnosis, puberty, poor metabolic control, high cholesterol, and elevated BMI.
- Certain markers like microalbumin, Beta2-microglobulin, microtransferrinuria, and C-reactive protein show potential for early detection.
Conclusions:
- Early detection of subclinical diabetic complications in children is feasible and essential.
- Improved metabolic control is key to reversing early abnormalities and preventing irreversible damage.
- Risk factor management and monitoring of specific biomarkers can aid in proactive intervention for diabetic microvascular and neurological complications.
Abstract:
Clinical studies conducted since the 1970s by the pediatric diabetology group of the Free University of Brussels have demonstrated that screening for subclinical retinopathy, neuropathy and nephropathy should be started at puberty and at least 3 years after the diabetes diagnosis. The goal is to detect early abnormalities responsible for subclinical disorders that can be reversed by improved metabolic control, thus preventing the occurrence of irreversible potentially incapacitating lesions. A 1974 retinal fluorescein angiography study showed that the development of microaneurysms, which are irreversible lesions, could be preceded by fluorescein leakage due to disruption of the blood-retinal barrier. Risk factors for early retinopathy include: duration of diabetes, age at diagnosis (with younger children having longer times to retinopathy), puberty and sex (with onset one year earlier in girls than in boys), long-term bad metabolic control over several years, high cholesterol levels and excessive body mass index (BMI). On the other hand, rapid improvement of diabetic control may worsen diabetic retinopathy (1985). Minimal EEG abnormalities were found in relationship to frequent and severe hypoglycemic comas and/or convulsions and retinopathy (1979). Desynchronization of action potentials in distal nerve fibers preceded conduction velocity slowing (1981). A single high glycated hemoglobin value was associated with peroneal motor nerve conduction slowing (1985), which was not observed in the femoral nerve (1987). Sympathetic skin response (1996) and statistical analysis of heart rate variability (2001) could have some interest for the diagnosis of early diabetic autonomic neuropathy. Early microproteinuria is of mixed origin, being both glomerular (microalbumin) and tubular (Beta2-microglobulin). Exercise testing to exhaustion did not provide additional information than the basal excretion (1976). Microtransferrinuria (1984) and urinary acid glycosaminoglycans output (2001) could also be predictive markers of glomerular dysfunction. Physical training reduced exercise-related proteinuria by half (1988). High levels of serum lipoprotein (a) were not associated with the presence of subclinical complications (1996). On the other hand, ultra sensitive C-reactive protein could be an interesting indicator for the risk of developing early complications (2002). Poor metabolic control was associated with higher levels of triglycerides, total cholesterol, LDL cholesterol and apolipoprotein B (1990). Decreased gluthatione peroxidase, gluthatione reductase and of vitamin C levels, denoting moderate oxidative stress, were found (1996), although there was no evidence of increased LDL cholesterol peroxidation (1998). Erythrocytes exhibited increased glycolytic activity and neutrophils decreased migration in relationship with metabolic control (1992). The degree of metabolic control influenced serum triiodothyronine levels (1985), magnesium concentrations (1999) and infection by Helicobacter Pylori (1997). Insulin therapy could activate the complement pathway if intermediate and long-acting insulin preparations without protamine sulphate are used (1992) and provoke higher BMI in adolescents on 4 insulin injections (1988). Well-being was inversely related to glycated hemoglobin levels (1997).

Related Concept Videos
 01:25
Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis
 01:15
Diabetes: Symptoms, Diagnosis, and Complications
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:19
Type I Diabetes III: Clinical Manifestations
 01:27
Diabetic Retinopathy
 01:22
Diabetes Mellitus: Type 2 and Gestational