Related Experiment Video
Updated: Jul 23, 2026


Diagnosis of Neoplasia in Barrett’s Esophagus using Vital-dye Enhanced Fluorescence Imaging
Published on: May 11, 2014
Predictive factors of coexisting cancer in Barrett's high-grade dysplasia
C Tharavej1, J A Hagen, J H Peters
1Division of Thoracic and Foregut Surgery, Department of Surgery, University of Southern California, Los Angeles, CA, USA.

Background:
Identification of high-grade dysplasia (HGD) in Barrett's esophagus has been considered an indication for esophagectomy because of the high risk for coexisting cancer. However, rigorous endoscopic surveillance programs recently have been recommended, reserving esophagectomy for patients whose cancer is identified on biopsy. This approach risks continued surveillance for patients who already have cancer unless reliable markers for the presence of occult cancer are identified. This study aimed to determine the endoscopic, histologic, and demographic features associated with the presence of occult cancer in patients with HGD.
Methods:
Endoscopic, histologic, and demographic findings for 31 patients who underwent esophagectomy for HGD were reviewed. The presence of an ulcer, nodule, stricture, or raised area on preoperative endoscopy was noted. The results of endoscopic biopsies taken before resection every 1 to 2 cm along the Barrett's segment were reviewed. The HGD was categorized as unilevel if the dysplasia was limited to one level of biopsy and as multilevel if more than one level was involved. Patients were divided into two groups according to the presence or absence of cancer in the resected specimens, and these variables were compared.
Results:
The prevalence of coexisting cancer in patients with HGD was 45% (14/31). Of the 31 patients in this study, 9 had a visible lesion. Cancer was found in the resected specimens from 7 (78%) of 9 patients with a visible lesion and 7 (32%) of 22 patients without a visible lesion (p = 0.019). Of 22 patients without a visible lesion, 10 had multilevel and 12 had unilevel HGD. The findings showed that 6 (60%) of 10 patients with multilevel HGD and 1 (8.3%) of 12 patients with unilevel HGD had cancer in the resected esophagus (p = 0.009).
Conclusion:
For patients with HGD, a lesion visible on endoscopy and/or HGD at multiple biopsy levels is associated with an increased risk for coexisting cancer. These patients should be considered for early esophagectomy.

Related Concept Videos
 02:07
Tumor Progression
Colon cancer is one of the best-documented examples of tumor progression. Early mutation in the APC gene in colon cells causes a small growth on the colon wall called a polyp. With time, this polyp grows into a benign, pre-cancerous tumor. Further...
 02:59
Cancer Prevention
Some...
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more similar...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:24
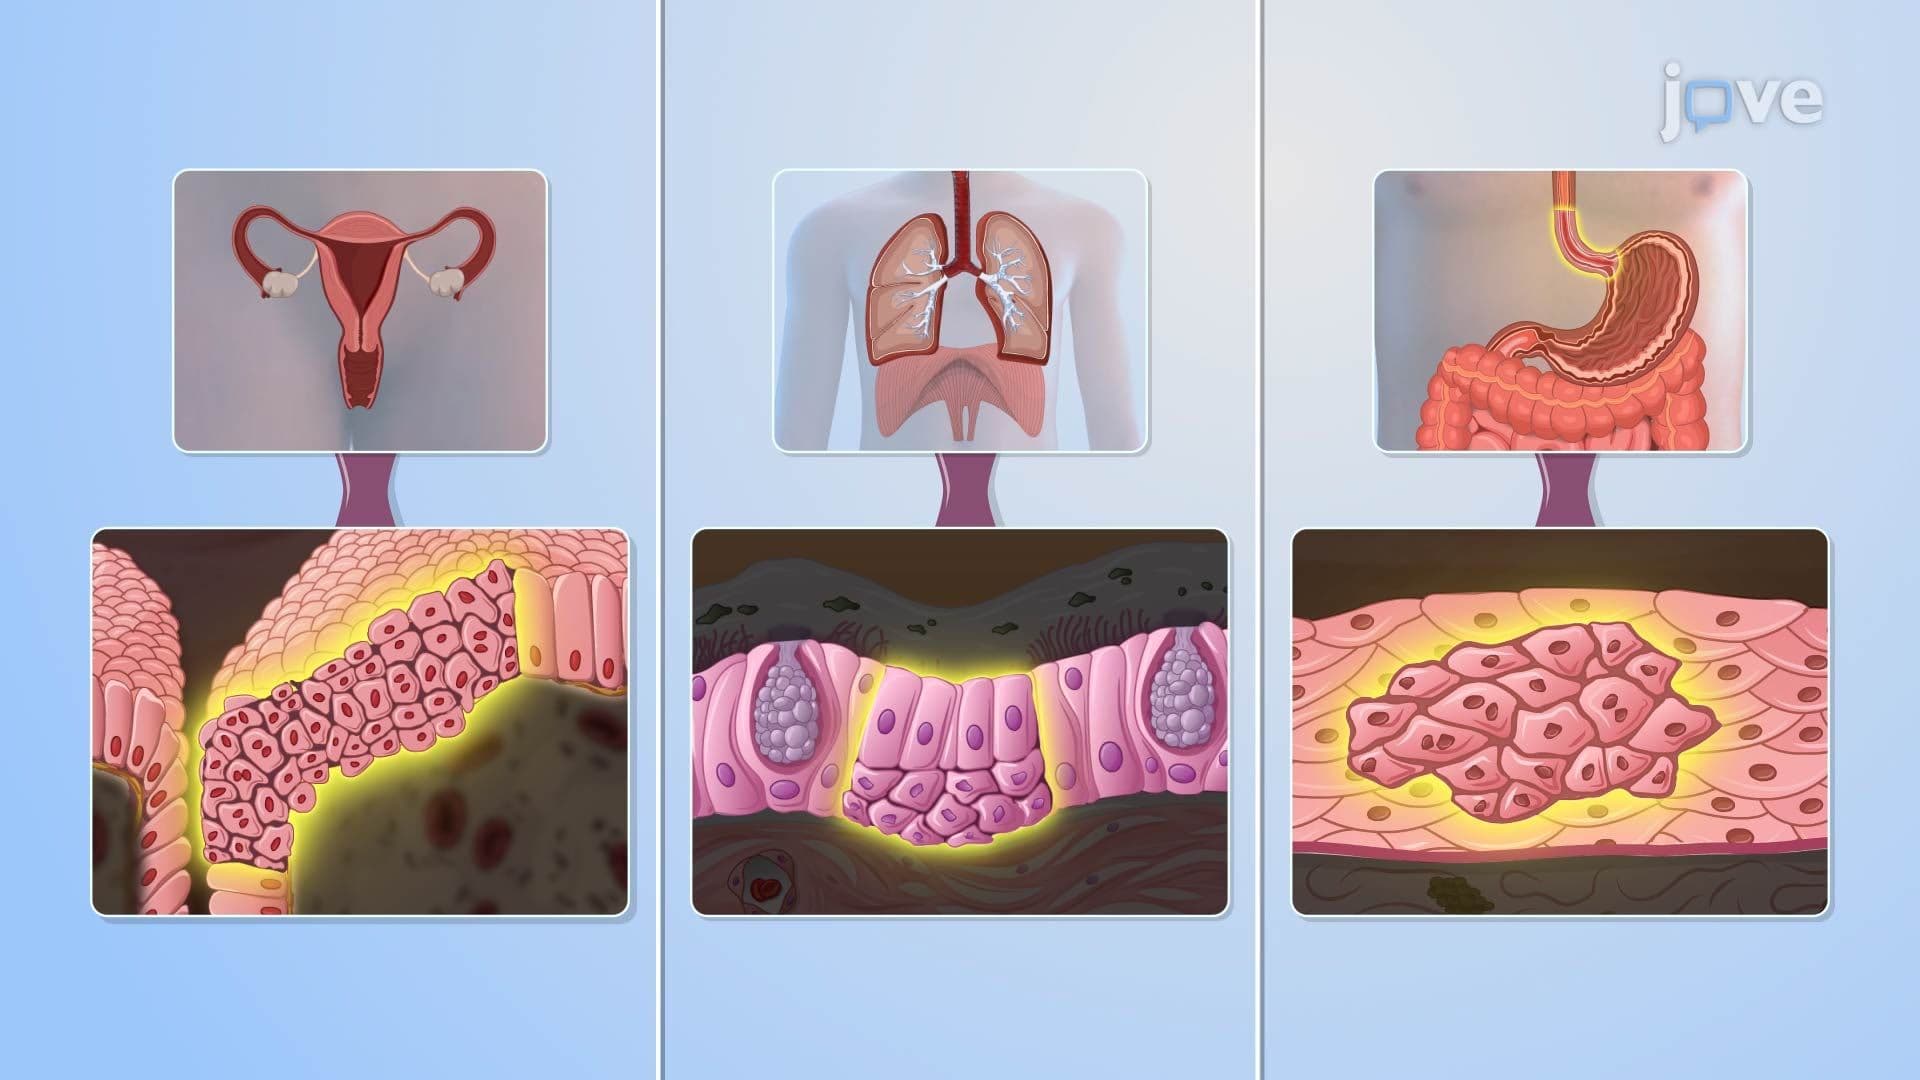
Cellular Adaptation IV: Dysplasia and Metaplasia