Does the clinical examination predict lower extremity peripheral arterial disease?
Related Experiment Video
Updated: May 8, 2026
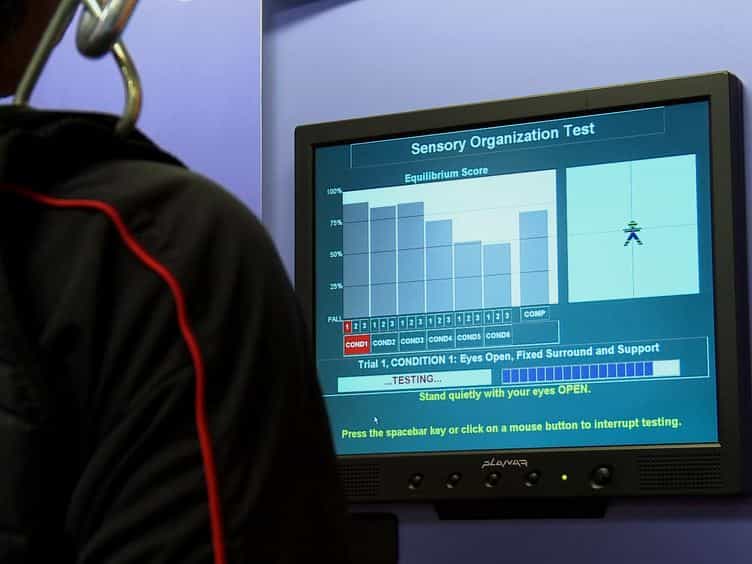
Computerized Dynamic Posturography for Postural Control Assessment in Patients with Intermittent Claudication
Published on: December 11, 2013
Nadia A Khan1, Sherali A Rahim, Sonia S Anand
1Department of Medicine, University of British Columbia, Vancouver, Canada. nakhan@shaw.ca

Context:
Lower extremity peripheral arterial disease (PAD) is common and associated with significant increases in morbidity and mortality. Physicians typically depend on the clinical examination to identify patients who need further diagnostic testing.
Objective:
To systematically review the accuracy and precision of the clinical examination for PAD.
Data Sources, Study Selection, And Data Extraction:
MEDLINE (January 1966 to March 2005) and Cochrane databases were searched for articles on the diagnosis of PAD based on physical examination published in the English language. Included studies compared an element of the history or physical examination with a reference standard of ankle-brachial index, duplex sonography, or angiogram. Seventeen of the 51 potential articles identified met inclusion criteria. Two of the authors independently extracted data, performed quality review, and used consensus to resolve any discrepancies.
Data Synthesis:
For asymptomatic patients, the most useful clinical findings to diagnose PAD are the presence of claudication (likelihood ratio [LR], 3.30; 95% confidence interval [CI], 2.30-4.80), femoral bruit (LR, 4.80; 95% CI, 2.40-9.50), or any pulse abnormality (LR, 3.10; 95% CI, 1.40-6.60). While none of the clinical examination features help to lower the likelihood of any degree of PAD, the absence of claudication or the presence of normal pulses decreases the likelihood of moderate to severe disease. When considering patients who are symptomatic with leg complaints, the most useful clinical findings are the presence of cool skin (LR, 5.90; 95% CI, 4.10-8.60), the presence of at least 1 bruit (LR, 5.60; 95% CI, 4.70-6.70), or any palpable pulse abnormality (LR, 4.70; 95% CI, 2.20-9.90). The absence of any bruits (iliac, femoral, or popliteal) (LR, 0.39; 95% CI, 0.34-0.45) or pulse abnormality (LR, 0.38; 95% CI, 0.23-0.64) reduces the likelihood of PAD. Combinations of physical examination findings do not increase the likelihood of PAD beyond that of individual clinical findings. However, when combinations of clinical findings are all normal, the likelihood of disease is lower than when individual symptoms or signs are normal. A PAD scoring system, which includes auscultation of arterial components by handheld Doppler, provides greater diagnostic accuracy.
Conclusions:
Clinical examination findings must be used in the context of the pretest probability because they are not independently sufficient to include or exclude a diagnosis of PAD with certainty. The PAD screening score using the hand-held Doppler has the greatest diagnostic accuracy.
More Related Videos

Related Concept Videos
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above the...
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:30
Peripheral Artery Disease I: Introduction
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:26
Peripheral Artery Disease IV: Nursing Management