Related Experiment Video
Updated: Aug 13, 2026
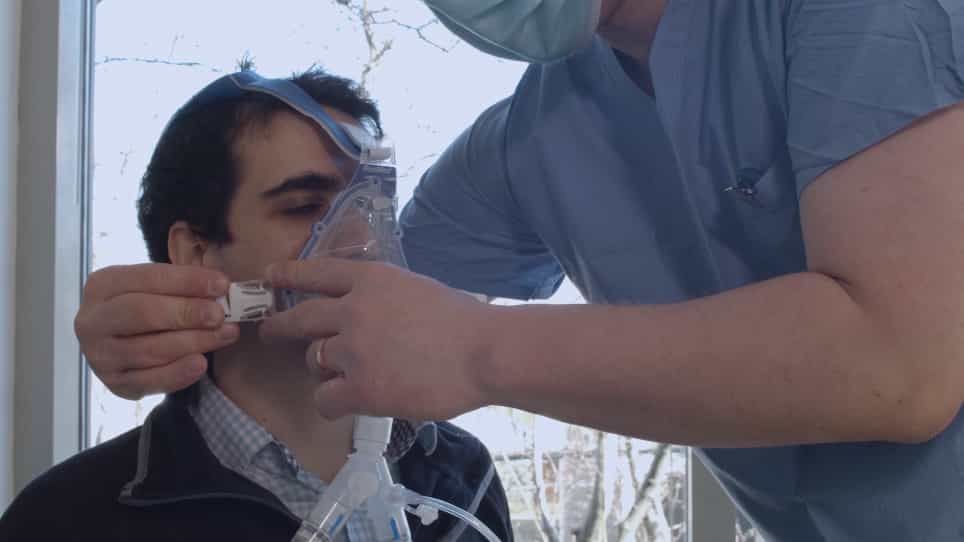

A Novel Inhalation Mask System to Deliver High Concentrations of Nitric Oxide Gas in Spontaneously Breathing Subjects
Published on: May 4, 2021
Exhaled nitric oxide is not reduced in infants with cystic fibrosis
P J Franklin1, G L Hall, A Moeller
1School of Paediatrics and Child Health, University of Western Australia, GPO Box D184, Perth, 6480, Western Australia. peterf@ichr.uwa.edu.au

Insights
Fractional exhaled nitric oxide (FeNO) is not reduced in infants with cystic fibrosis (CF). However, FeNO levels decrease with age in CF patients, indicating it is not a reliable marker for airway inflammation in this population.
Area of Science:
- Pediatric Pulmonology
- Respiratory Medicine
- Biomarker Research
Background:
- Fractional exhaled nitric oxide (FeNO) levels are reportedly reduced in cystic fibrosis (CF) patients.
- Conflicting data exist regarding FeNO in young children with CF, leaving its role as a primary disease feature or secondary response unclear.
Purpose of the Study:
- To compare FeNO levels between infants with CF and healthy infants.
- To investigate the relationship between FeNO, age, and airway inflammation markers in infants with CF.
Main Methods:
- A validated single-breath technique was used to measure FeNO in 23 healthy infants and 18 infants with CF.
- Lung function tests were performed on all participants.
- Bronchoalveolar lavage (BAL) was collected from CF infants to assess airway inflammation.
Main Results:
- No significant difference in FeNO was observed between CF infants and healthy infants.
- An inverse relationship between age and FeNO was found in CF patients, but not in healthy controls.
- No association was found between FeNO and BAL markers of airway inflammation in CF infants.
Conclusions:
- FeNO is not reduced in infants with cystic fibrosis.
- FeNO levels decrease with increasing age in infants with CF.
- FeNO is not a suitable marker for assessing airway inflammation in infants with cystic fibrosis.
Abstract:
Fractional exhaled nitric oxide (F(eNO)) has been reported to be reduced in cystic fibrosis (CF) patients. However, data from young children are conflicting and it is not clear whether this is a primary feature of the disease or a secondary response. The present study compared F(eNO) between CF and healthy infants using a validated single-breath technique. A total of 23 healthy infants (11 females; mean age 40.1 weeks) and 18 infants with CF (nine females; 64.9 weeks) underwent tests of lung function and F(eNO). Bronchoalveolar lavage (BAL) was collected from all CF infants 2-5 days after lung function testing. There was no significant difference in F(eNO) between the CF and healthy infants (geometric mean: 23.1 parts per billion (ppb) and 17.0 ppb, respectively). There was an inverse relationship between age and F(eNO) in the CF patients, but not in the healthy group. Within the CF group, there was no association between F(eNO) and any marker of airway inflammation measured in the BAL. Exhaled nitric oxide is not reduced in cystic fibrosis infants, but does decrease with age. The current data indicate that F(eNO) is not a good marker of airway inflammation in cystic fibrosis.
Related Concept Videos
 01:05
Breathing
 01:17
Pulmonary Cycle: Exhalation
 01:24
Cystic Fibrosis: Management
Sinus disease and chronic sinusitis...
 01:23
Upper Respiratory Drugs: Antitussives, Expectorants, and Mucolytics
Antitussives include codeine, dextromethorphan (Robitussin), and benzonatate (Tessalon). Codeine and dextromethorphan exert their effects centrally by suppressing the cough reflex center in the medulla. Benzonatate operates peripherally within the respiratory tract by anesthetizing...
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:23
Cystic Fibrosis: Pathogenesis
CF is primarily caused by a genetic mutation in a chromosome 7 gene coding for the cystic fibrosis transmembrane conductance regulator (CFTR) protein. The most common gene mutation leading to CF is the ΔF508 mutation, but...