Association between hypertension and primary mitral chordae tendinae rupture
Related Experiment Video
Updated: Aug 11, 2026

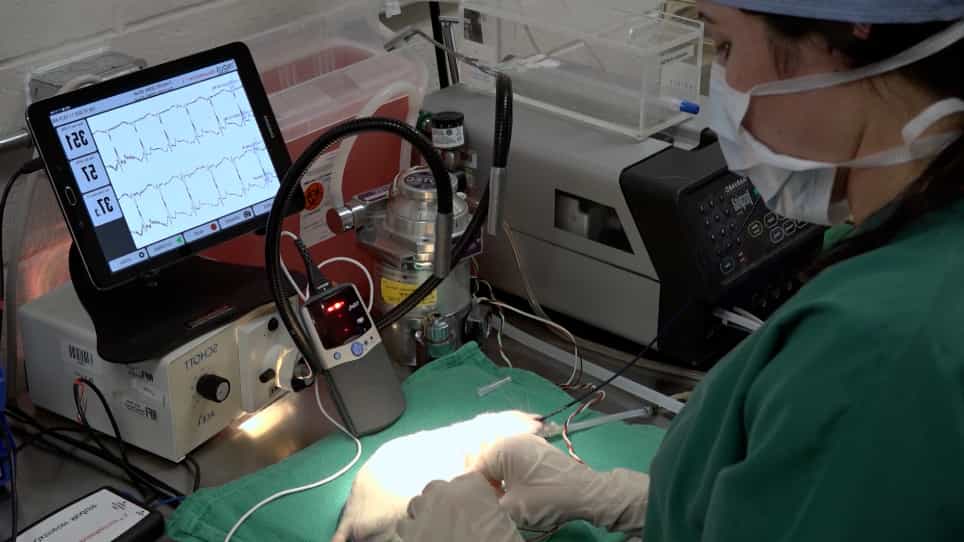
Rat Model of Right-Sided Cardiac Remodeling and Arrhythmia Using Pulmonary Artery Banding
Published on: August 30, 2024
Tsung-Hsien Lin1, Ho-Ming Su, Wen-Chol Voon
1Division of Cardiology, Department of Internal Medicine, Kaohsiung Medical University Chun-Ho Memorial Hospital, Kaohsiung Medical University, 100 Shi-Chuan 1st Road, Kaohsiung 80708, Taiwan, Republic of China. Sheush@kmu.edu.tw

Insights
Hypertension is an independent risk factor for primary chordae tendinae rupture (CTR), a condition leading to mitral regurgitation. Identifying hypertension and other factors aids early intervention for better survival chances in CTR patients.
Area of Science:
- Cardiology
- Valvular Heart Disease
Background:
- Chordae tendinae rupture (CTR) causes mitral regurgitation, leading to severe symptoms and potential need for mitral valve surgery.
- Early identification of CTR and its risk factors is crucial for timely intervention and improved survival rates.
- Hypertension is a potential risk factor for CTR due to increased mechanical strain on the mitral valve complex.
Purpose of the Study:
- To identify independent predictors of primary chordae tendinae rupture (CTR).
- To investigate the association between hypertension and primary CTR.
- To understand risk factors for CTR in patients undergoing mitral valve surgery.
Main Methods:
- A cross-sectional study involving 98 patients with mitral CTR at a single medical center in Taiwan.
- Patients were classified into primary (no obvious predisposing factors) and secondary (known predisposing causes) groups.
- Logistic regression analysis was used to identify independent predictors of primary CTR.
Main Results:
- The primary CTR group was older and had a significantly higher prevalence of hypertension and dyspnea compared to the secondary group.
- Hypertension was found to be an independent predictor for primary CTR (odds ratio = 2.717, P = .048).
- Age was also an independent predictor for primary CTR (odds ratio = 1.039, P = .039).
Conclusions:
- Hypertension is an independent predictor of primary chordae tendinae rupture (CTR).
- Age is also an independent predictor for primary CTR.
- These findings highlight the importance of managing hypertension in preventing CTR.
Background:
Mitral regurgitation from chordae tendinae rupture (CTR) may cause severe clinical symptoms and is a progressive disease that eventually results in the need for mitral valve surgery. Early recognition of CTR and identification of risk factors are important because early intervention increases the chances of survival. Hypertension may increase mitral valve complex mechanical strain and cause the chordae tendinae to rupture.
Method:
Using a cross-sectional study of medical files in one medical center in Taiwan, we enrolled 98 patients with mitral CTR and classified them into two groups, comprising 68 subjects (69%) without obvious predisposing factors (primary group) and 30 subjects (31%) with known predisposing causes (secondary group).
Result:
Of the subjects, 63 (64%) were men with a mean age of 57.5 +/- 1.5 years. The posterior mitral leaflet was most commonly involved (64%). The known predisposing factors in secondary group include mitral valve prolapse, infective endocarditis, and rheumatic heart disease. The patients who had primary CTR were older (59.9 +/- 1.6 v 52.1 +/- 3.1 years, P = .029), had a higher prevalence of hypertension (56% v 30%, P = .018) and complained more often of dyspnea (82% v 53%, P = .003) than the patients in the secondary group. Using binary logistic regression analyses, the variation in primary group was found to be independently explained by age (P = .039, odds ratio = 1.039, 95% confidence interval = 1.002 to 1.077) and hypertension (P = .048, odds ratio = 2.717, 95% confidence interval = 1.008 to 7.326).
Conclusion:
We conclude that hypertension was an independent predictor for primary CTR in this study.
More Related Videos

Related Concept Videos
 01:27
Mitral Valve Prolapse I: Introduction
 01:20
Mitral Regurgitation I: Introduction
 01:22
Mitral Stenosis I: Introduction
 01:22
Mitral Valve Prolapse II: Assessment and Management
 01:23
Rheumatic Heart Disease I: Introduction
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests