Related Experiment Video
Updated: Jun 19, 2026

A High-throughput Method for Measurement of Glomerular Filtration Rate in Conscious Mice
Published on: May 10, 2013
Cardiovascular outcomes in high-risk hypertensive patients stratified by baseline glomerular filtration rate
Mahboob Rahman1, Sara Pressel, Barry R Davis
1Case Western Reserve University, Cleveland, Ohio, USA.

Insights
Older patients with hypertension and reduced kidney function face higher risks of coronary heart disease (CHD) than end-stage renal disease (ESRD). Lower glomerular filtration rate (GFR) independently predicts increased CHD risk.
Area of Science:
- Nephrology
- Cardiology
- Hypertension Management
Background:
- Chronic kidney disease (CKD) is prevalent in elderly hypertensive individuals.
- CKD significantly increases cardiovascular disease (CVD) risk.
Purpose of the Study:
- Compare rates of coronary heart disease (CHD) and end-stage renal disease (ESRD).
- Assess glomerular filtration rate (GFR) as an independent predictor of CHD risk.
- Evaluate the efficacy of amlodipine, lisinopril, and chlorthalidone in modifying CVD outcomes in high-risk hypertensive patients stratified by GFR.
Main Methods:
- Post hoc subgroup analysis of a multicenter randomized, double-blind, controlled trial.
- Inclusion of 32,077 hypertensive patients aged 55+ with CHD risk factors, stratified by baseline GFR.
- Random assignment to chlorthalidone, amlodipine, or lisinopril.
Main Results:
- In patients with moderate-to-severe GFR reduction, 6-year CHD rates (15.4%) exceeded ESRD rates (6.0%).
- A GFR < 53 mL/min/1.73 m² independently predicted a 32% higher CHD risk.
- Chlorthalidone demonstrated superior efficacy in preventing heart failure compared to amlodipine and lisinopril.
Conclusions:
- Reduced GFR in older hypertensive patients is an independent predictor of increased CHD risk.
- Chlorthalidone is more effective than amlodipine or lisinopril in preventing heart failure.
- No significant difference in CHD, stroke, or combined CVD event prevention among the three agents.
Background:
Chronic kidney disease is common in older patients with hypertension.
Objective:
To compare rates of coronary heart disease (CHD) and end-stage renal disease (ESRD) events; to determine whether glomerular filtration rate (GFR) independently predicts risk for CHD; and to report the efficacy of first-step treatment with a calcium-channel blocker (amlodipine) or an angiotensin-converting enzyme inhibitor (lisinopril), each compared with a diuretic (chlorthalidone), in modifying cardiovascular disease (CVD) outcomes in high-risk patients with hypertension stratified by GFR.
Design:
Post hoc subgroup analysis.
Setting:
Multicenter randomized, double-blind, controlled trial.
Participants:
Persons with hypertension who were 55 years of age or older with 1 or more risk factors for CHD and who were stratified into 3 baseline GFR groups: normal or increased (> or = 90 mL/min per 1.73 m2; n = 8126 patients), mild reduction (60 to 89 mL/min per 1.73 m2; n = 18,109 patients), and moderate or severe reduction (< 60 mL/min per 1.73 m2; n = 5662 patients).
Interventions:
Random assignment to chlorthalidone, amlodipine, or lisinopril.
Measurements:
Rates of ESRD, CHD, stroke, and combined CVD (CHD, coronary revascularization, angina, stroke, heart failure, and peripheral arterial disease).
Results:
In participants with a moderate to severe reduction in GFR, 6-year rates were higher for CHD than for ESRD (15.4% vs. 6.0%, respectively). A baseline GFR of less than 53 mL/min per 1.73 m2 (compared with >104 mL/min per 1.73 m2) was independently associated with a 32% higher risk for CHD. Amlodipine was similar to chlorthalidone in reducing CHD (16.0% vs. 15.2%, respectively; hazard ratio, 1.06 [95% CI, 0.89 to 1.27]), stroke, and combined CVD (CHD, coronary revascularization, angina, stroke, heart failure, and peripheral arterial disease), but less effective in preventing heart failure. Lisinopril was similar to chlorthalidone in preventing CHD (15.1% vs. 15.2%, respectively; hazard ratio, 1.00 [CI, 0.84 to 1.20]), but was less effective in reducing stroke, combined CVD events, and heart failure.
Limitations:
Proteinuria data were not available, and combination therapies were not tested.
Conclusions:
Older high-risk patients with hypertension and reduced GFR are more likely to develop CHD than to develop ESRD. A low GFR independently predicts increased risk for CHD. Neither amlodipine nor lisinopril is superior to chlorthalidone in preventing CHD, stroke, or combined CVD, and chlorthalidone is superior to both for preventing heart failure, independent of level of renal function.


Related Concept Videos
 01:28
Glomerular Filtration Rate and its Regulation
GFR regulation involves two primary intrinsic controls: the myogenic and tubuloglomerular feedback mechanisms.
The myogenic...
 01:02
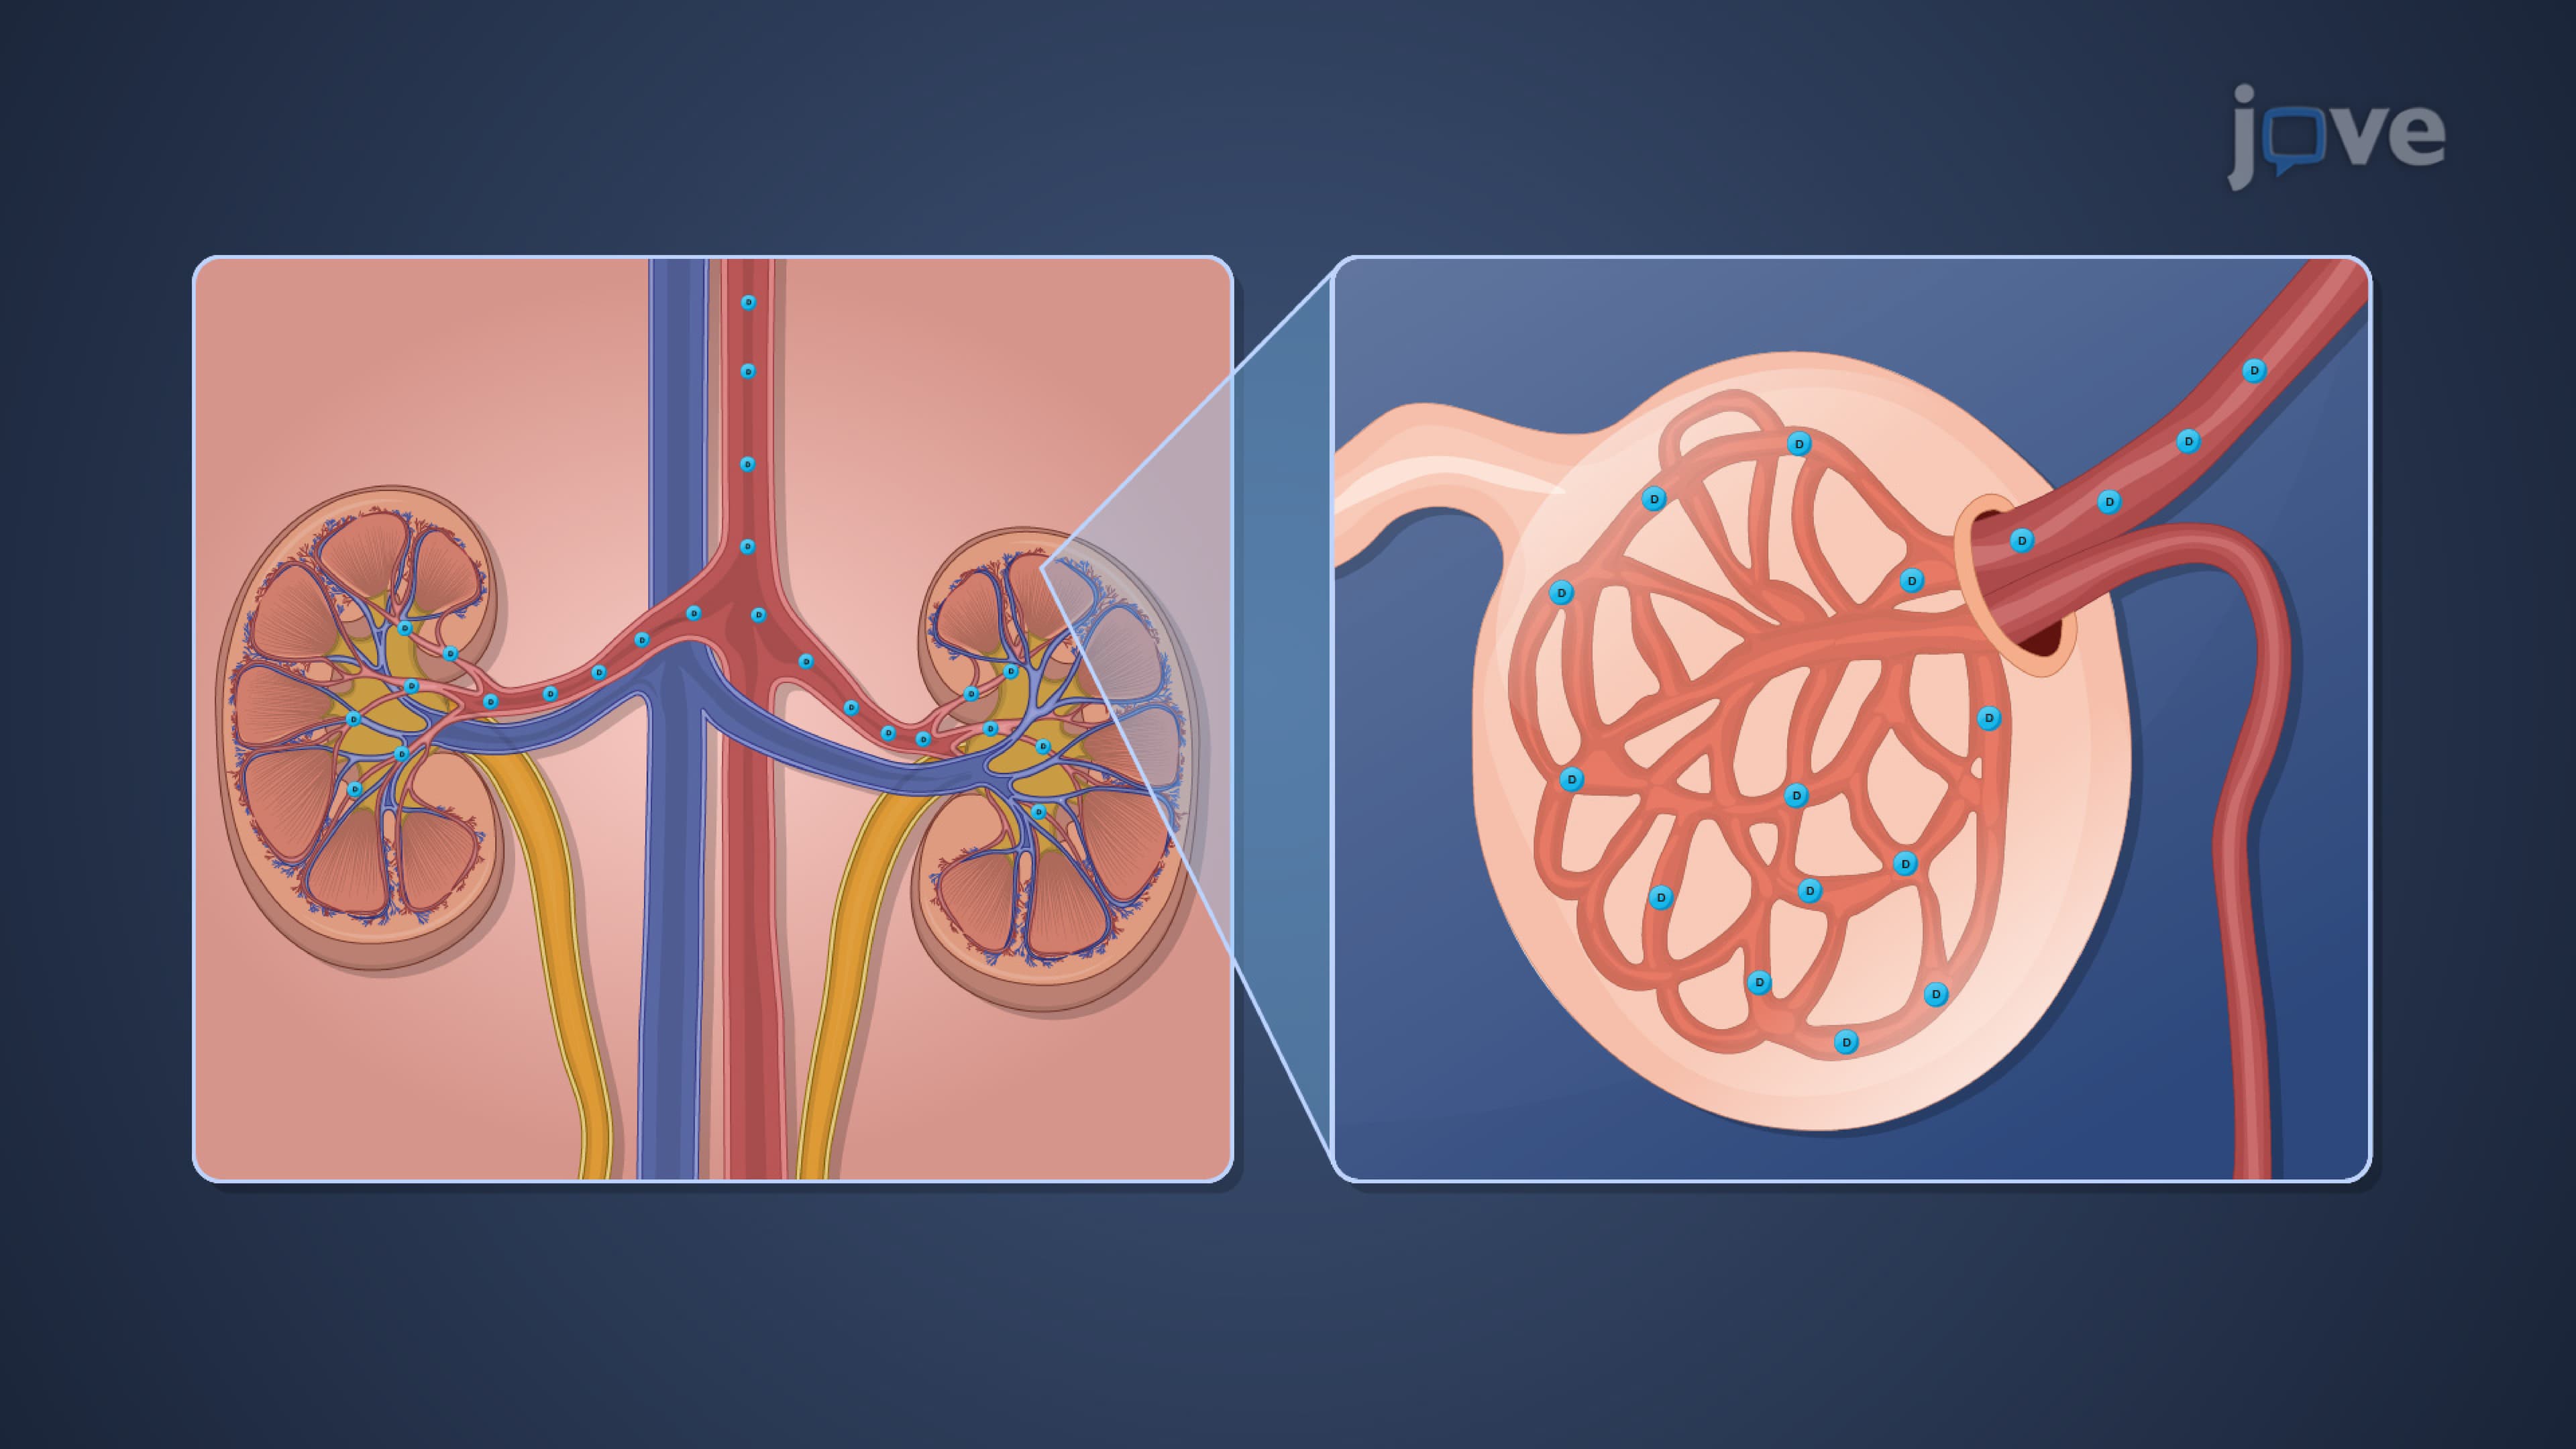
Renal Drug Excretion: Glomerular Filtration
Drugs gain access to the kidney via the renal artery, which progressively branches off into afferent arterioles.
 01:25
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:28
Diabetic Nephropathy