Related Experiment Video
Updated: Aug 11, 2026
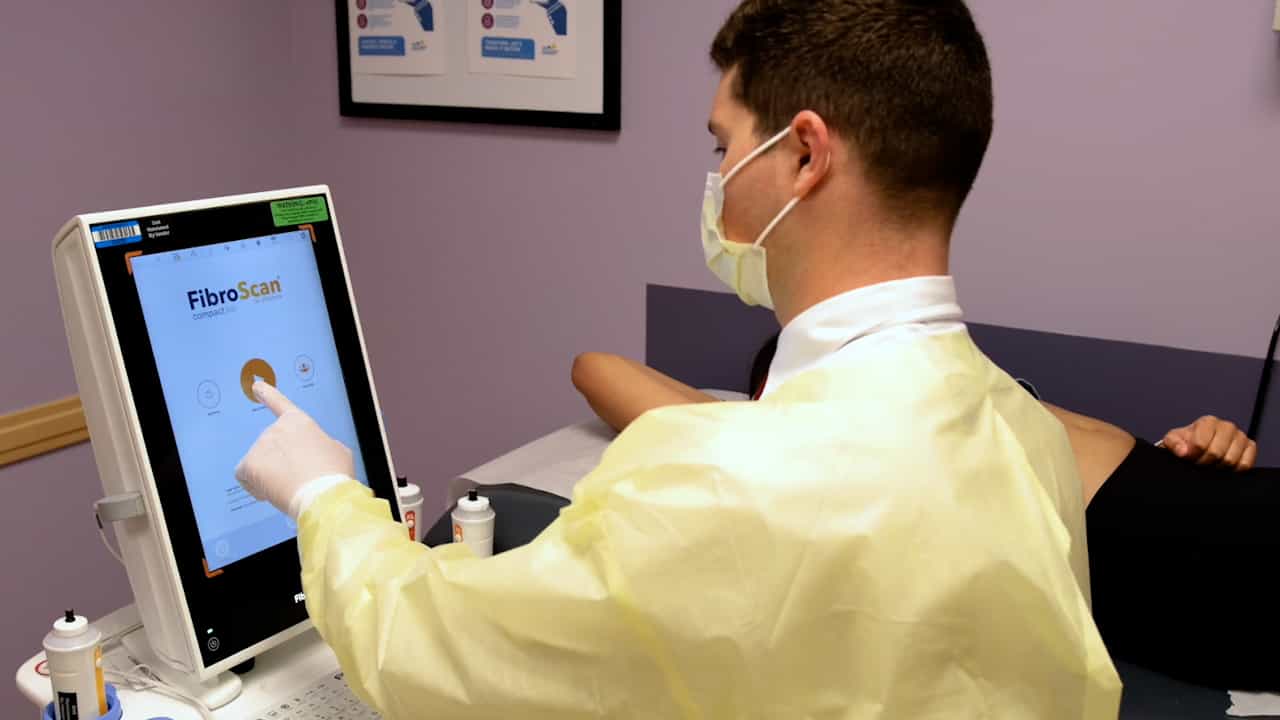
Implementation of Non-invasive Point of Care Transient Elastography for Evaluation of Liver Disease in Pediatric Populations with Cystic Fibrosis
Published on: August 29, 2025
Is significant cystic fibrosis-related liver disease a risk factor in the development of bone mineralization
George Alex1, Anthony G Catto-Smith, Michael Ditchfield
1Department of Gastroenterology and Nutrition, Royal Children's Hospital, Melbourne, Australia.

Abstract:
In order to assess the effects of significant cystic fibrosis-related liver disease (CFLD) on bone health, we compared the bone mineral status of older children and adolescents with CFLD to those with cystic fibrosis (CF) alone. Thirteen children (age range, 10-19 years) from our clinical CF services were identified with significant CFLD (9 of these 13 patients had clinical and radiological evidence of portal hypertension). This cohort was then matched by age, gender, and anthropometric measurements with equal numbers of patients with CF alone. All patients had a dual-energy X-ray absorptiometry (DEXA) scan to determine bone mineral content (BMC), bone area (BA), bone mineral density (BMD), and bone mineral apparent density (BMAD) in the region of the lumbar spine. Blood was drawn to determine serum vitamin A, D, E, and K status and liver function tests. The best forced expired volume in 1 sec (FEV1) for each patient in the 12 months around the time of the scan was also documented. Patients with CFLD had slightly worse FEV1 (82 +/- 20% vs. 91 +/- 16%, P = 0.05) and significantly higher alanine aminotransferase (65.5 +/- 35 IU/l vs. 30 +/- 20 IU/l, P = 0.01) than those with CF alone. The mean lumbar spine BA, BMC, BMD, and BMAD were not different between children with CFLD and CF. In conclusion, the presence of significant liver disease in children with CF does not appear to be an additional risk factor for the development of abnormal bone mineralization.


Related Concept Videos
 01:23
Cystic Fibrosis: Pathogenesis
CF is primarily caused by a genetic mutation in a chromosome 7 gene coding for the cystic fibrosis transmembrane conductance regulator (CFTR) protein. The most common gene mutation leading to CF is the ΔF508 mutation, but...
 01:31
Essential Minerals for Bone Health
Calcium and Phosphorus
Calcium is a critical component of bones, especially in the form of calcium phosphate and calcium carbonate. Since the body cannot make calcium, it must be obtained from the diet. However, calcium cannot be absorbed from the small intestine without...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...
 01:31
Osteoclasts in Bone Remodeling
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...