Related Experiment Video
Updated: Aug 11, 2026
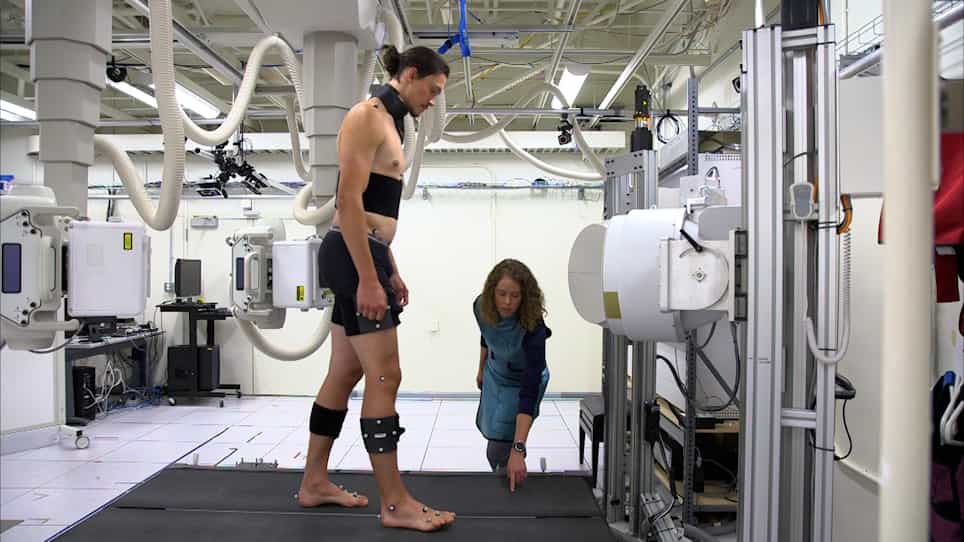

In Vivo Quantification of Hip Arthrokinematics during Dynamic Weight-bearing Activities using Dual Fluoroscopy
Published on: July 2, 2021
Developmental dysplasia of the hip: definition, recognition, and prevention of late sequelae
1Crouse Hospital Pediatric Orthopedics, Syracuse, NY, USA. robertcady@aol.com

Insights
Preventing late diagnosis of developmental dysplasia of the hip (DDH) requires skilled infant hip exams. Early detection minimizes long-term hip problems and arthritis, but some cases remain undetected at birth.
Area of Science:
- Pediatric Orthopedics
- Developmental Dysplasia of the Hip (DDH)
- Neonatal Screening
Background:
- Late presentation of developmental dysplasia of the hip (DDH) causes significant distress and potential litigation.
- Current diagnostic methods can minimize, but not entirely eliminate, late DDH diagnosis.
- Undetected DDH at birth may lead to premature degenerative arthritis, increasing morbidity and healthcare costs.
Purpose of the Study:
- To emphasize the critical importance of early detection and prevention of late-presenting developmental dysplasia of the hip (DDH).
- To highlight the need for improved clinical skills in neonatal hip examination.
- To discuss strategies for enhancing the detection and management of DDH in infants.
Main Methods:
- Review of current diagnostic techniques for developmental dysplasia of the hip (DDH).
- Emphasis on the necessity of repeated, careful physical examinations of infants within the first year of life.
- Discussion of educational strategies for clinicians, including specialized training and formal screening programs.
Main Results:
- Approximately 15% of developmental dysplasia of the hip (DDH) cases are not detectable at birth, even with expert examination or ultrasonography.
- Thorough documentation of infant hip examinations is crucial for clinical practice and medicolegal protection.
- A combination of careful physical examination and imaging (ultrasonography or X-rays) for at-risk infants is the optimal strategy.
Conclusions:
- Improving clinicians' proficiency in neonatal hip examination is paramount to prevent late presentations of DDH.
- Early identification and treatment of DDH in newborns can reduce the incidence of adult degenerative hip arthritis.
- Systematic screening programs and enhanced documentation practices are essential for minimizing the impact of DDH.
Abstract:
When a child presents with a dislocated hip after the walking age, parents are upset, pediatricians are distraught, and lawsuits often follow. The prevention of late presentation is a goal that all practitioners should strive for. However, at this time, using current diagnostic techniques, the late presentation of DDH can be minimized but not eliminated. The AAP Subcommittee on DDH has estimated that approximately 15% of DDH at birth is not detectible, even by experienced examiners or ultrasonographers. In addition to preventing the late presentation of a developmentally dislocated hip, the prevention of premature degenerative arthritis of the hip secondary to developmental subluxation and acetabular dysplasia is equally, if not more, important in terms or morbidity and cost. It is hoped that the identification and treatment of babies with DDH at birth will have the added benefit of decreasing the incidence of degenerative arthritis of the hip in adults. As the key to early detection remains repeated, careful examination of the infant in the first year of life, it is imperative for practitioners to become as skilled as possible in performing the exam. Unfortunately, medical school curricula and pediatric and family practice residency programs often are deficient in teaching the neonatal hip examination. Strategies for clinicians to improve their examination technique include asking a pediatric orthopedic surgeon to demonstrate the examination in their nursery or attending one of the AAP courses on DDH. Starting a formal DDH screening program in the nursery is another option, using few screeners to maximize their experience. Nurse practitioners, physician's assistants, and physiotherapists could be used in addition to physicians. Having a child present with a developmentally dislocated hip after the walking age is not malpractice if the child has had repeated careful examinations. It is important to document the examinations in writing, rather than placing a check mark next to "musculoskeletal" or "hips" on standard, pre-printed exam forms. The best documentation is a handwritten note that states "the hips are stable and there is wide symmetrical abduction" at every well-child visit. At this time, careful, repeated physical exam supplemented by ultrasonography or X-rays for babies with risk factors is our best strategy to minimize the late presentation of DDH.
Related Concept Videos
 01:27
Degenerative Disc Disease I: Introduction
 01:07
Development of the Limb Synovial Joints
The mesenchymal stem cells differentiate into chondrocytes that form the hyaline cartilage, and later the cartilaginous model of the bone. This model further transforms into a bone. This process is known as endochondral ossification.
During development, the limbs...
 01:07
Teratogenicity
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility, suggesting a...